Part 5 — CHAPTER XXXI. SURGICAL DISEASES OF THE JOINTS AND JOINT STRUCTURES. (continued 2)
Reading edition
Danger attaches to the performance of the so-called bloodless operations, in that there is a possibility of laceration of nerve trunks or of large vessels which may have become fixed in the condensed tissues and be torn with them. There is more danger of this perhaps at the knee than in other joints, and ruptures of the popliteal vessels and nerves have been repeatedly reported. The first attempt in breaking up such a joint should be to increase the degree of flexion. If by efforts in this direction the tissues can be first released, then there is less danger of their yielding when extension is made. Another danger which threatens in all resistant cases, and especially in elderly people, is fracture of bones. The writer has seen the upper end of the tibia as well as the neck of the humerus yield under these circumstances. In the latter event one should endeavor to prevent bony union, and thus to gain a false joint in place of the original.
In regard to the nature of the operative attacks upon the above types, the following is copied from Murphy:[33]
A. Extracapsular disease - 1. Tendon elongation (tendoplasty).
2. Tendovaginitis (exsection of sheath).
3. Cicatrices (removal).
B. Intracapsular - 1. Adhesive synovitis (exsection of capsule).
2. Replacement by aponeurosis or muscle.
C. Osseous - 1. Disconnect bones.
2. Remove neighboring bony processes or prominences.
3. Liberate soft parts.
4. Prevent subsequent bony contact.
5. Interpose tissue to form hygroma or fibrous surface.
D. Joints suitable for operation. - 1. Mandibular.
2. Hip.
3. Shoulder.
4. Elbow.
5. Knee.
E. Technique - 1. Flap formation (skin flap with fascia, or muscular).
2. Exposure of ankylosed area.
3. Osseous separation.
4. Transplantation and fixation of interposition flap.
5. Replacement of bone.
6. Fixation of parts.
7. Drainage.
F. Subsequent treatment - 1. Passive motion
2. Active motion.
3. Forced traction.
To the various expedients which may be adopted for making stiffened joints more useful may be given, in a general way, the term arthroplasty. A variety of mechanical contrivances have been resorted to in the past, operators hoping to be able to secure, for instance, a movable knee instead of one which is stiff. Artificial joints, made of celluloid, ivory, etc., have been used for experimental purposes, but while occasionally they have given good results in animals, they have rarely been satisfactory in man. For the prevention of re-adhesion, plates of celluloid, thin metal, gutta-percha, rubber, etc., have been used. These are either wrapped around a bone end or are used for lining a bone cavity, and rapidly accumulating experience is showing that this may be done with great benefit.
Thoroughness of operative work is one of the important contributing agents to the securement of wide range of motion, especially in complete removal of synovial membrane, capsule, and ligaments. Soft parts should be liberated thoroughly. Of the materials which can be interposed between bone ends in order to prevent reunion, muscular aponeurosis, with a certain amount of fatty tissue, makes the best material for interposition. When aponeurosis cannot be secured, then muscle should be tried, with some fat, as the former flattens out and undergoes structural changes, with conversion into fibrous tissue.
It should be represented to the patient as a legitimate scientific experiment, and in such a way that no matter what may happen no blame can be attached to the operator. In general it may always be stated that the older the lesion the less satisfactory will be any measure of treatment except possibly resection and arthroplasty.
ARTHRODESIS.
This term applies to the intentional production of ankylosis in a joint previously healthy or nearly so, with the intention of stiffening a useless limb and thus enhancing its usefulness. The measure applies mainly to those cases of infantile paralysis, with loss of control of the knee or ankle, or both, when by stiffening the limb it can be made to serve the purpose of a crutch. It is the last resort in this direction when there is no possibility for tendon grafting. Long confinement of a limb in a fixed dressing will lead to considerable stiffening of the joint, yet a joint so immobilized lacks that firmness of support called for in cases above mentioned. Therefore when it is desired to perform arthrodesis the joint is usually opened and more or less of its articular surface removed, the intent being to produce the effect in the shortest time and in the best way. It can be better attained by a removal of articular surfaces with the saw and the apposition of fresh bone surfaces to each other, their retention being ensured either by sutures (tendon or wire) or accurate fixation in plaster of Paris. Under these circumstances drainage should not be necessary, and limbs can be completely enclosed in a fixed dressing.
MAJOR OPERATIONS ON JOINTS.
Aside from arthrotomy and partial or complete arthrectomy, as above mentioned, the latter, including removal of synovia or cartilage, and perhaps curetting of bone foci, the formal resections or excisions of joints remain to be considered. The latter is the preferable term, as it is meant to include removal of the component parts that enter into the construction of joints, while the term resection implies rather the removal merely of portions of bone.
Joint excisions are practised especially for the following purposes: (a) To atone for the result of old unreduced dislocations; (b) in certain compound dislocations, with or without fracture; (c) in certain comminuted fractures where there is no prospect of recovery with useful joints; (d) in the destructive forms of acute arthritis where the entire joint is disorganized and the bone ends carious; (e) in tuberculous arthritis or panarthritis, with or without suppurative complications; (f) in occasional instances of disabling osteo-arthritis; (g) for relief of ankylosis, either for improvement of position (knee) or restoration of motion; (h) occasionally after gunshot injuries. Excisions required by the exigencies of traumatisms should be promptly done. If the case be complicated with septic infection the prognosis is much less favorable. For convenience of description excisions may be classified as primary, intermediary, and secondary. According to the joint involved, as at the knee, the purpose underlying the operation is to effect an absolutely rigid bony ankylosis.
The development and perfection of the general method of joint excisions is a matter of but little more than a century. Previous to that time amputation was almost the only resort when destruction had occurred. The most prominent surgeons in the early development of the measure were Park, of Liverpool, and Moreau, of France. During the latter part of the past century Ollier, of Lyons, greatly improved the technique by demonstrating the importance of the periosteum and by introducing the so-called subperiosteal methods. This is of great value in uninfected cases. It is a mistake, however, to endeavor to save periosteum which has become involved in the tuberculous process; in fact, in the presence of tuberculous disease we cannot be too radical in the removal of all affected tissue.
In the so-called subperiosteal method the operator endeavors, so far as possible, to preserve the periosteum of the parts exposed to attack, and, if possible, the capsular ligament as well. Thus at the elbow the capsule, if not diseased or obliterated, should be preserved, the osseous tissue being shelled out from within, so far as possible. The less, then, the connections between the capsule and the periosteum are disturbed the better. The French apply to this method the term “subcapsular periosteal.” When the bone covering can be preserved new bone is easily formed to replace that which has been lost, especially during adolescence, while the preservation of the capsule, with its ligamentous connections, affords a better joint cavity than will the substitute which results from natural processes. Furthermore the surrounding tendons are less disturbed and the condition remains more like the original. Nevertheless one does not exsect healthy joints, and the method is not always easy nor even possible of performance. It will suffice to say that it should be adhered to only as far as circumstances may justify or permit.
Surgeons, however, have not been satisfied with the older methods, and have endeavored to still further enhance motility in operated joints. (See above—Arthroplasty.) To this end the interposition of muscle, fascia, or of foreign membrane has been suggested. Thus, after removal of the head of the femur a strip of fascia lata may be interposed between the raw-bone surface and the cavity of the acetabulum, being fastened there by catgut sutures. In the shoulder a similar procedure has been carried out, utilizing a strip of deltoid muscle. At the elbow a piece of the pronator radii teres may be detached and fixed by sutures to the brachialis anticus. In every case the method should be adapted to the demands made, the intent being to cover divided bone ends with tissue which will prevent osseous union, as it is known to do in many cases of fracture where such interposition produces non-union. In so far as one attempts here to imitate conditions which are considered undesirable in certain other traumatisms, Murphy has done more than any other American surgeon, both in the experimental and clinical study of this subject. (See above.)
For the joints below the hip and shoulder the bloodless method will facilitate operative work. In case of a septic joint, however, it would not be advisable to apply the elastic bandage below and then over and around the joint, as by the pressure thus made some septic material may be forced into the absorbents. In clean cases the rubber bandage is a great advantage to the operator. It has this objection, however, in that hemorrhage which does not occur during the operation has to be checked after its conclusion, and I have often thought it advisable to avoid the use of the bandage and to secure vessels as they are divided, in order that when bleeding has once ceased there be no fear of its recurrence later.
The question of drainage is one of importance. In a general way one may feel that in an absolutely clean case drainage is not required, save possibly a small opening for escape of blood. If practised at all it should be thoroughly done. Drainage tubes are often too small and do not permit the escape of either clotted blood or debris of injured tissue.
The after-treatment of excisions demands, first of all, physiological rest of the part involved, especially if, as at the knee, sutures or other expedients for maintaining apposition have been inserted. When motion is sought there will soon come a time when passive motion can be begun. This will vary with the size of the joint and the magnitude of the procedure. Actual rest should be maintained until firm wound healing has been secured. Passive motion is then begun, to be practised daily, the sensation of the patient being the guide as to the range of the movement and extent of manipulation. Thus, after exsection of an elbow with prompt union of the wound passive motion should be begun in about two weeks, but it should not be begun for a month if the joint has been thoroughly disorganized and the cavity is still discharging. Motion should be begun as early as is considered feasible in order to guard against a false joint.
The remote consequences of joint excisions are usually very satisfactory. The best results are obtained in the young, i. e., those whose tissues are still undergoing natural changes and whose bones are growing. In the course of time, by condensation of surrounding tissues, a new joint capsule is formed, its interior smoothed off, apparently covered with endothelium and filled with a sufficient amount of fluid, similar to that of normal joints, to serve the purpose; in this way a new joint becomes gradually substituted for the old, which serves the original purpose, in a surprising and gratifying way. Even in those of advanced years a satisfactory result is often obtained. It is often necessary to afford some support, by which too great a range of motion may be avoided; thus at the elbow the result at first is what may be called a “flail-joint,” which permits much undesirable lateral movement. This can be avoided by having light leather corsets fitted to the forearm and arm, connected by two lateral hinged braces. This being constantly worn, and no motion permitted which is not an imitation of the normal, the parts in time adapt themselves to the purpose, so that all apparatus can after a while be removed.
Excisions, like amputations, may be practised and the general methods learned on the cadaver, but their actual performance in the presence of extensive disease will be found to be a different procedure from that learned upon the dead body. For reasonably representative cases typical operations can be devised, with explicit directions. It is not advisable to try to do such work through too short incisions. A long incision heals as kindly as one shorter and affords more room for operative work. The incision should be so planned and executed as to afford the maximum of exposure with the minimum of damage to important structures. The region of the great vessels is avoided in all the classical operations, while nerve trunks, if exposed, are retracted and kept out of harm’s way. After the knife has once laid open the joint it is used but little except for the division of resisting structures, e. g., ligaments. The greater part of the work is then done with elevators, or periostomes with reasonably sharp edges and sufficiently broad surface, so that the periosteum can be divided with the latter and separated with the former to the necessary extent. Obviously epiphyseal junctions should be spared whenever possible, especially in the young. To remove an entire epiphysis is to materially impair the later growth of the limb. In some of the most serious cases it will be found already loosened and lying as a sequestrum in the joint cavity. In this case it may be easily lifted out of place. Tendons should never be divided unless absolutely necessary. Incisions in their neighborhood should be so planned as to be parallel with their direction and permit their displacement without division. The sharp spoon should be employed for curetting the interior of a joint capsule or cleaning out a bone focus (erasion). A capsule involved in tuberculous disease should be completely extirpated. Diseased bone ends should be sufficiently exposed to permit of the use of an ordinary saw or a chain or wire saw.[34] Considerable force will often be necessary in making bone ends accessible for this purpose. The chisel is rarely used except in cases of bony ankylosis, where it is not possible to force bone ends through the opening in order to attack them with the saw. As remarked above, clean cases may be closed without drainage. Visible vessels should be secured, and, while a certain amount of oozing may be expected, if the part be enclosed in suitable compressive dressings and elevated, it need not cause alarm. The gentle application of an elastic bandage for three or four hours may afford additional security. It should not, however, be allowed long to remain. The terminal portion of the limb will always afford an indication as to the condition of the circulation. Should it become cyanotic or cold the dressing should be renewed and the wound examined promptly.
Special Incisions.
The Shoulder.
—A longitudinal incision suffices for most cases (Fig. 214). This may be made posteriorly between the fibers of the deltoid or anteriorly and externally over the bicipital groove. It is better to separate the deltoid fibers than to divide them, although they may be divided. Should the straight incision afford insufficient room another incision at right angles will afford ample access. The capsule, having been exposed, is opened, the wound widely separated with retractors, the arm rotated through a wide arc, while with a stout knife the capsular ligament and the various muscular attachments around the neck of the bone are divided. The greater and lesser tuberosities, with their muscles undivided, should be retained, when circumstances permit. The head of the bone, being freed, is dislocated and forced out through the wound, where it may be seized with large forceps and removed with a saw. The higher the bone is divided the better. Every other consideration, however, should be sacrificed to removal of all foci of disease. The capsule may then be extirpated and the glenoid cavity thoroughly cleaned out with a sharp spoon. Should the case be one of serious infection it is advisable to make a posterior opening, even through the deltoid, for purposes of thorough drainage. The greater part of the first incision is to be closed with sutures, the arm dressed in a comfortable position, with the elbow at a right angle, and the patient allowed to be up and around as soon as he feels in the mood for it.
Fig. 214
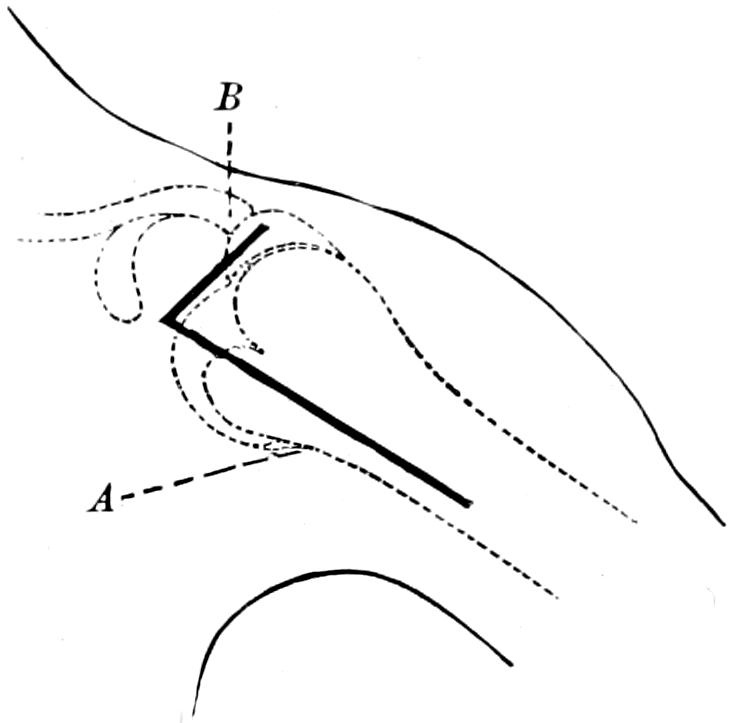
Excision of the shoulder: A, regular incision; B, supplementary. (Ollier.)
The Elbow.
—Here a variety of methods have been advised, and the extent of the operation must depend, to some degree at least, on the nature and extent of the condition which necessitates it. Partial excisions have been recommended, though in the writer’s experience incomplete operations often give less satisfaction than those which are complete. However, when it is a question of removing callus or displaced bone fragments, which, after fracture into the joint, impair its function, then partial resections may be serviceable.
Fig. 215
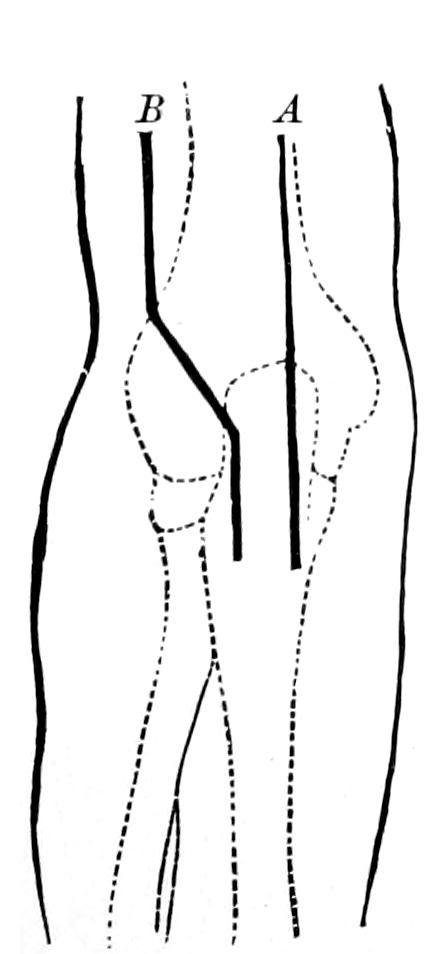
Fig. 216
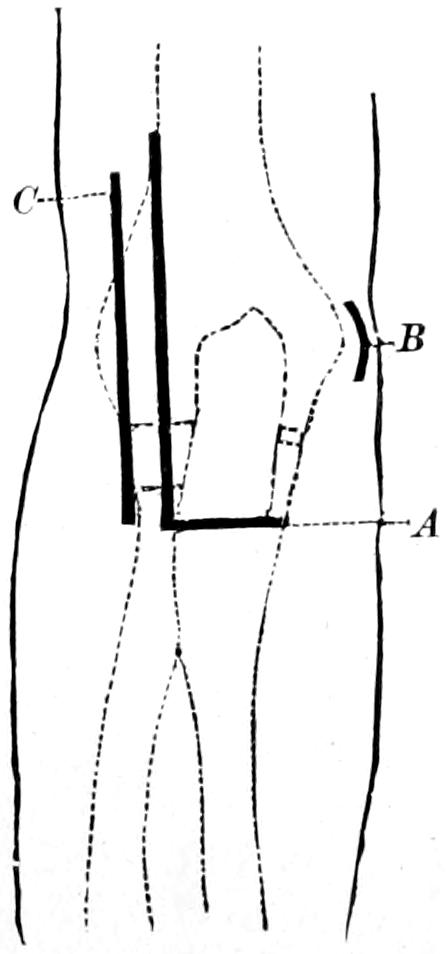
Fig. 217
Excision of the elbow-joint: A, von Langenbeck; B, Ollier.
Excision of the elbow-joint: A, Nélaton; B, C, Hueter.
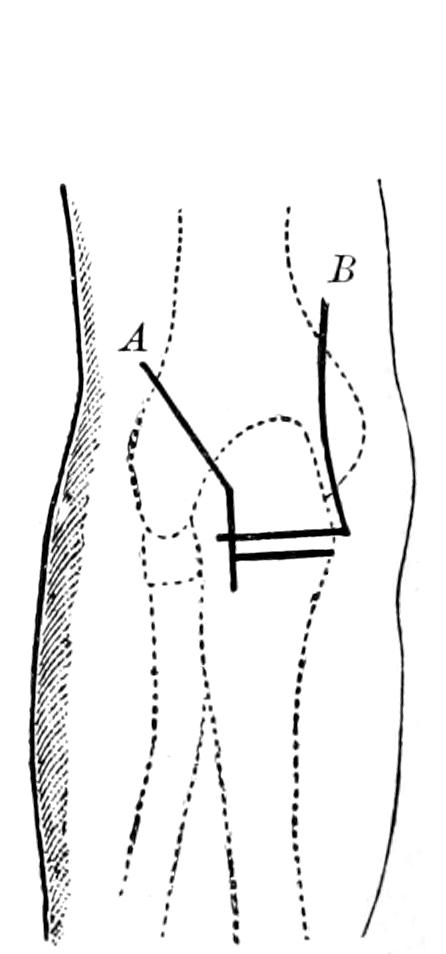
Osteoplastic method: A, by external incision; B, von Mosetig-Moorhof.
The essential incision is a long posterior one, which may be somewhat modified (Figs. 215, 216 and 217). It is essential here to avoid the ulnar nerve, which passes between the internal epicondyle and the olecranon, and the vessels and nerves in front of the joint. If it be made an inviolable rule to always keep close to the bone both of these dangers may be avoided. Ligamentous and muscular structures, among the latter the anconeus, should be spared as much as possible. After separating the joint surfaces thoroughly, by forced flexion, it is usually easier to force out the lower end of the humerus and first remove it, after which the upper ends of the radius and ulna are exposed and removed. When there is bony ankylosis it is preferable to divide the bones of the forearm first. The tendon of the triceps is not only detached from the olecranon, but divided by the first long incision. After concluding the incision, the capsule, if it remains, is to be closed with chromic catgut sutures and the end of the triceps tendon or some of its periosteal attachment united to the periosteum of the upper end of the ulna.
The arm is now fixed in the right-angle position and held comfortably to the body by a suitable sling.
The Wrist.
—It is rare that in disease of the wrist-joint this is found to be limited to a single bone of the carpus. Should an x-ray examination indicate such limitation then the focus can be exposed and cleaned by an incision upon the dorsum of the wrist, where it may seem best adapted for the purpose. Suppurative and tuberculous affections of the wrist usually necessitate removal of the carpal bones, including, possibly, the lower extremities of the ulna and radius. When the wrist-joint is involved it may be sufficient to remove the latter with the first row of the carpus.
Fig. 218 illustrates the incisions to be recommended for wrist resection, of which the Langenbeck line is to be preferred. Occasionally two lateral incisions, with through drainage, will better serve the purpose. It may be necessary to divide the short radial extensor, but this may be united again with suture. In most instances it is possible to retract the tendons to either side and thus clear the carpal region. By hyperextension the extensor tendons are relaxed and more room is thus made. The incision marked “A” combined with that marked “B” in Fig. 218, affords the best exposure when disease is extensive. The incision along the inner border of the wrist is made 5 Cm. above the styloid process of the ulna, and between the latter and the ulnar flexor down to the middle of the last metacarpal bone. Here the tendon of the latter muscle should be divided at its insertion and lifted out of its groove in the ulna. The collection of extensor tendons is then separated from the back of the wrist and lifted up, it being usually necessary to divide the unciform process of the unciform bone with forceps. The knife should be kept from the palmar surfaces of the metacarpal bones in order to avoid injury to the deep arch. After dividing the anterior radiocarpal ligament the carpus is extirpated through the ulnar incision. The ends of the ulna and radius are now easily accessible for removal with forceps or a metacarpal saw. The same is also true of the proximal ends of the metacarpals. After spreading the hand and forearm upon a flat splint drainage can be made to the desired extent and the wound closed.
Fig. 218
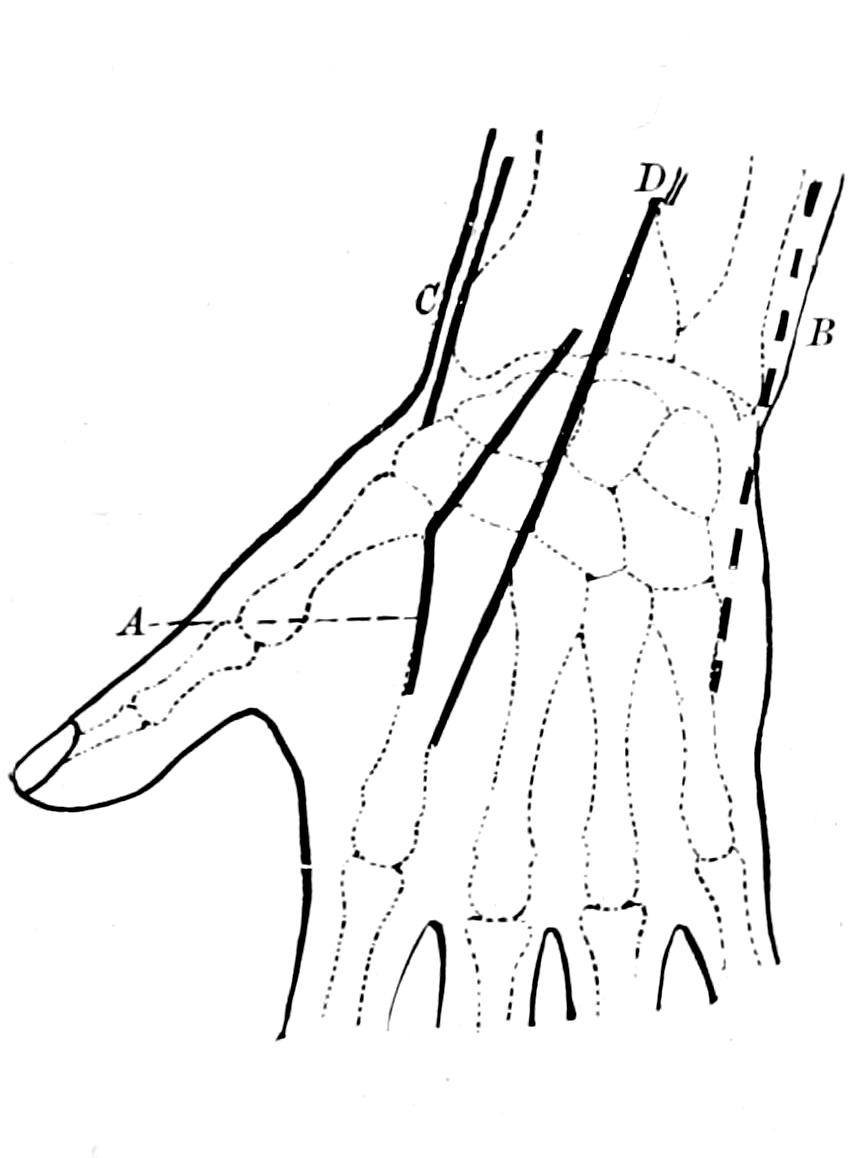
Excision of the wrist: A, Lister’s radial incision; B, Lister’s ulnar incision; C, Ollier; D, von Langenbeck.
Fig. 219
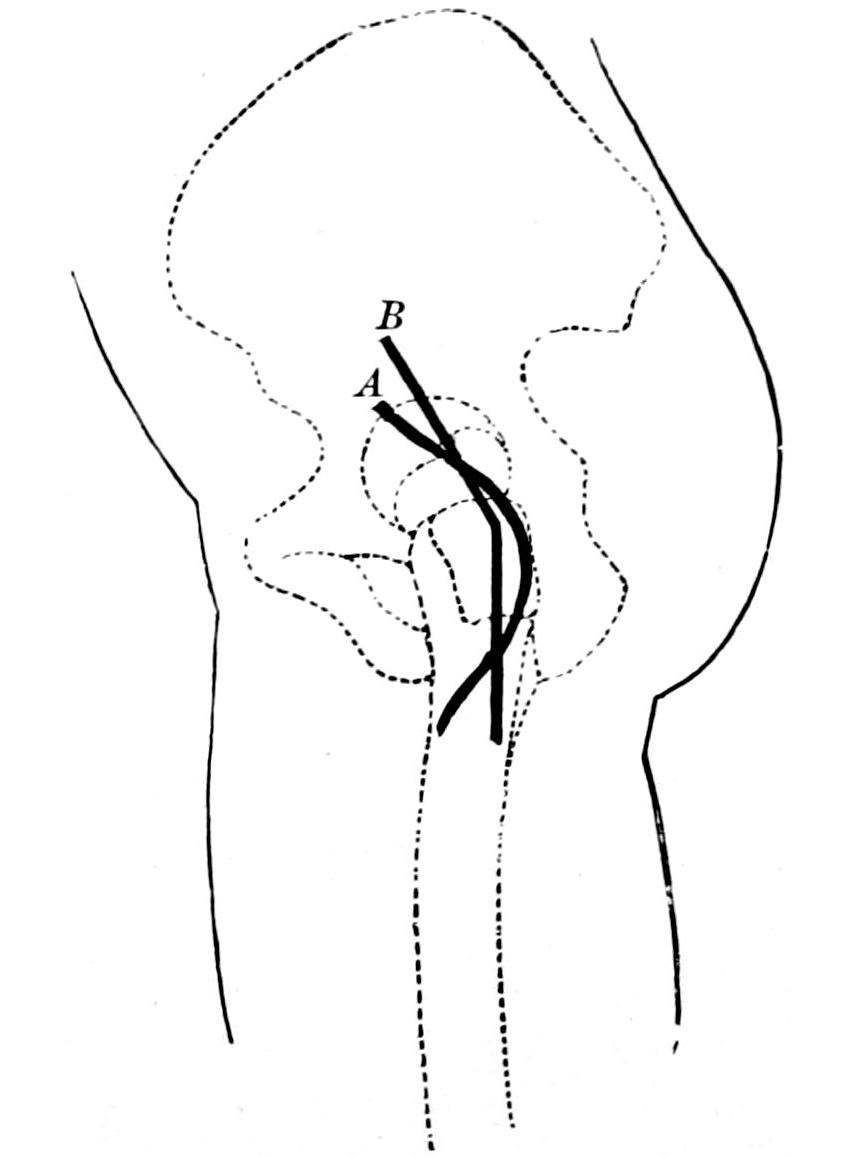
Excision of the hip: A, Sayre; B, Ollier.
So far as the hand and fingers are concerned little resecting need be done, the surgeon usually confining himself to the removal of sequestra or curetting of carious bone. In cases of compound comminuted fracture bone fragments may be removed; only in cases of lost or destroyed phalanges will amputation be necessary.
The Hip.
—In its structure the hip-joint is one of the simplest in the body. Although it lies deeply it is easily made accessible. Fig. 219 illustrates the incisions by which the joint is attacked for the purpose of exsection. If necessary either extremity of the incision can be extended or enlarged by a cross-cut. When the joint is disintegrated by disease, especially when partially dislocated, the parts will lend themselves to an easy and simple operation. When, however, the operation is done for ankylosis or for disease, by which great thickening and fixation have been produced, the measure may become difficult. For ordinary purposes the simplest method is to drive a sharp-pointed, strong-bladed knife directly down upon the neck of the bone from a point midway between the great trochanter and the crest of the ilium; then keeping the knife-blade in contact with the bone the incision is carried downward over the trochanter and along the shaft to a length making it sufficient for easy exposure of the bone and of the joint. Nothing is gained in these cases by trying to work through a short incision. A long one heals as readily and makes the operation more simple. It is as easy to make the entire incision in one cut as to divide the muscles layer by layer. The capsule of the neck of the femur being exposed by a wide retraction of wound margins, it is necessary next to divide muscular attachments to the great trochanter by raising the periosteum to which they are attached and saving both. To expose these insertions the femur should be rotated inward and outward, while the capsule is at the same time divided. The ligamentum teres, which offers a theoretical obstacle, usually disappears in the presence of any active disease and is scarcely ever encountered; it can be divided with curved scissors. Now by more or less powerful effort, including flexion and adduction to the extreme limit, with more or less rotation, the head of the bone is forced out from its socket and through the wound. Whether the bone should be decapitated with chain saw, metacarpal saw, or by the exsector of Wyeth will depend partly upon the freedom with which it can be exposed and on the equipment of the operator. It may be advisable to divide the neck with a chisel. The trochanter major should be preserved whenever its removal is not made imperative by the progress of the disease. The head and neck of the bone having been removed, the acetabulum is now more or less easily exposed, especially with retractors, and it should be cleaned with a sharp spoon. The capsule also should be removed, at least when the operation is done for tuberculous or other infectious condition. It is advisable to irrigate, then to wipe dry all the original joint surfaces and raw bone, and finally to cauterize either with pure carbolic or with zinc chloride, which should be washed away with the irrigating stream, the intent being to close the mouths of all the absorbents and prevent absorption from fresh exposure. Sinuses if present should be thoroughly excised, scraped, and treated in the same way. A drainage tube is usually preferable to the use of gauze.
The above is the method usually relied upon for hip exsection. Other methods have been devised, especially by anterior incision; of these the best probably is that of Barker. The cut is made along the outer border of the anterior surface of the sartorius and rectus, and through it the femoral neck is reached. By wide retraction the anterior surface of the joint can be completely exposed and opened, and through this opening the neck of the femur can be divided with a chain saw or chisel, before removal of the head from the acetabulum. The disadvantage of anterior incision is that pertaining to drainage. Nevertheless this can be obviated with capillary drains. Its advantages are that splinting and protection can be more perfectly effected, with less necessity for frequent interference. In other words it makes the subsequent care of the patient easier. Many English surgeons are in favor of it. Ollier devised a so-called osteoplastic excision, made through a curved incision with a downward convexity, the top of the great trochanter being exposed and divided with a chisel sufficiently to permit of its being turned up with the flap, and then being reunited to the main part of the bone after the removal of the neck and head. This method has its advantages in a limited number of cases, but it has not become popular in this country. It would seem to be an advantage to preserve the trochanter, although some surgeons remove it. So long, however, as disease is confined to the head and neck of the bone it is unnecessary to remove this projection.
The after-care of a hip excision is not an easy matter. Most surgeons prefer to maintain the limb in position by the aid of traction, with sufficient weight to overcome all muscle spasm. If the case be such that dressings need only be made at long intervals, then it matters little, but in a septic case in which there is considerable discharge the problem is sometimes a serious one. Various beds or suspension splints have been devised, consisting essentially of frames with cross-strips of stout material, upon which the patient lies. After raising the frame one or two of these strips are released and the parts exposed. This arrangement also permits of the easy management of a bed-pan. In young children a wire splint with a fenestrum, or a plaster-of-Paris spica or breeches with large opening cut opposite the wound, will often be serviceable. The tendency is rather toward adduction, and this should be overcome. Something will depend upon whether the surgeon is working for ankylosis or for a movable joint. In the former case a rigid dressing should be employed as soon as the condition of the wound permits. In the latter passive movement should be begun as soon as the wound is healed.
While the operation is usually performed quickly, and is not regarded as serious, it nevertheless has a considerable mortality, especially in the young and the aged, because of the conditions which necessitate it. After a complete exsection, even by the most ideal method and in the most ideal case, the limb remains somewhat shortened. This may be compensated by raising the heel of the shoe worn on the affected side. In severe cases it may be necessary to supply even two or three inches of artificial support for this purpose. Unless this is done compensatory spinal curvature will ensue.
Fig. 220
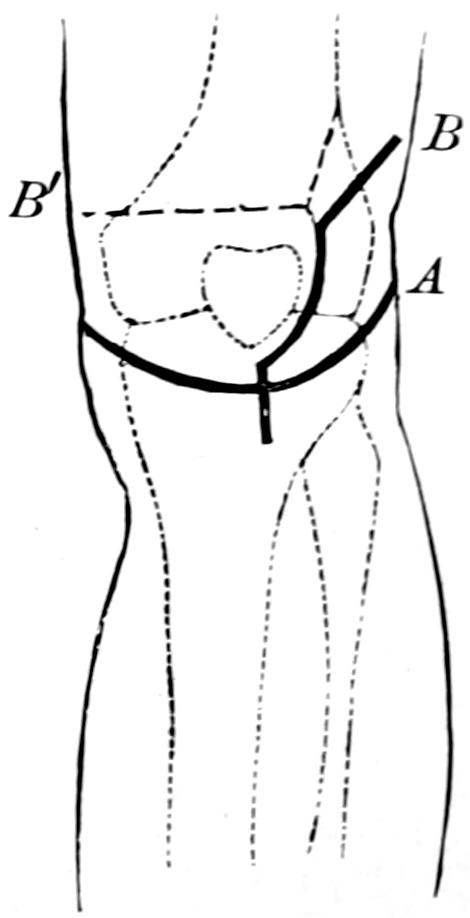
Excision of the knee-joint: A, semilunar incision; B, Ollier’s incision.
The Knee.
—The knee is generally more accessible for operation than the elbow, as the important structures which should not be disturbed lie grouped upon its posterior aspect. Protection for one of these is protection for all, and the freedom with which the joint may be opened makes it especially easy to do either complete or partial operation. Here the surgeon should endeavor to preserve the epiphyses, especially in children, as they have much to do with the growth and length of the limb. So long as incision is confined to the anterior aspect of the joint it can be made in almost any manner. The usual method is that represented by line A in Fig. 220, by which a horseshoe flap is raised and the joint interior exposed. Occasionally the direction of the flap is reversed, and it is turned downward rather than upward. In the former case the ligamentum patellæ is divided; in the latter, the tendo patellæ. Whichever way the flap is turned it is made to include the patella, although this bone can be removed at any time. The lateral ligaments being divided, as well as the crucial, and the limb completely flexed, exposure of the joint surfaces is made. It is now possible to do an arthrectomy, a partial exsection or a complete one, according as the disease is more or less extensive. In the complete operation the articular surfaces of the femur and of the tibia are usually removed with an amputating saw. If this be introduced from the front and made to work its way backward the popliteal vessels should be amply protected against possible injury. Here it should be borne in mind that the leg is not constructed in a straight line, but that there is a lateral angle at the knee, as the femurs diverge as they pass upward, and this angle should be imitated in directing the saw and removing the bone end. Again, a slight bend anteriorly will make the limb more useful than one which is absolutely straight. The intent thus should be to give the knee at a slight angle anteriorly and interiorly, and the saw should be manipulated with great care. In a complete operation the patella is also removed. In tuberculous and other septic disease the capsule should be completely extirpated. This offers no difficulty, save at the posterior surface, where it may approach closely to the region of the great vessels.
Various modifications have been practised in these operations. Some open the joint by straight cross-incision with division of the patella, the latter being reunited with tendon or wire sutures. Others have practised a more complicated H-shaped incision, the transverse portion being carried either through the patella or just below it. The line marked B in Fig. 220 was suggested by Ollier. It is questionable whether any of these methods offer any advantages over the one first described.
After exsection it is desirable to maintain the bone ends in an accurate position if speedy reunion be desired, and for this purpose various methods are in vogue. The bones may be drilled and fastened together with tendon or wire sutures, or ivory nails may be driven in, one on each side, directing them obliquely, so that displacement cannot easily occur, or metal nails may be used for the same purpose. Another plan is to insert two long metal drills, one on either side, which perforate the skin two or three inches above the wound, and are passed downward and toward the other side so as to fix the surfaces, as it were, by a cross-forked arrangement. After two or three weeks these drills may be withdrawn. Fixation of this kind is advantageous, for when complete excision has been practised the surrounding tissues are lax and the parts are not easily held in position by external dressings alone. In a clean case, with careful hemostasis, very little drainage will be required. What is needed can be provided by an absorbable drain passed through the lower portion of the wound on either side. In a septic case it would be well to provide for ample drainage on each side.
The limb may be dressed upon a fenestrated wire or gauze splint, which is easier when frequent change of dressing can be foreseen, or it may be immobilized in a plaster-of-Paris splint.
The Ankle.
—The ankle is usually reached by an incision on either side, three or four inches in length, extending from above each malleolus downward and forward on to the tarsus. The knife-blade should be forced to the bone, so as to divide the periosteum, which is subsequently separated and lifted by an elevator, in order that the operation may be made subperiosteally. The fibula is usually first divided, with a chain saw or a chisel, an inch above its tip. The divided fragment is wrenched from its place with forceps, and severed from the ligaments by knife or scissors, being careful not to injure the external lateral ligament. The inner incision is made in practically the same way, the periosteum separated, the internal lateral ligament divided, and the end of the tibia forced through the incision by everting the foot. Its joint end may be removed with a saw, dividing on the same level and plane with the lower end of the fibula. Through the gap thus made the astragalus may be either removed or its upper surface divided with a metacarpal saw. The fresh bone surfaces left in this way will unite and ankylosis will result, unless fibrous or muscular tissue be interposed to favor the formation of a false joint.
As in other operations methods may be varied to meet the exigencies of certain cases. Longitudinal incisions may be placed farther forward than indicated above, as is shown in Fig. 221, which illustrated König’s method. Here the bone surfaces are divided with broad chisels. A transverse incision of the front and upper part of the ankle may be made, through which the tendons are exposed, lifted in a group out of harm’s way, and curetting and bone sawing performed. Kocher makes a semilunar incision from the outer border of the tendo Achillis to the outer border of the extensor tendons, its line passing beneath the external malleolus. By this method the joint is opened and the peroneal tendons divided, their ends being reunited after the completion of the balance of the work. This method is usually applicable in children.
Ample drainage is required in these cases, for the operation is seldom performed in the absence of septic complications. The foot should be kept in proper and right-angled position by metallic splints, or by plaster of Paris, the latter preferable, fenestra being cut in order to make access to the wound.
Excisions of the Tarsus and Osteoplastic Excision of the Heel.
—Removal of the tarsal bones is confined usually to cases of tuberculous disease, and may be performed by a variety of methods. Thus the tissues of the sole of the foot may be divided transversely by an incision carried from the tubercle of the scaphoid beneath the sole and across to a point one inch behind the base of the metatarsal. Through this, access can be made to the inferior surface of the tarsus. Conversely the upper portion may be exposed by a similar transverse incision across the dorsum of the foot, by lateral incisions, or by a combination of both. It is seldom necessary to divide the tendons, it being nearly always possible to gather them into a group and lift them out, while the bones are attacked with a sharp spoon or a chisel.
Occasionally the calcis becomes involved in cancerous or tuberculous disease and it would appear that removal of the heel proper would be all that is required. To meet these indications Wladimirov, in 1871, and Mikulicz, in 1880, independently devised a method by which the ankle-joint may be opened and as much of the heel and adjoining tarsus as necessary removed, the foot being later fixed in the extreme equinus position. This is referred to as osteoplastic excision or amputation of the heel. Fig. 222 illustrates the line of incision, which extends from the tubercle of the scaphoid beneath the heel to a point on the opposite side, then obliquely upward and backward to the base of each malleolus, and then transversely and posteriorly, thus including within its line the region of the heel. These incisions extend to the bone, the ankle-joint is opened posteriorly, the lateral ligaments divided, the lower extremities of the tibia and fibula removed with a saw, the astragalus and calcis separated from their attachments, and the posterior articular surfaces of the scaphoid and cuboid also removed. The lines of division of bone are indicated by dotted lines in Fig. 222. Thus the lower ends of the leg bones are brought into contact with the upper end of the divided tarsus by straightening the foot in the extreme equinus position and maintaining this position with wire sutures or bone or metal pins.
Fig. 221
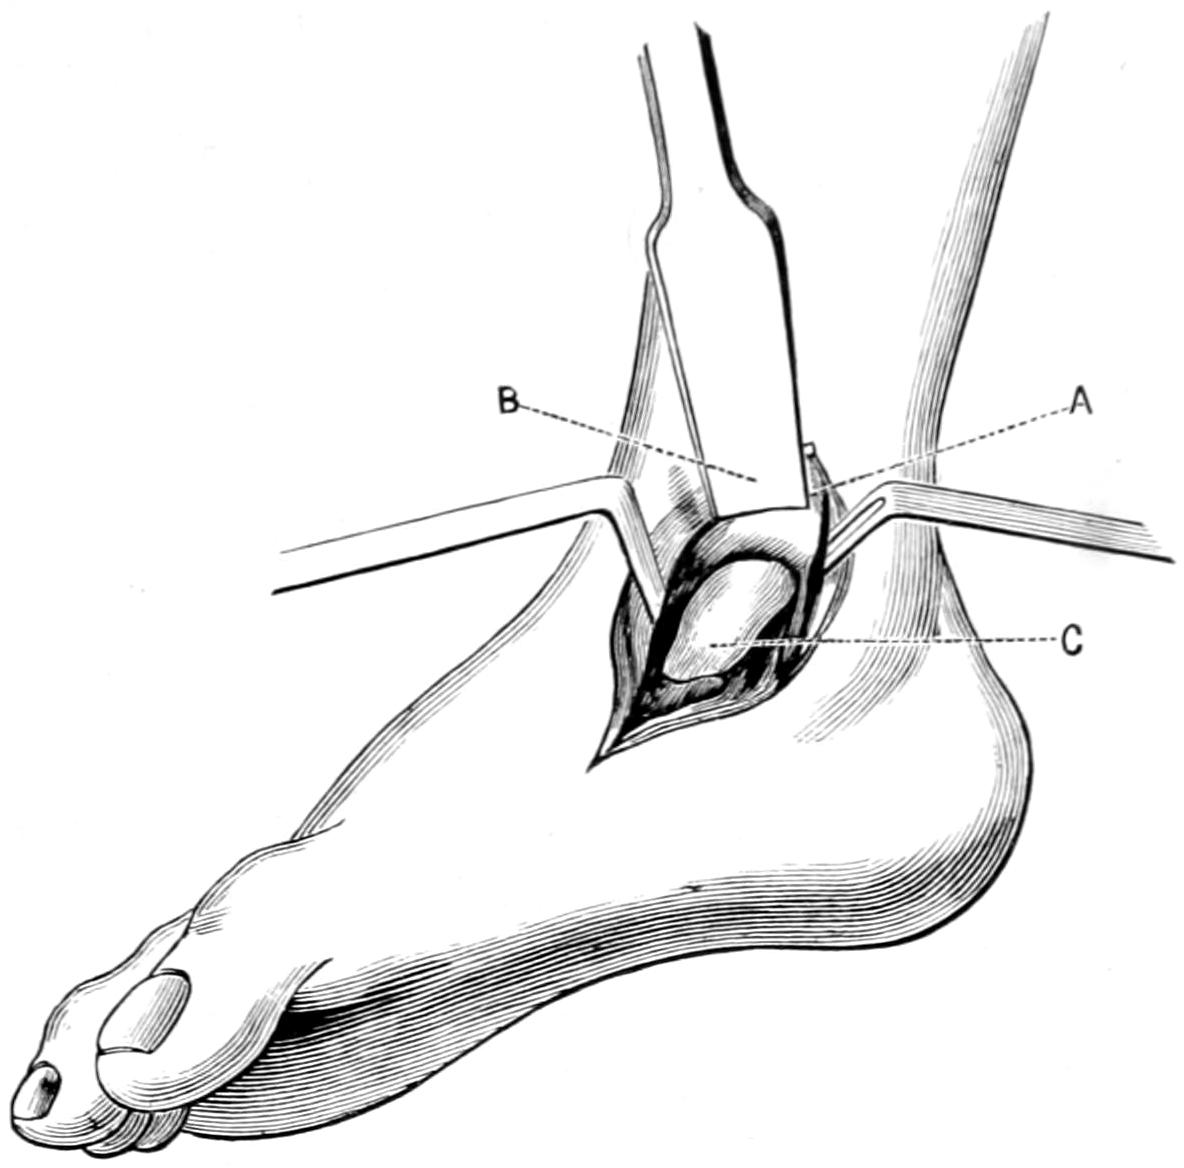
König’s incision for excision of the ankle.
Fig. 222
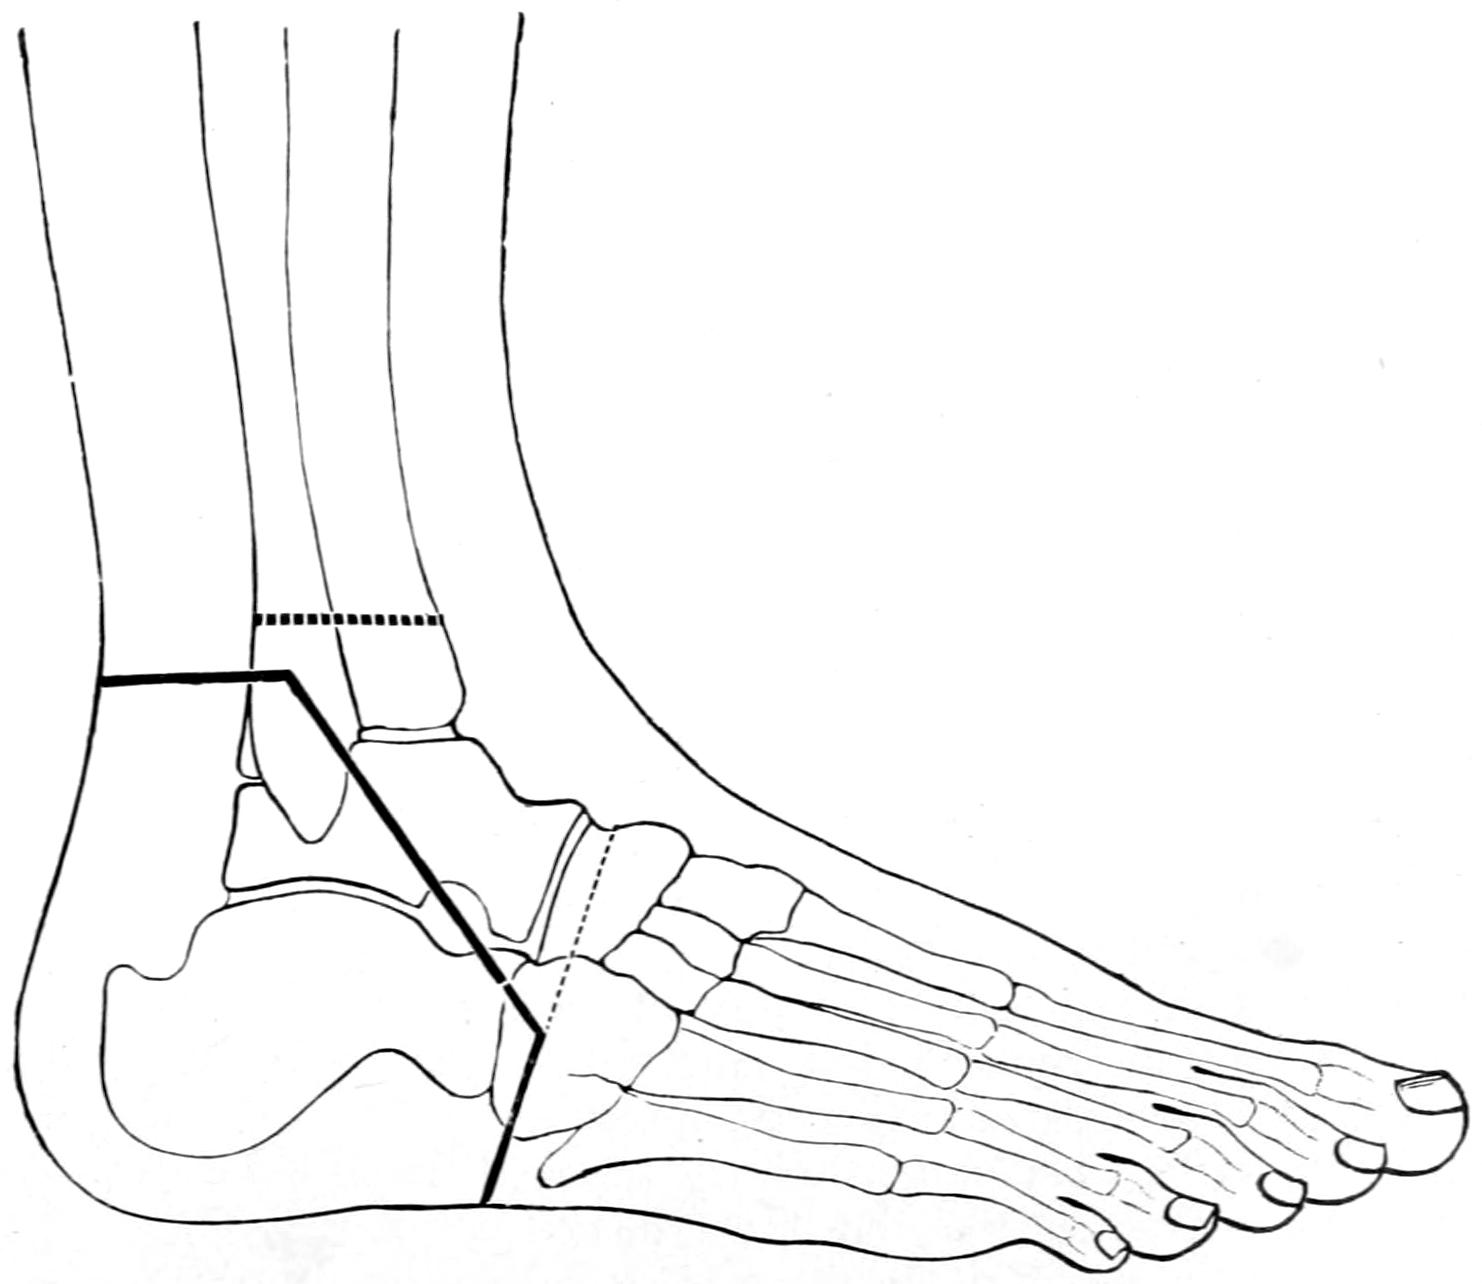
Osteoplastic excision of the foot. (Mikulicz.)
The cases in which this method is of use are rare, but when indicated it has usually given satisfactory results. It is a substitute for amputation of the leg, and it is often an open question as to which will give the most satisfactory result. It has probably not been practised a hundred times.