Part 5 — CHAPTER XXVI. CYSTS AND TUMORS.
Reading edition
GENERAL CONSIDERATIONS.
A tumor is a new formation, not of inflammatory origin, characterized by more or less histological conformity to the tissue in which it has originated, and having no physiological function.
By the above definition it is intended to separate the new-growths from a distinctive class of neoplasms which are of inflammatory (i. e., of infectious) origin, to which the generic term of infectious granulomas has been given. (See Part II.)
Exceedingly vague notions have prevailed concerning the nature and origin of tumors, and, while the clinical observations of writers in the past will never lose their value, the ideas which have prevailed concerning their pathology constitute interesting reading in a historical sense, but are now of small value. Accurate notions scarcely prevailed until Virchow demonstrated that tumor cells nowise differ from cell types which are met either in embryonic or in adult tissues. Tumors, like all other parts of the body, are built up of cells, and the points concerning which we need most light regard the influences which determine cell overproduction in these characteristic forms. Concerning the views that have prevailed, this is scarcely the place in which to offer an epitome. I shall therefore take up but few of the explanations which have been offered to account for tumor growth, and will emphasize that, according to our present light, there is no explanation sufficient to cover all cases, but that it is now one cause and now another which may determine this peculiar form of cell activity.
Irritation and Trauma.
—The effort is often made to explain the presence of tumors upon the hypothesis or the known fact of some previous injury. Frequently tumors appear in sites where there have been previous traumatisms, but this sequence of events by no means proves a definite relation of cause and effect. On the other hand, there are forms of irritation which are often followed by tumor formations. Probably no woman escapes without one or more bumps or bruises upon the breast, yet they do not produce tumors in more than a trifling proportion of cases. Per contra, upon the lower lip of inveterate clay-pipe smokers and the scrotum of chimney-sweepers there develop certain forms of malignant ulcer (epithelioma) which so often and so significantly follow upon the irritation thus produced that it is impossible to avoid conviction that one is the cause of the other. Should events prove the parasitic nature of any of these growths they will also prove that the irritation causes surface lesions through which infection easily occurs. In regard to the relative frequency with which cancer in some form follows trauma we should not forget the well-known fact that traumatism usually diminishes tissue resistance. If cancer be an expression of infection, as many (including the writer) believe, the possible relation between trauma and malignant disease may be better appreciated.
Inflammation.
—This refers to inflammation in the sense in which it has been used in the past, implying a variable condition, sometimes including and sometimes excluding infection, the term covering a confused mixture of irritation, hyperemia, and infection. In so far as it concerns inflammation as considered in the present work it should not be here included, since inflammation (i. e., infection) produces neoplasms of a class considered in Part II and is distinctly ruled out from present consideration (i. e., the infectious granulomas).
If inflammation in the former sense be more than hyperemia it may be regarded as predisposing to cell activity, but not necessarily to tumor formation as distinguished from hypertrophy of a given part or tissue. If it refer to irritation, this has been acknowledged as a factor in the etiology of tumors, but as an uncertain one. Cancer of the gall-bladder or liver, which occasionally results from the irritation of a gallstone, or the cancer of the breast that follows eczema of the nipple, may be regarded in this light as additional illustrations if it is preferred to interpret them in this way. If by inflammation be meant the infectious granulomas, they have already been considered. As the term “inflammation” can scarcely mean anything except hyperemia, irritation, or infection, we seem to have completely ruled it out from consideration as by itself an active cause leading to tumor formation.
The Embryonal Hypothesis of Cohnheim.
—This in its ingenuity and in its applicability is a fascinating explanation, which is undoubtedly sufficient for at least a certain number of instances. According to Cohnheim, only one causal factor for tumors exists—i. e., anomalous embryonic arrangement. He regards them as entirely of embryonal origin, no matter how late in life they may develop and appear. Briefly summarizing his views, they are to the effect that in the early stages of embryonal development there are produced more cells than are necessary for the construction of a certain part, so that a number of them remain superfluous. While these may remain very small, they possess, on account of their embryonal nature, a potent proliferating power. This superfluous cell material may be distributed uniformly, in which case it will develop whole system arrangements, like supernumerary fingers, etc., or it may remain by itself in one place, and will then develop a tumor. In the latter case the tumor may appear early or not until late in life, according to the time at which the cell collection receives the necessary stimulus, or because of its suppression by resistance of surrounding structures. It may be an irritation or an injury, such as above alluded to, which shall give it this stimulus; as, for example, it is reasonable to think that certain nevi and other congenital conditions which develop later into cancers do so in accordance with this view. Surgeons generally find little fault with Cohnheim’s hypothesis, except that as yet they decline to see in it an explanation for all cases. Nevertheless for dermoid and teratomatous, and for all heteroblastic tumors, it seems to afford the only tenable explanation. Thus chondromas of the parotid and of the testicle are most easily explained in this way, and that cartilaginous islands occur in the shafts of adult bones is well known.
Heredity.
—In regard to heredity being a factor in the etiology of neoplasms there is reason to believe that a favorable tissue disposition may be inherited, but there is nothing to show that it permits the actual transmission of the disease.
Parasitic Theory.
—The parasitic theory of tumor formation has only within a few years taken definite form and shape, as a result of evolution from vague suggestions and scattered observations. It implies that tumors, and they are mainly of the malignant type, are due to irritation produced by extrinsic agencies, parasites of some kind, which, introduced from without, act as do bacteria in the now well-known infectious granulomas. While this theory, perhaps, does not afford an absolutely satisfactory explanation of all the phenomena of malignancy, it nevertheless comes nearer to it than does any other hypothesis now before the profession, the arguments in favor of it being scientific and positive, and those against consisting mainly of mere negations. Summed up these arguments may be stated as follows:
1. Comparative Pathology.
—The argument from comparative pathology begins with the lower forms of life. Tumors in trees and plants are well known to vegetable pathologists and botanists as of frequent occurrence. They vary in size from the most trifling galls to those large woody masses known as xylomas, which are essentially tree cancers, since they tend to the destruction of the tree. These are known to be invariably due to extrinsic agencies, such as insects, fungi, etc. As water freezing in the bark of a tree may crack it open and thus leave opportunity for subsequent infection, so may injuries upon the body surface make trifling lesions which predispose to subsequent infection and cancer in man and animals. Exclude parasites from such traumatic lesions on plants and there will be no xylomas.
PLATE XIV
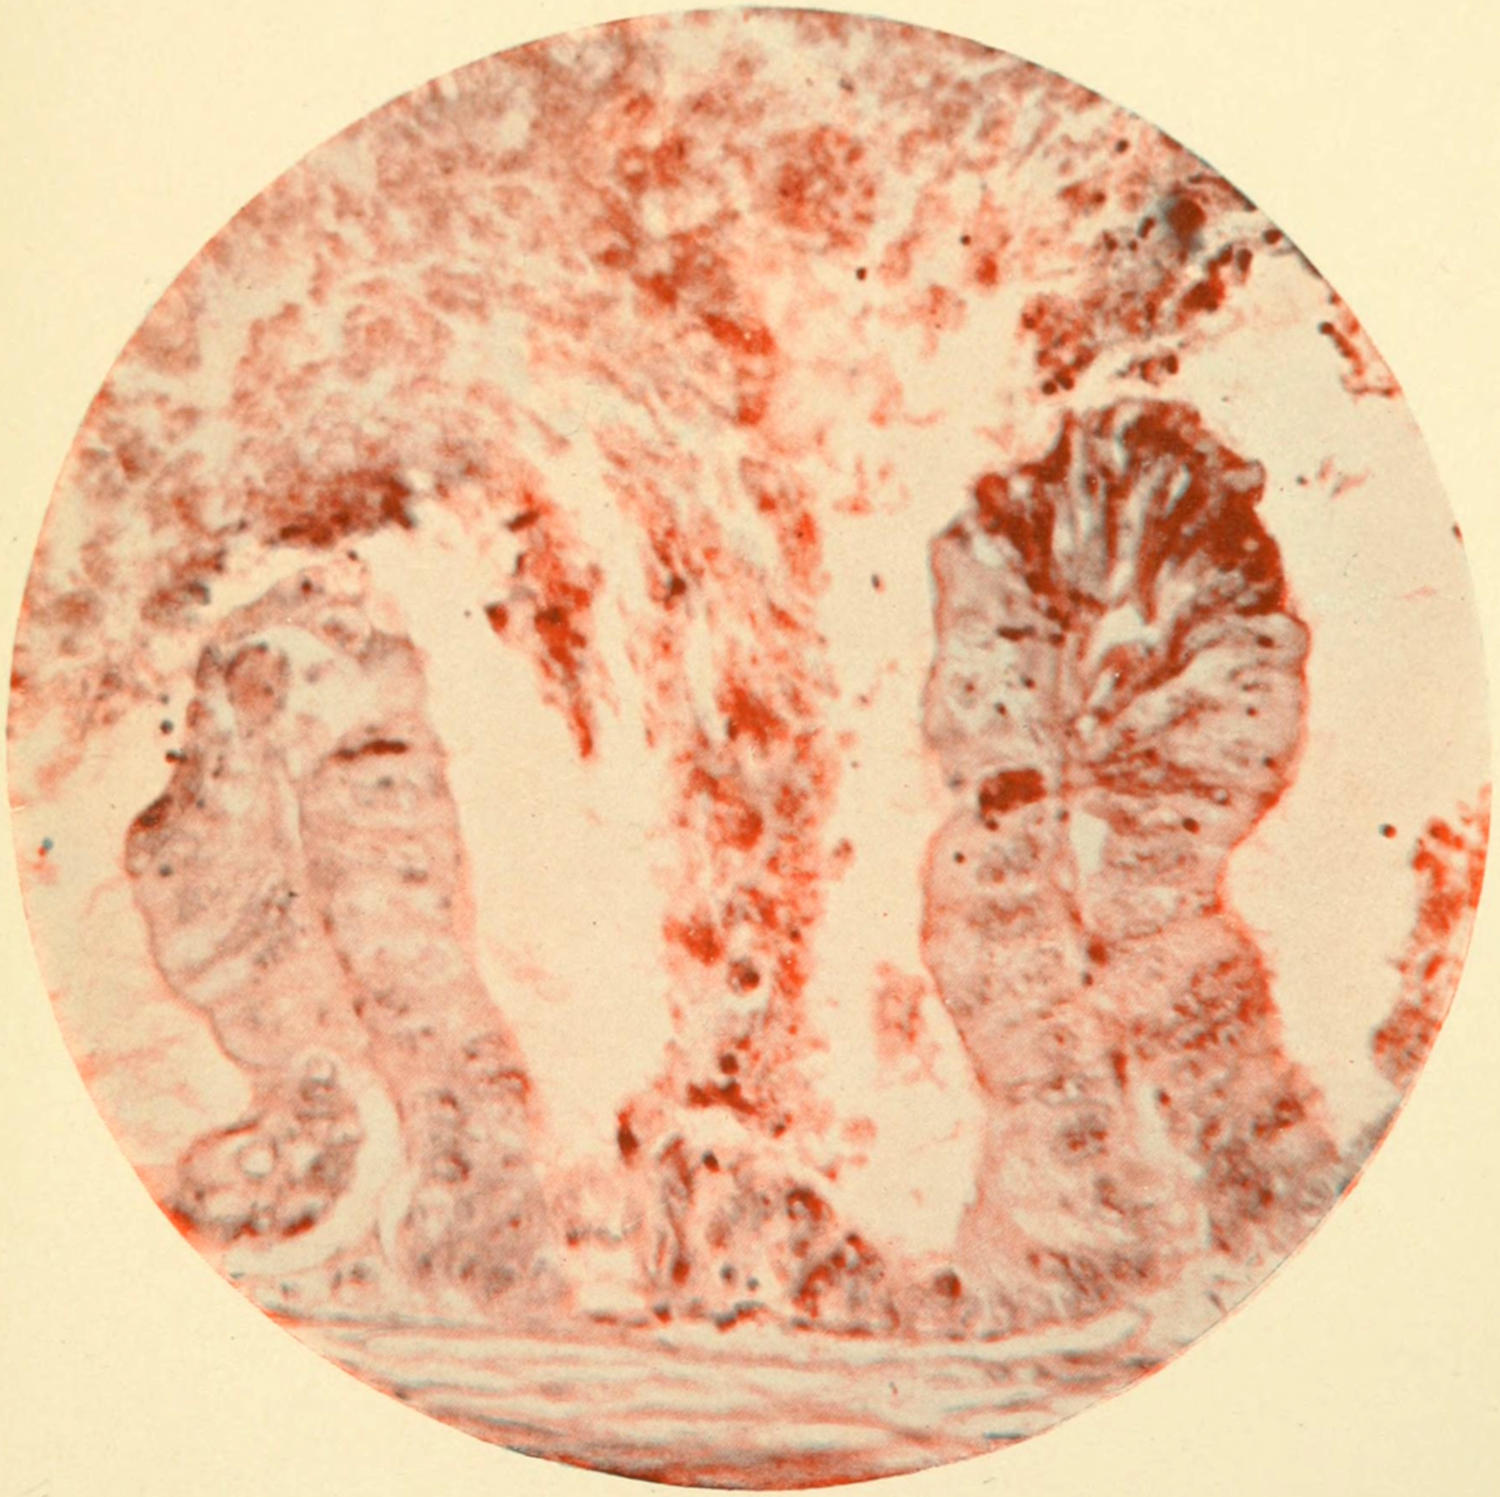
Adenocarcinoma with Young Parasites. (Parasites blue. Plimmer’s method.)
This plate is introduced to illustrate the presence of parasites, whose minute and actual character is not yet positively determined, but whose existence is undeniable.
From Gaylord’s paper in the Third Annual Report of the New York State Pathological Laboratory of the University of Buffalo.
PLATE XV
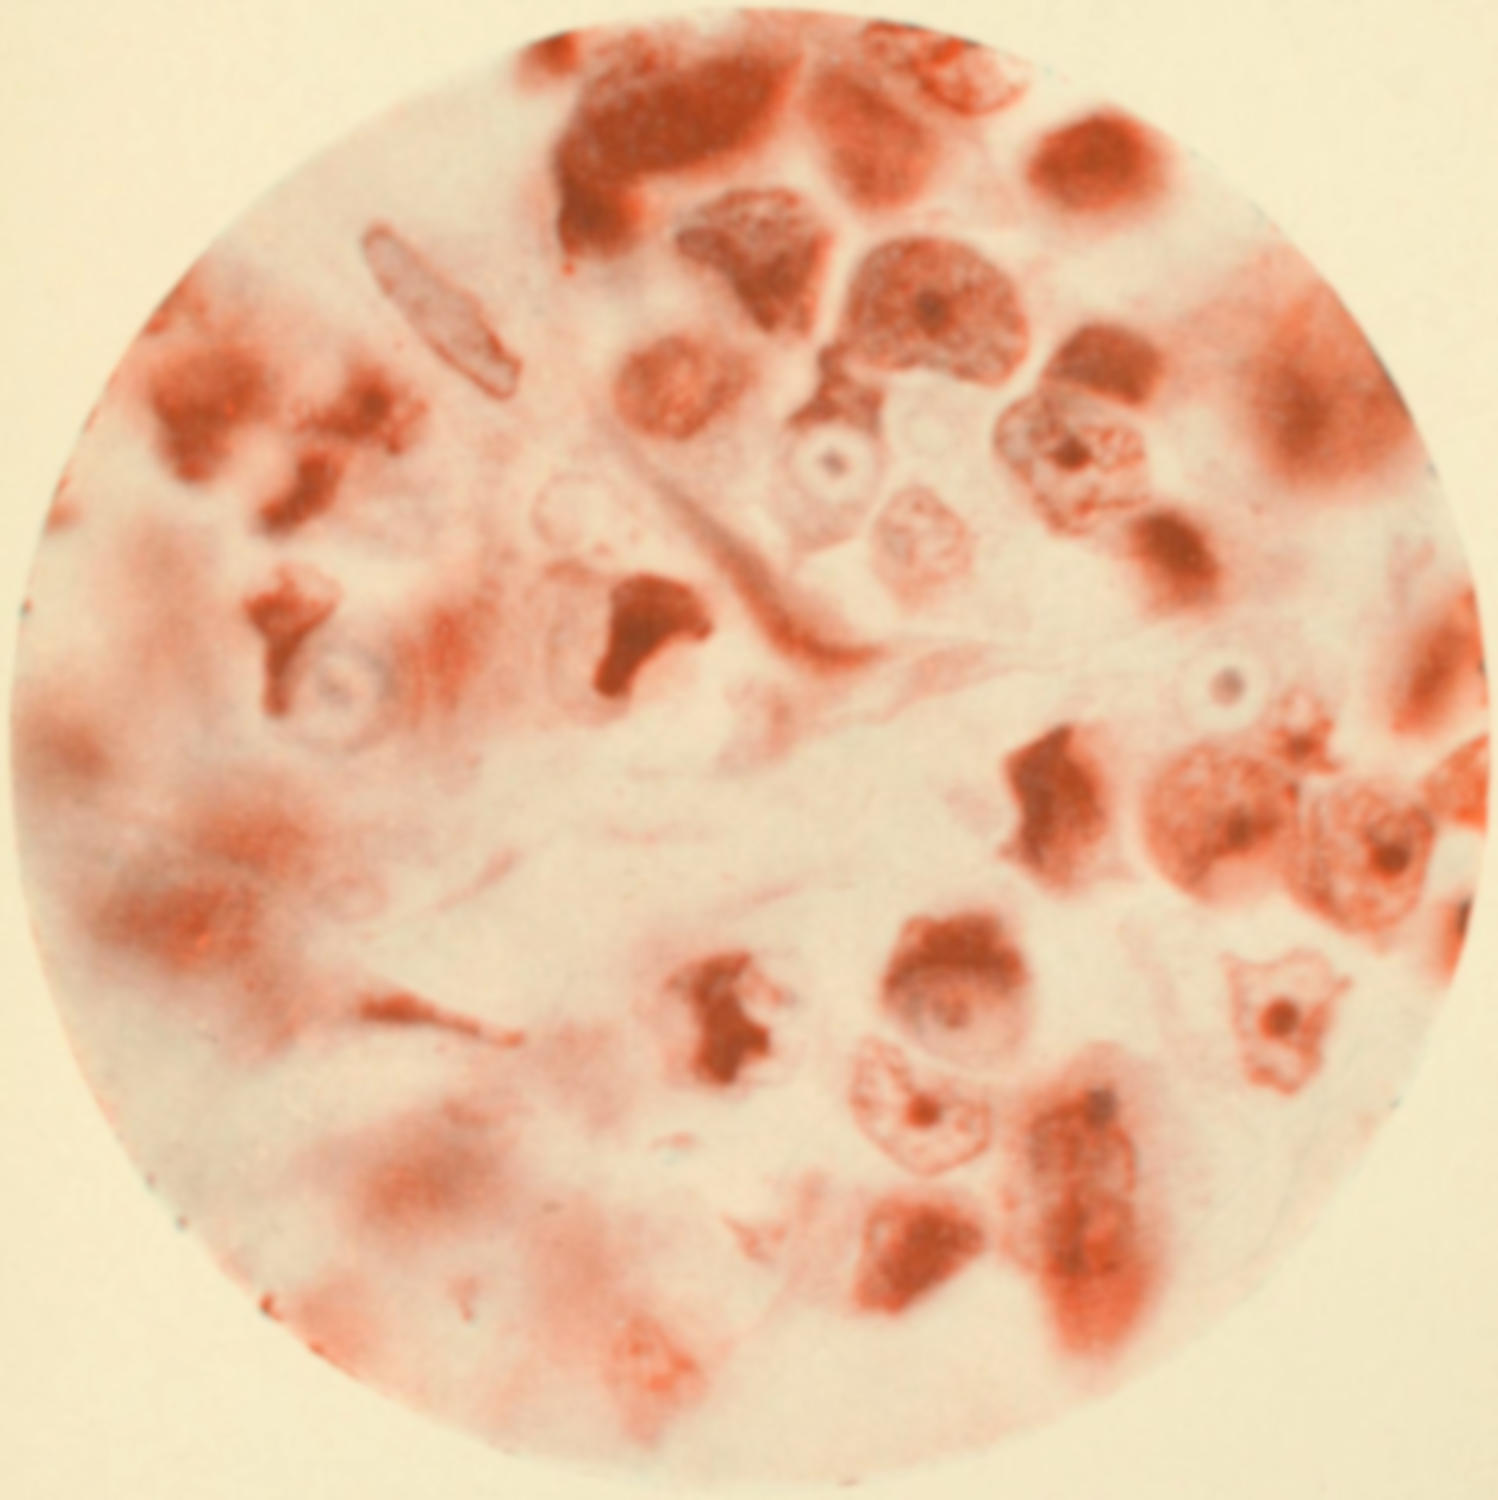
Rapidly Growing Carcinoma of Breast.
The parasites herein demonstrated are still subjects of careful and minute study. It would therefore seem premature to make detailed statements concerning their exact nature.
From Gaylord’s paper in the Third Annual Report of the New York State Pathological Laboratory of the University of Buffalo.
PLATE XVI
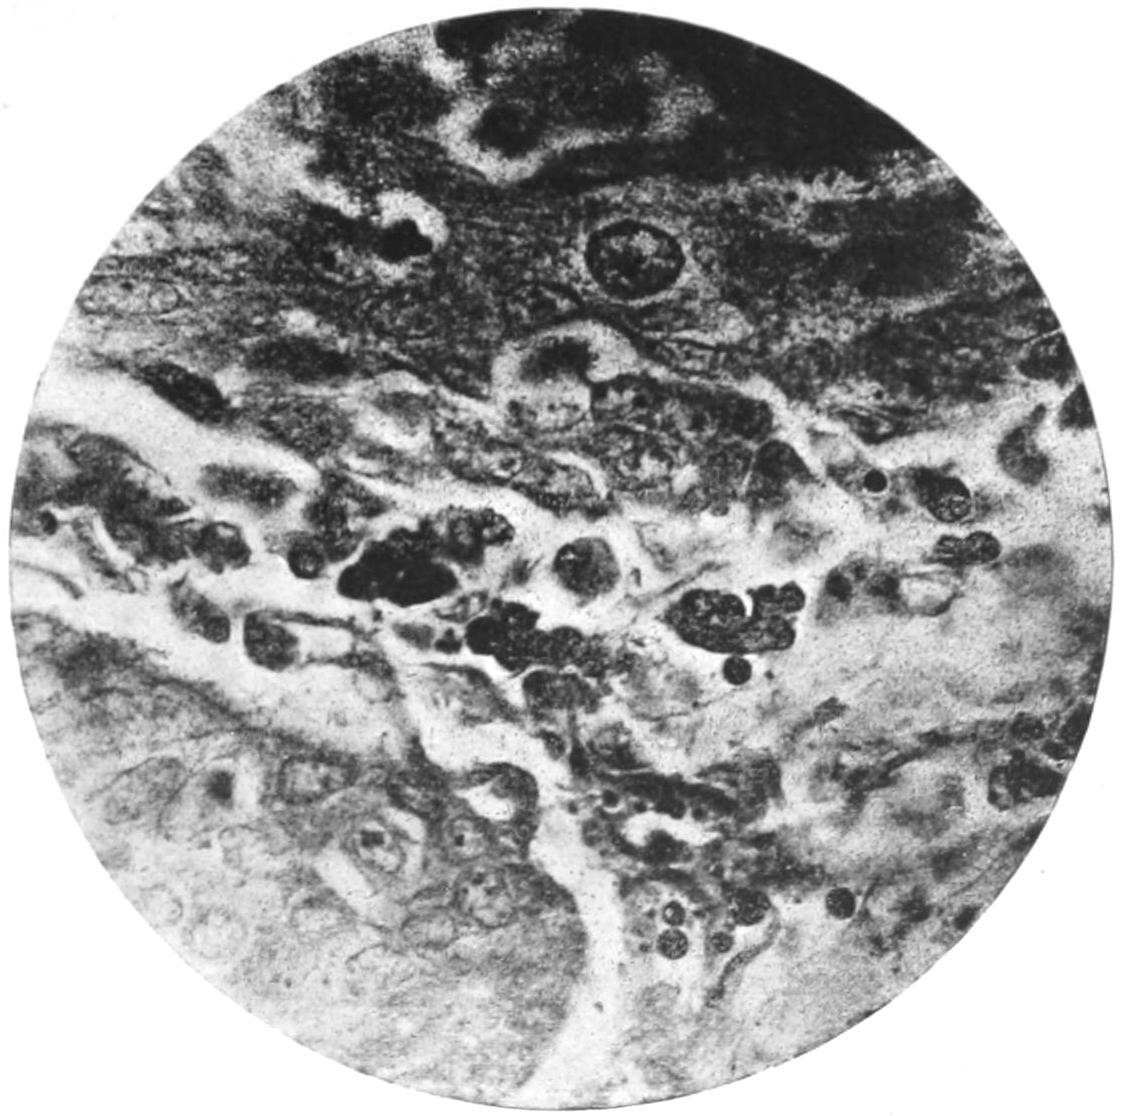
Fig. 1. Parasites, at one time called Russell’s Bodies, at Periphery of Epithelioma of Tonsil. (Oil immersion.)
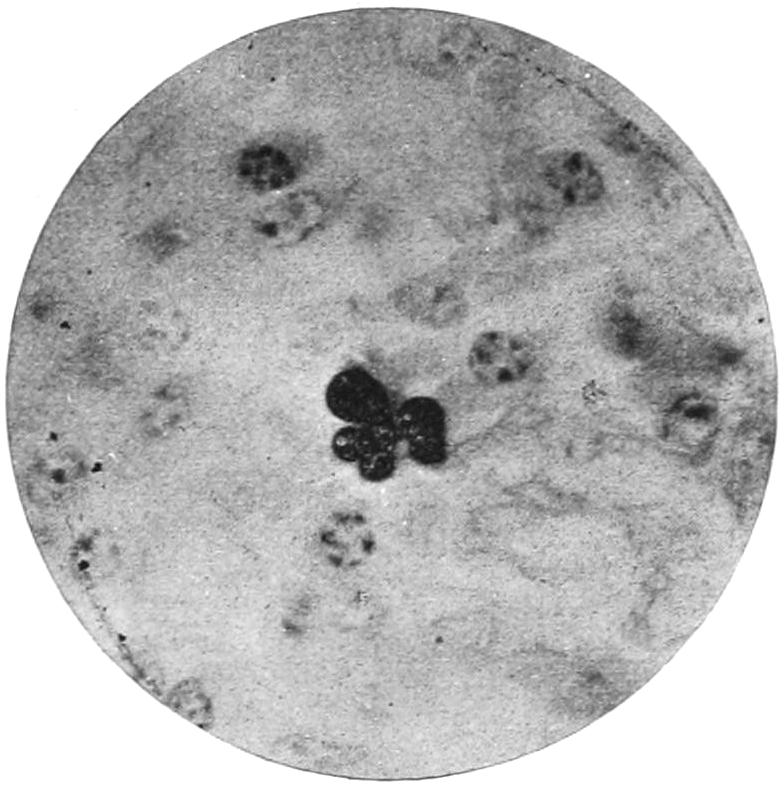
Fig. 2. Same in Lymph Node before Epithelial Invasion. (From N. Y. State Path. Lab. Rep.)
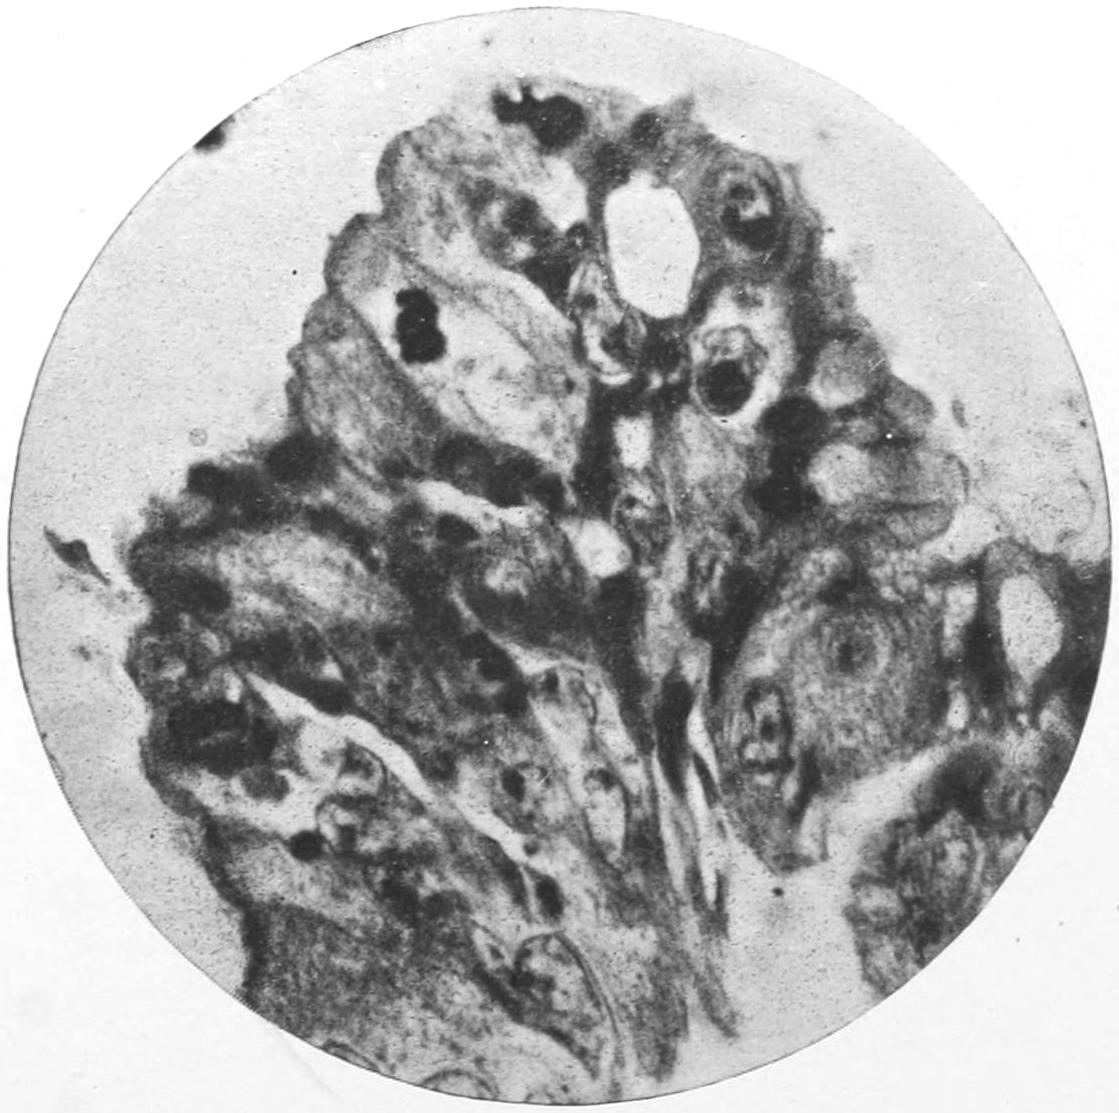
Fig. 3. Papillary Adenocarcinoma of Ovary, showing Intracellular Ameboid Forms of Parasites. (From N. Y. State Path. Lab. Rep.)
2. The Analogy Afforded by the Infectious Granulomas.
—These are universally conceded to be of parasitic origin, while their clinical course and behavior in every respect make many of them almost as malignant as the true cancers become.
3. Metastasis.
—This is in every other disease considered to be one of the most significant expressions of infection, yet until recently few of those who have willingly accorded to metastasis its now common interpretation in tuberculosis have been willing to give it the same dignity as a factor in the spread of cancer and an important explanation of its nature. Why should every other disease characterized by metastasis be everywhere viewed as parasitic, and cancer, in which occur some of its most positive expressions, be denied? Metastasis has the force and significance of an inoculation experiment performed under favorable circumstances.
4. Evidence of Local Infectivity.
—The involvement of a part which has lain in contact with a cancerous lesion, as about the mouth or the vulva, and in many other ways and places of which medical literature is now full, and the instances of cancer following the knife wound, especially following the track of the trocar used for tapping a case of cancerous ascites, stamp the disease as having an infectivity which cannot be explained on any inherent property of its own.
5. Microscopic Appearances.
—While it is true that but few observers have been able to agree upon a definite cancer parasite, it is also true that many of the best observers have seen, described, and figured bodies that do not belong in the cells of a cancerous growth except they are there in the roll of active agents, and the appearances which have been described by Pfeiffer, Plimmer, Gaylord, Calkins, and others are not to be explained away as mere artefacts, but must be given a place in our estimation which they would attain of themselves, as exciting suspicion, were there no other facts corroborating the views that they are in some way actively connected with the production of the disease. (See Plates XIV, XV, XVI.)
6. Inoculation Experiments.
—No feasible plan has been devised for practising inoculation experiments upon human beings. It is known, however, that the disease may be transmitted in some cases among animals of the same species, and the transfer has been made in a few instances from man to the lower animals. In the Gratwick Laboratory (Buffalo) the disease has been thus transmitted through hundreds of mice, and has thus afforded the best means of studying it in its varied phases, albeit in small animals, ever yet enjoyed. But cancer does occur in animals and has proved to be capable of inoculation, and, therefore, has responded to one of the severest tests of the value of the theory. Moreover the facts cited above (under 4) are essentially successful auto-inoculation.
7. Clinical Observations.
—Add to the features already mentioned above those impressions which come from accurate observation and correlation of the phenomena attending many cases of cancer, and a plausibility is thus lent to the parasitic theory which it can never gain from study in the dead-house or through the microscope. The resemblance between it and other known infections, the local and general alterations of tissues and fluids, the chemical changes by which the cachexia of the disease is brought about—these with other features all conspire to give the keen observer of cases of cancer an impression of parasitism or infectiousness which nothing can efface. Add to these its endemic, sometimes almost epidemic occurrence, its apparent transmission by contact, and the fact that it is but little influenced either by nutrition or drugs, and the argument is still strengthened. As against these arguments little has been advanced save denials or negations.
In thus upholding the parasitic theory, the writer would not wish to be understood as claiming either that the parasite has yet been discovered or its nature positively made out, nor that it is a question of one organism alone; rather, on the contrary, he feels that it is probably a question of several agents, probably of protozoan character, perhaps too small to be recognized with the lenses of today, perhaps belonging to some as yet unstudied class of organisms, making themselves known, however, as do the hypothetical parasites of syphilis and scarlatina, by their effects. To accept the parasitic view is to reconcile many discrepancies of earlier times and to give an entity to the disease by which, and until something better be found, we may be more safely guided in its management.
The parasitic theory lends plausibility to the statement which the writer wishes to emphasize, that cancer, like many of the other infectious diseases, is at first a local condition, that it is not transmitted by inheritance, and that there is a time in the history of every cancer when, if it could be recognized sufficiently early, and if it were also accessible and thoroughly removed, it could be cured.
Nomenclature.
—The nomenclature of tumors has been much confused, and if some new terms are introduced it is perhaps better than to cling to some which have prevailed in the past. Various systems have been followed of naming them according to their supposed nature or their evident tendency, or according to some purely arbitrary classification; thus there is the distinction into homologous and heterologous or heteroplastic, according as they are similar to or variant from that tissue in which they seem to originate; or they have been referred to as benign and malignant according to the disposition which they evince; and these terms are in sufficiently frequent use to demand acceptance. The distinction between benign and malignant is convenient and in some respects accurate, implying little in regard to histological structure, but much in regard to their effect upon the individual.
So far as method of classification goes, the anatomical (i. e., the histological) has proved far the most satisfactory, and is that which is now generally adopted. It is the basis for the classification followed in the ensuing pages. But even here it is impossible to maintain abrupt or always accurate distinctions, because tumors are frequently of mixed type, and it is required, if desired to express their composition by their names, to sometimes combine words in an awkward fashion.
By common consent that tissue which predominates furnishes the concluding portion of the compound term, while by prefixing other terms we endeavor to imply the composite character of the neoplasm.
Thus we have osteochondroma, fibromyoma, myofibroma, etc., and it is necessary often to reduplicate terms in order to be accurate in description. While this complicates phraseology, it nevertheless furnishes to the reader a reliable clue as to the general character of such a growth; and if one reads, for instance, of a myxochondrosarcoma, he promptly infers therefrom that thereby is meant a tumor essentially a sarcoma, in which both myxomatous degeneration and cartilaginous formation have taken place.
In the same way the prefix cysto is frequently used to imply a combination of originally solid tumor which had undergone cystic changes in whole or in part.
The old term cele is frequently used as a suffix, implying neoplastic changes in an organ, or at least the formation there of a tumor. Thus we have bronchocele, hydrocele, and cystocele. Again, certain terms are used in a different sense from that originally intended. Thus the term sarcoma has a definite significance, whereas originally it had little meaning and was applied inadequately and indiscriminately. Old terms also, like fungus hematodes, are now used rather in a descriptive sense, because for any such tumor we can find, on accurate examination, a proper term taken from descriptive pathology. Therefore the student of today should read the works of the older writers, especially concerning neoplasms, with a certain amount of intelligence, as well as of apology for the inaccuracy and misnomers of the past.
TREATMENT OF TUMORS.
The results of treatment of tumors leave much still to be desired, particularly when dealing with those of malignant nature. So far as purely internal treatment is concerned, we have not yet discovered drugs which with any certainty influence cell growth to the extent of making them reliable or effective. In the past, and even at present, numerous remedies have been advocated as having more or less power in this direction. Of them all it is probable that arsenic in some form is more efficacious than any other. This is true in the case of the disease elsewhere spoken of as malignant lymphoma, or Hodgkin’s disease, which partakes much of the character of some of the other neoplasms. But to say that arsenic alone or any other known remedy can be relied upon at all times is making a bold assertion.
Operable Tumors.
—The treatment of operable tumors is essentially surgical (i. e., operative), although to a large extent results are based upon the essential character of individual cases. But it can be stated that to be successful in the removal of any tumor its complete extirpation is imperative. Even the most benign growths will return if only partially removed. This is true even of innocent cysts, which will be often reformed if a portion of the cyst wall be allowed to remain. Complete extirpation is ordinarily a simple measure when tumors are encapsulated, as are often many of the innocent tumors. On the other hand, the performance of some of these operations is made difficult and hazardous by the location of the tumor, as in many large uterine fibroids, tumors of the thyroid, etc. But when dealing with malignant tumors the secret of success is to extirpate them, sacrificing everything which may appear to be involved unless, like a large bloodvessel or important organ, it be essential to the life of the part or of the individual. These statements are made when speaking of tumors in a general way. More specific directions will be given when dealing with particular forms or in the chapters on Special and Regional Surgery.
CLASSIFICATION OF TUMORS.
Following custom in large degree, yet being guided by undeniable facts concerning histological structure, tumors will be classified and considered as follows:
1. Cysts.
2. Dermoids.
3. Teratomas.
4. Tumors of connective-tissue type.
5. Tumors of nerve elements.
6. Tumors derived from epithelium.
1. Cysts.
A cyst may be defined as a tumor containing one or more cavities filled with fluid or semifluid contents. This specifies nothing with regard to the location nor the character of the cyst wall nor the nature of the fluid contents. Following Sutton, I divide cysts into four groups:
Retention cysts.
Tubulo cysts.
Hydroceles, or distention cysts.
Gland cysts.
Retention Cysts.
—These imply a previously existing cavity whose outlet is obstructed and whose contents consequently accumulate, often to such a degree that the original character of both containing wall and contained fluid is entirely altered. When this occurs in glands or gland ducts there is usually complete atrophy of gland tissue, providing sufficient time have elapsed. Such cysts are due either to permanent or temporary arrest of flow. In hydronephrosis, for example, there is obstruction of the renal outlet and dilatation of its pelvis, with partial or complete atrophy of the kidney structure, until a cyst of enormous size may be present. When a similar condition obtains in the uterus, as by obstruction of the cervix, perhaps due to injury done during labor, we have a condition known as hydrometra, seen occasionally in women, often in the lower animals, and particularly in those having a bicornate uterus, causing a condition often mistaken for an enormously dilated Fallopian tube. Similarly, when the common bile-duct is obstructed, which may be due to impacted gallstones, to inflammatory lesions or tumors, there may be such backing up of bile in the gall-bladder as to produce the condition known as hydrocholecyst.
Under any of these circumstances pyogenic bacteria may produce infection which will be more or less promptly followed by suppuration; and then, instead of hydronephrosis, ydrometra, hydrosalpinx, etc., we have pyonephrosis, pyometra, and pyosalpinx.
Tubulo Cysts.
—These are cystic dilatations of certain functionless ducts and obsolete canals which no longer serve a useful purpose. They comprise:
1. Cysts of the Vitello-intestinal Duct.
—Cysts originating from this functionless duct occupy the umbilical region, sometimes projecting externally, sometimes internally. They are usually lined with mucous membrane furnished with villi and columnar epithelium. Such a cyst may be confounded with an umbilical hernia. These cysts occasionally open at the umbilicus and discharge irritating material, sometimes fecal matter. Cystic dilatation of the portion of the duct originally connected with the ileum is also sometimes seen.
2. Allantoic Cysts.
—These are connected with the urachus, which should ordinarily be found as a fibrous cord, but which occasionally persists in a pervious condition, in whole or in part. At birth it is often traversed by a narrow canal lined with epithelium continuous with that of the bladder. The urachus lies outside the peritoneum, and may be dilated at any point between its two extremities. When the entire urachus is pervious urine is discharged from the navel.
3. Cysts Connected with Remains of the Wolffian Body.
—The Wolffian body, or the mesonephros, is intimately related with the development of the kidney, the ovary, and the testis. In the two latter locations glandular elements may be met, persisting in adult life.
In the male the tubules persist as excretory ducts from the testis, but in the female they persist, in a vestigial condition, as the parovarium and Gärtner’s ducts. The ovary proper consists of the oöphoron and the paroöphoron, the former being the egg-bearing portion, the latter receiving the tubules from the adjoining structure known as the parovarium. The paroöphoron gives rise to cysts which burrow deeply between the layers of the broad ligament, make their way alongside the uterus, and raise the peritoneum. It is a peculiarity of these cysts that their inner walls often become papillomatous, and may even develop such a crop of warty outgrowths that these make their way through the cyst wall and protrude into the abdominal cavity, where they sometimes become detached and are dropped as loose bodies into the peritoneal sac. The condition is also often accompanied by warty growths upon the peritoneal surfaces. These need give rise to no alarm, because they usually disappear spontaneously with removal of the tumor. Paroöphoritic cysts are to be distinguished from parovarian cysts, which develop from the parovarium, this latter consisting of a number of tubules situated between the layers of the mesosalpinx, composed of an outer series known as Kobelt’s, an inner set, about a dozen in number, known as the vertical tubules, with a straight tube, running at right angles to these through the broad ligament to the vagina, known as Gärtner’s duct, which is homologous with the vas deferens in the male. Cystic dilatation of Kobelt’s tubes is often seen, these cysts being very small and having no clinical importance. Cysts arising from the vertical tubules are usually transparent until they attain considerable size, when their walls thicken. Their contained fluid is not harmful, and after rupture of such cysts internally the fluid is absorbed. Such cysts may rupture and refill several times. As between the paroöphorous and parovarian cysts the latter are easily enucleated, carry the ovary upon one side, and have the Fallopian tube stretched over them without communication.
The internal sections of Gärtner’s duct are more often involved in animals than in women, but excellent illustrations of cystic dilatation of its various portions have been observed, usually in the walls of the vagina.
Corresponding to the above-mentioned conditions in the female there are in the male, as the result of changes in the Wolffian body, two conditions—encysted hydrocele of the testicle, and general cystic degeneration of the same. Like the ovary, the testicle is a complex organ with remnants of the mesonephros persisting among its ducts, while only a few of the Wolffian tubules remain. True encysted hydroceles arise sometimes in the efferent tubes of the testis and sometimes in Kobelt’s tubes (the same structures which in the female give rise to parovarian cysts), the two conditions, therefore, being analogous and homologous. These cysts, though closely associated with the testis, lie outside its tunica vaginalis. Their contained fluid is usually clear or of a milky whiteness, due to fat globules. Sometimes it contains spermatozoa. Another variety is cystic dilatation of one or more of Kobelt’s tubules, which is often described as involving the hydatid of Morgagni.
General cystic disease of the testis, known also as adenomatous degeneration, was formerly referred to as hydatid disease of the same organ. The multiple cysts appear to originate in the remnant of the mesonephros still persisting, known as the paradidymis. The cavities are lined with epithelium, and papillomatous intracystic formation is not uncommon. These tumors have been called by a number of improper names, such as “cystic sarcoma,” etc.
Hydroceles.
—The term hydrocele has covered numerous conditions. At present, when no other locality is designated, hydrocele of the tunica vaginalis is understood. (The term implies a collection of watery fluid in a previously existing serous cavity.) This is the most common form.
Possibility of its formation depends upon the prolongation of the peritoneal cavity which takes place in advance of or along with the descending testicle, and which in many of the lower animals remains connected with the general cavity throughout life. In men only is it expected to close, even before birth. When the portion which extends along the spermatic cord is not completely obliterated there is encysted hydrocele of the cord, or funicular hydrocele, which is not common. The common form of hydrocele is constituted by serous effusion into the tunica vaginalis, and occurs usually without recognizable exciting cause. It will be treated more fully in its appropriate place.
The corresponding process of peritoneum in the female is known as the canal of Nuck; and, when persistent, this also becomes distended with fluid and forms a cyst known as hydrocele of the canal of Nuck, occupying the inguinal canal.
In many of the lower animals the ovaries are contained within a serous sac derived from the peritoneum, which is so connected with the opening of the Fallopian tubes that when the ova escape from the ovary they enter these tubes and pass to the uterus without entering the general peritoneal cavity. This ovarian sac is subject to serous distention, and constitutes a condition called by Sutton an ovarian hydrocele. An homologous condition occurs sometimes in the human female, by pathological adhesion, and such cysts may attain large size. They project from, and are intimately connected with, the posterior layer of the broad ligament.
Hydroceles of the Neck.
—Hydroceles of the neck, so called, are cystic collections of congenital origin found in the cervical region, due to dilatation of ducts or clefts which should have disappeared at or before birth. The forms of cyst to which the name “hydrocele of the neck” are usually limited are recognizable at or soon after birth, and constitute fluctuating tumors, often extending beneath the clavicle into the axilla or down upon the thorax. They may occupy the entire lateral region of the neck, and may be unilateral or bilateral—may be single or multilocular, and may even intercommunicate.
They originate always beneath the deep fascia. Some of these cysts are undoubtedly due to dilatation of lymph spaces. This is particularly true of the multilocular forms. There is noted in many of them a tendency toward spontaneous recovery, but many again require operative measures for their eradication. Occasionally their walls are extremely vascular, even to the degree meriting the term nevoid.
Some of these cysts are considered by Sutton to be essentially examples of the laryngeal saccules which are met with as diverticula from the laryngeal mucous membrane, which undermine the deep cervical fasciæ of certain monkeys. These air chambers, which are normal in the monkey, communicate with the larynx through the thyrohyoid membrane, and occasionally run down beneath the upper border of the thorax. Many of the cysts having this resemblance are closely related to the hyoid bone and to the larynx, and there is much to substantiate the view thus quoted.
Glandular Cysts.
—Ranula is an altogether too comprehensive term which has long been used in surgery, alluding to cysts in the floor of the mouth, and not indicating minutely their character nor their exact location. At present this term should either be restricted in signification or be eliminated. If used, it should be confined to retention cysts due to obstruction of the submaxillary or sublingual ducts. Such obstruction is often caused by salivary calculi impacted in the duct orifices. In other instances it is due to cohesion of the margins of the outlet. A similar condition in the parotid duct is known, but is less common. Aside from this, certain other cysts originate from minute beginnings in and about the floor of the mouth, being due to dilatation of the mucous glands, particularly one near the tip of the tongue, sometimes known as Nuhn’s gland. Dermoid cysts in this locality are not uncommon. Formerly cysts of the floor of the mouth were described as ranula.
Pancreatic cysts correspond in large degree to salivary cysts, the pancreatic duct becoming dilated by retention when its orifice is obscured; and, indeed, the condition has been referred to as pancreatic ranula. Sometimes the canal is dilated in distinct portions, so that the condition resembles a string of cysts; at other times it is the terminal portion which is most enlarged. Such cysts attain large size and contain mainly mucoid material. Examples have been reported showing that they have attained a capacity of two gallons.
In the mesentery there sometimes develop cysts which are known as chyle cysts, whose sacs appear to be formed of separate mesenteric layers, their cavity being occupied by fluid identical with chyle. Such tumors also sometimes attain great size.
In the eyelids one occasionally meets with cystic dilatations of the lacrymal ducts. These are known as dacryopic cysts or dacryops. Fistulas result when they are opened through the skin, and if meddled with at all they should be radically extirpated.[13]
Pseudocysts.
—In his elaborate work on tumors Sutton has made a distinct classification of pseudocysts, which lack some of the characteristics of genuine cysts, yet, nevertheless, are entitled to consideration in this place. Among these are included intestinal diverticula and vesical diverticula, in either of which instances hernial protrusions of the mucous membrane through the outer coating of the bowel or of the bladder occur, thus forming pouches. These are common in the bowel, rare in the bladder; especially in the former locality they are often multiple. This condition is often referred to as sacculation, and sacculation of the bladder may even be confounded with true urachus cyst. They are of little consequence so long as foreign materials, such as feces, urinary calculi, etc., do not lodge in them. But they occasionally cause serious trouble. Diverticula have been mistaken for appendices, while diverticula from the bladder have been encountered in hernia operations.
Pharyngeal diverticula give rise to rare but most interesting tumors. It is well known that the branchial clefts, which in early fetal life connect with the pharynx, are sometimes not completely closed, and that a portion of one may persist abnormally, giving rise to a condition known as the pouch of Rathke. There may also occur sacculation of the pharyngeal wall where it joins the esophagus, or hernial protrusions, especially in Rosenmüller’s fossa.
Cystic dilatation of Rathke’s pouch occurs near the upper part of the pharynx, and may attain the size of a marble. Hernial pouches are seldom mistaken for cysts, and are of importance mainly because of the fact that food or other foreign material gathers and lodges in them. Most of the other cystic abnormalities of the pharynx pertain to dermoids, and will be considered shortly. In a general way, these pharyngeal tumors have been grouped as pharyngoceles.
Similarly in the esophagus and trachea hernial protrusions occur, and lesions closely resembling retention cysts may be seen.
Synovial cysts (i. e., those containing synovial fluid) may arise (1) by protrusion of synovial sheaths, (2) by distention of bursæ in the vicinity of joints, or (3) by hernial protrusions of joint membranes. They are often met with in connection with the larger joints, more particularly about the knee. In this way tumors as large as goose-eggs may be formed, while their location may be so shifted that they present themselves in perplexing ways. To that form produced by hernial protrusion of the lining of a tendon sheath has been given the name ganglion.
The simple ganglion is frequently seen on the back of the wrist, and, while it is always connected with the tendon sheath, it undoubtedly often connects with the synovial membrane of the carpal joints. The compound ganglion, so called, is a much more serious and extensive affair, being one which has prolongations in two or more directions, and containing peculiar bodies, known as melon-seed bodies, which appear to be fibrinous concretions worn round and smooth by attrition. These are present sometimes in enormous numbers. (See Tuberculosis of Synovial Structures, Chapter IX.)
Bursæ are normal in many well-known situations in the body, but may undergo cystic dilatation and become annoying tumors. In many other places, under the influence of friction or mechanical irritation, there develop bursæ which are known as adventitious. These are sometimes subtendinous, and may communicate alike with joint sheaths and tendon sheaths. These are true cysts of new formation not developed from a pre-existing cavity.
They are largely the effect of peculiar occupation, as in housemaids and carpet-layers there are formed frequently prepatellar bursæ, while miners get them upon the elbow, porters upon the shoulder, plasterers upon the forearm, etc. In the same way, by the pressure of ill-fitting boots, an adventitious bursa is developed over the expanded head of the first metacarpal bone, thus forming a condition known as bunion.
Neural Cysts.
—This term has been applied by Sutton to pseudocystic dilatation of certain cavities found in the brain and central nervous system. Hydrocephalus is in one sense a pseudocyst of this variety. Corresponding to it in fetal life is hydramnios. Hydrocele or cystic dilatation of the fourth ventricle is well known. Cranial meningoceles, which are hernial protrusions of brain membranes, are also pseudocysts, to be included in this category. They will be considered in Chapter XXXVI. Cephalhematoma may be also included in the same way. Spina bifida, a condition which will be described in Chapter XXXVIII, is, nevertheless, practically a cyst of congenital origin involving the spinal meninges. One form of spina bifida is constituted by cystic dilatation of the central canal of the spinal cord, and produces syringomyelocele. These conditions will be treated more fully in their appropriate places.
Sutton has rendered a great service by showing that the brain and spinal cord are evolved from a segment of the primary intestines, and that the intestinal canal and the neural canal communicate in fetal life at their lower terminations; while it has been shown by several that in the earlier forms of mammalian life they were also connected by their anterior terminations. It is in this way that certain complex tumors of the sacral and coccygeal region are to be explained. So also is the collection of lymphoid tissue in the vault of the pharynx, known as Luschka’s tonsil, and in the coccygeal region, known as Luschka’s gland, it being a curious and instructive fact that lymphoid tissue of this character is always met with in the neighborhood of obsolete canals.
Hydatid Cysts.
—These cysts are the indirect product of the eggs of the Tænia echinococcus, a form of tape-worm which infests the alimentary canal of dogs. The eggs reach in some direct or indirect way the food or water taken into the human stomach and are there hatched; the young animals migrate through vessel walls and are deposited in some tissue or organ where the cyst later develops. These cysts have a thick, elastic wall, with a lining containing cells, involuntary muscle fibers, and a water-vascular system. After such a cyst has attained the size of an inch or more, small vesicles, or “brood capsules,” begin to develop, which present at one point a retractable head, with scolices so arranged in crown form as to produce sucking disks. According to the date at which the cyst is opened appearances will differ. Sometimes a large cavity will be filled with multiple “daughter cysts,” and sometimes these will have disappeared, so that the cyst fluid contains nothing distinctive. After having ceased to develop, hydatids frequently undergo atrophy and even become calcified; the characteristic hooklets are the last of the distinctive features to disappear.
These growths may be rapid, even to the point of producing necrosis and rupture, or may be very slow and persist almost unchanged for years. The disease is uncommon among the native-born population of the United States, and most of its examples are seen in emigrants. It is exceedingly prevalent in Iceland and in New Zealand. It occurs most often in the liver, but is frequently met with in these countries in the lungs, the brain and spinal canal, and the bones, but may be encountered in any part of the body. When located near the intestinal tract or the air tract the cysts are more liable to penetration by ordinary germs of sepsis, and then may suppurate. It is not infrequent to have conversion of an hydatid cyst into an abscess. Before or after such change it may undergo rupture, spontaneous or traumatic, and this, according to the nature and amount of its contents, and the location of the opening, will promptly produce more or less grave symptoms. While spontaneous recovery has, in rare instances, followed rupture, it has perhaps more often led to fatal result. At all events, it will produce serious and perhaps distressing symptoms.
The only radical treatment for hydatid cysts is extirpation. When this is not possible the cyst may be opened and the margins of the opening attached to those of the skin wound. After being evacuated it should be packed and drained, and then may be expected to slowly contract, perhaps even to the point of obliteration. The contents of such a cyst should not be allowed to escape into any of the body cavities, since their sterility can not be always relied upon.
Cystic Degeneration.
—Hematocele is an expression meaning a tumor composed originally of effused blood which has undergone chemical and other changes, which consist of lamination and thickening of its exterior portion and fluidification of the interior, until in course of time such an internal blood clot may be converted into a distinct and plainly walled cyst. This condition may be seen in two locations—namely, in the pelvis and between the cranium and the brain, or in the brain. The hemoglobin gradually disappears, and the contents of these cysts are translucent or even watery in appearance. Hematoceles may form where there has been internal hemorrhage in certain locations which has failed to absorb, and where no pyogenic infection has occurred.
Pseudocystic changes occur in other tumors and in other parts of the body as the result of mucoid and colloid liquefactions. In the midst even of apparently dense and entirely defined tumor masses changes of this kind occur, and lead to formation of cavities containing fluid of variable consistence, causing the tumor when divided to present the appearance of the geodes or quartz rocks, containing cavities lined with quartz crystals. The occurrence of such cystic changes is indicated, in naming such a tumor, by prefixing the term cysto-, as cystosarcoma, cystofibroma, etc.
2. Dermoids.
Dermoids are cysts or tumors containing tissues and appendages which are developed from the epiblast, and which occur when skin and mucous membrane are not normally found. The simplest form of dermoid is a cyst whose interior is lined with modified skin, containing sebaceous glands and hair follicles, from which often numerous long hairs are produced. Even sweat glands may be present. Its cavity is occupied by mixed material, pultaceous in character, made up of sebum, cholesterine, and growing hairs which are often rolled into balls. The sebum is the product of the glands contained in the cyst wall.
A complex form of so-called dermoid cyst is met with in which there are unstriped muscle fiber, teeth, mammary glands, etc. These belong rather to the class of teratomas, as they contain more or less tissue not of epiblastic origin.
A dermoid tumor is one lacking cystic characteristics, made up of tissue largely developed from the epiblast, with more or less tissue of mesoblastic origin. Such a tumor may contain much connective tissue, fat, fetal hyaline cartilage, and nerve tissue, while from its exterior long hair may grow, and teeth project from its surface or be embedded within its substance. Such tumors are generally found in the pharynx and about the rectum.
The explanation of dermoids and teratomas may be gleaned from embryology, and rests upon the arrangement of the different blastodermic layers of the developing ovum, and upon the facts already alluded to in explaining Cohnheim’s hypothesis of the origin of tumors. Strictly speaking, a dermoid should contain only that which may be developed from the epiblastic layer. It is well known that teeth and hair, as well as sebaceous material, are epiblastic products. Consequently such material may be found within a dermoid and needs no further explanation than an epiblastic inclusion, according to Cohnheim’s views. But so soon as such a tumor contains bone, muscle, etc. (i. e., tissues of mesoblastic origin), we should drop the term dermoid and consider it a teratoma. Such is the distinction between these two terms. According to Wilm’s researches, any tumor of this sort which contains epithelial products as teeth or hair is sure to contain also mesoblastic elements, and thus to belong to the latter. The term epidermoids has been applied to the former.
The most prominent characteristics of dermoid cysts are: (1) Skin, which may be thick or thin, lined with papillæ, containing more or less pigment, its deeper layers possessing a quantity of fat. (2) Hair, which next to skin is the most constant structure found in dermoids; this may be present in trifling amount or in long coils or balls. It is of interest that in dermoids found in animals covered with wool we find the same character of hairy structure, while in birds dermoids contain feathers rather than hairs. (3) Sebaceous glands and their peculiar secretion are invariably found. These may be of large size, and sebaceous retention cysts may be seen in the walls of dermoids. Sometimes horny matter or tissue is found in these, indicating the same relation between horn and sebaceous structures, as we see upon the external skin in other instances. So, too, material resembling the texture of finger-nails is occasionally found projecting into the cavity.
The fluid or semifluid contents of these cysts consist usually of sebaceous material, cholesterin, epithelial debris, etc. Sometimes it is thick, sometimes thin—and occasionally consists almost entirely of mucus.
It is not uncommon to find structures in ovarian dermoids closely analogous to, or actually resembling, mammary glands. These may be mere nipple-like processes of skin, or completely developed mammæ, well formed, but without ducts or gland tissue, may occupy such a cyst. These really are pseudomammæ, because they have no ducts. Nevertheless, glandular tissue is not always absent. This resemblance proceeds even farther, in that in some of these ovarian mammæ changes occur analogous to those which take place in normal breasts.
The epiblast seems to have the power of developing mammary glands or supernumerary mammæ in many locations—in fact, upon any part of the body surface. About the thorax they are common; upon the abdomen they are rarely observed; and they have been found even upon the labia.
Sweat glands are infrequent in dermoids. Teeth are quite common. These may vary in number from two or three up to several hundred—may be embedded in definite sockets or simply sprout from the cyst wall. Occasionally bone material, lodging such teeth and crudely resembling a jaw, will be found.
Dermoids containing mucous membrane are found, especially in connection with the ovary and with the postanal gut (i. e., the original communication between the spinal and alimentary canals).
It is curious that under these circumstances mucous membrane is sometimes furnished with hair, as it normally is in the stomach or other cavities of some of the lower animals. Mucous glands and retention cysts of these glands are also found in ovarian dermoids. This will be more readily understood if the mutability of skin and mucous membrane be not forgotten. The transition from one to the other is not difficult, and we find all intermediate stages between the two extremes—if not in man, at least in animals. This will account for the fact that skin-covered dermoid tumors are found in certain parts of the alimentary canal, and particularly in the pharynx. These tumors grow also from the mucous membrane of the bowel, of the rectum, or even of the small intestine.
Sutton has made a division of dermoids into three classes:
1. Sequestration;
2. Tubulodermoids;
3. Ovarian.
1. Sequestration Dermoids.
—Sequestration dermoids occur chiefly in situations where during embryonic life coalescence takes place between two surfaces possessing an epiblastic covering, although sometimes this coalescence practically occurs late in life and by implantation.
Dermoids of the trunk occur particularly where opposite halves of the body wall coalesce—that is, in the midline of the trunk and head. Dermoid cysts are rarely found in connection with spina bifida, and certain tumors spoken of as spina bifida undoubtedly are dermoids. Anteriorly dermoids occur frequently in the scrotum, and occasionally in the testicle. At the umbilicus they are rarely found—usually as pedunculated tumors projecting externally. In the midline of the thorax and neck they are most common opposite the manubrium, dropping down behind it to invade the anterior mediastinum. Near the hyoid bone they occur relatively frequently; about the head they are met with most commonly at the angles of the orbits—more so at the outer than at the inner angle. Dermoid cysts are known to oculists as growing upon the iris or springing from the conjunctiva. About the ear they are not infrequent; in the roof of the mouth, especially if this be incomplete, we frequently find cysts of epiblastic origin.
Sequestration dermoid cysts are also undoubtedly found in connection with the dura mater, in the scalp, most commonly at the anterior fontanelle, at the root of the nose, and at the external occipital protuberance, where they may be confounded with sebaceous cysts or with meningoceles. In order that a dermoid of the dura may communicate with the skin there must of course be osseous defect.
Sequestration dermoids upon the limbs have been mostly reported as sebaceous cysts. They are rare, and usually associated with antecedent injury, by which epiblastic structures are driven in and implanted in such a way that as they develop they give rise to these peculiar tumors. These are what Sutton calls implantation dermoids. They are found upon the fingers and elsewhere.
2. Tubulodermoids.
—These are largely connected with obsolete canals and ducts. It is a great service which Sutton has rendered in proving, apparently beyond the possibility of doubt, that the central canal of the nervous system is really of intestinal origin, and may be regarded as a disused segment of the primary alimentary canal. He has also shown how it behaves occasionally as do other functionless ducts, and that cysts and dermoids in connection with it are to be thus explained. He and others have also shown the anterior as well as the posterior communication of these canals, and the pituitary body are to be regarded in this light as the same formation of lymphoid tissue around an obsolete canal which we see in Luschka’s tonsil close by, and in Luschka’s gland at the other extreme of the canal.
Fig. 72
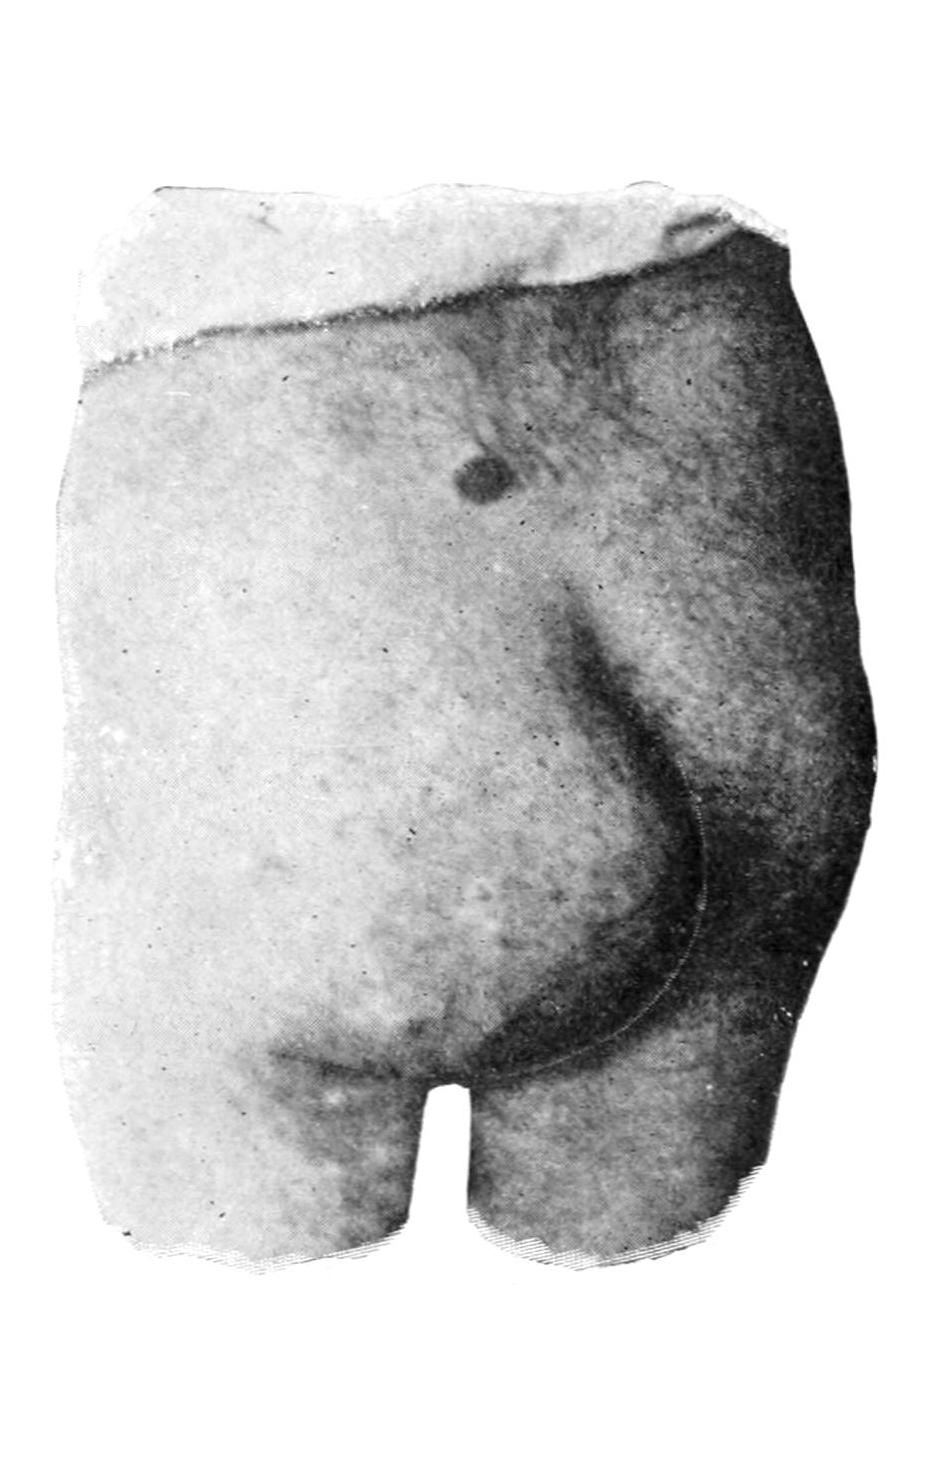
Solid dermoid escaping from pelvis. (Original.)
Fig. 73
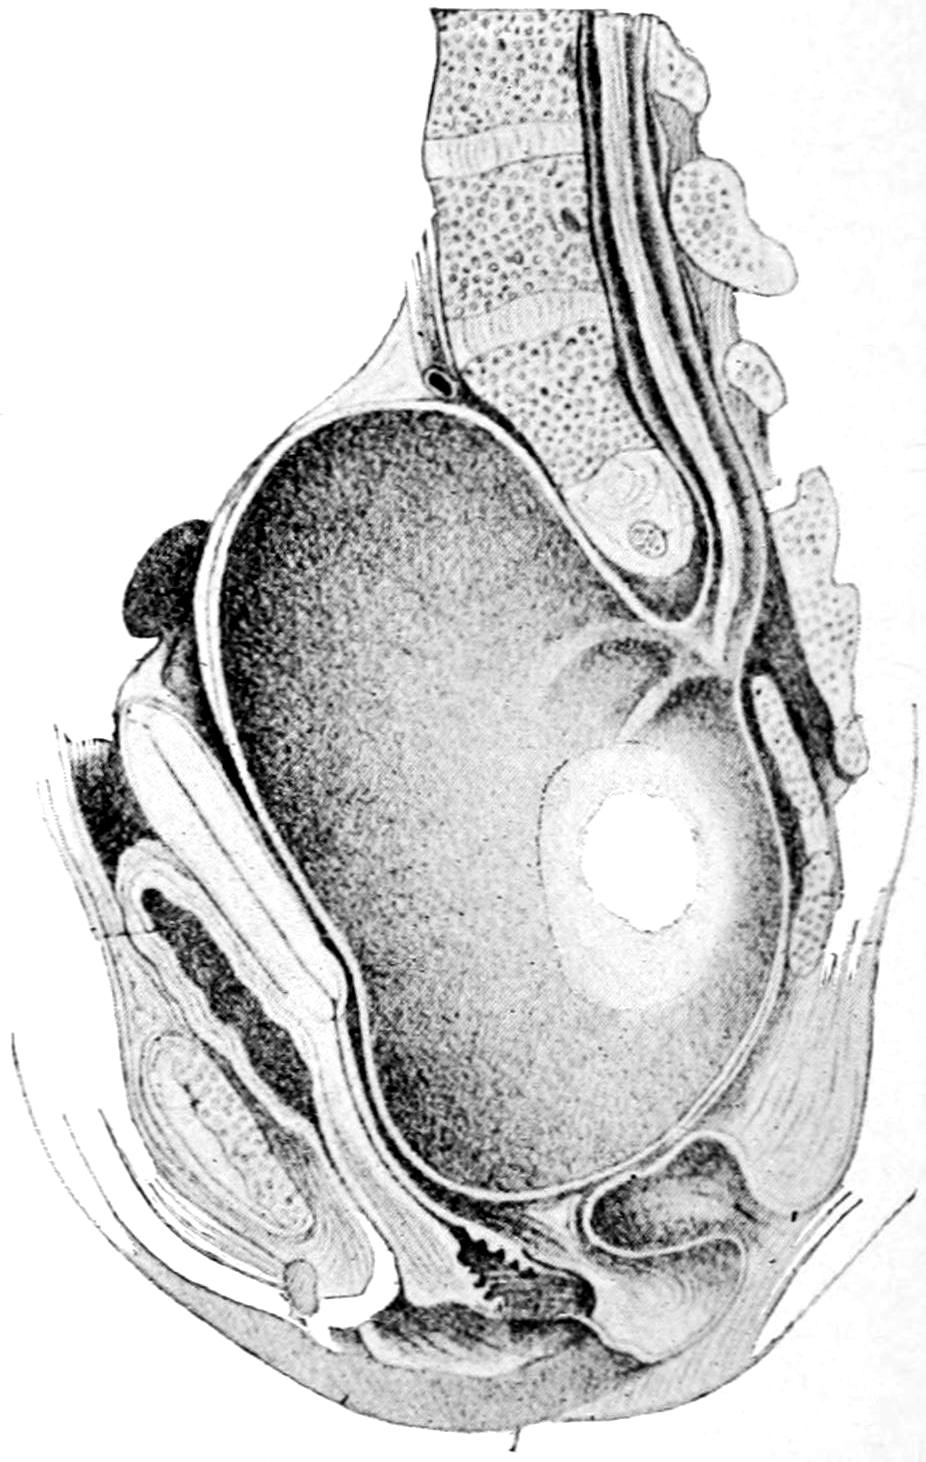
Congenital dermoid cyst of pelvis. (Ahlfeld.)
The primary alimentary canal was a continuous tube lined with a continuous layer of columnar epithelium. That portion connected with the yolk sac develops into the intestine, the balance into the central nervous canal. Portions of this canal are in postnatal life absolutely obsolete; others persist in a rudimentary condition. Dermoid cysts and dermoid tumors develop in connection with each of these. In some there is a large central cavity; others are almost absolutely solid. Thus we find dermoids in the coccygeal region, which have been variously regarded as sarcomas, adenomas, etc., which are really of origin as stated above and should be considered simply as dermoid tumors. Most of these project outwardly; some of them arise and develop within the pelvis. Dermoid cysts and tumors are also met with in connection with the rectum—sometimes between the rectum and the bladder, and between the rectum and the spine. Dermoid tumors are also found in connection with the pituitary body. These sometimes develop within the cranium, or, again, protrude perhaps into the orbit, perhaps into the pharynx.
Thyroid dermoids are tumors of great interest. They develop sometimes about the craniopharyngeal canal, which may be detected as a small canal in the macerated sphenoid bone of a fetus, and which before birth is filled with fibrous tissue. It connects with a recess in the middle line and at the base of the skull, presenting in the pharynx, which is often referred to as the bursa pharyngea. It is around this recess that the lymphoid tissue known as the “pharyngeal tonsil” develops. It may be thus expected that the roof of the pharynx should be the occasional site of dermoids. It is from the pharynx or the floor of the mouth that in vertebrates the thyroid body arises. In higher forms it becomes dissociated from the pharynx and shifts its position. The thyroid body is developed around the thyroid duct, which first appears as the thyrohyoid duct, which later becomes divided, that portion in relation with the tongue becoming the thyrolingual duct, the remaining portion persisting as the thyroid duct. These are present about once in every ten subjects, according to Sutton, the canal when persistent being lined with epithelium. When the extremities of these ducts become occluded retention cysts may form. In the same way dermoids of the tongue are formed, similar to those occurring on the scalp. These are frequently mistaken for sebaceous cysts. They may be unilateral, central, or even bilateral. The lingual duct is also of interest, because it would appear that certain cases of epithelioma of the tongue arise along this duct, and perforating malignant ulcer of the tongue is thus produced. Dermoid tumors of the lingual or thyroid ducts resemble in structure the thyroid body. The thyroid duct may also be detected in many adults running from the isthmus of the thyroid body to the posterior aspect of the hyoid bone, and surrounded by muscle tissue. Sometimes the space usually occupied by this duct is represented by a series of detached bodies known as accessory thyroids. These are not infrequently the seat of cysts, sometimes of considerable size. (The accessory thyroids often enlarge when the main thyroid has been extirpated for disease.) Thus cysts in close relation to the hyoid bone are common. Some of them grow slowly, while others grow rapidly and contain much fluid. Many of them are unilateral, and are often mistaken for enlargements of one lobe of the thyroid. Cysts growing from accessory thyroids are often filled with papillomatous masses, and are occasionally the seat of malignant degeneration.
In the omphalomesenteric duct or its remains, especially in relation with the umbilicus, we often meet with small cysts or tumors in infants and young children. When the duct is persistent it presents normal intestinal structure, and, like the appendix, possesses much adenoid or lymphoid tissue.
Another and very important form of tubulodermoids develops in connection with the branchial clefts of the neck. Congenital fistulas of the neck have been long known, but only comparatively recently understood. Of the branchial clefts it is well known that the first alone should persist, as the Eustachian tube. Occasionally, however, they fail to become obliterated, and then we have congenital tumors or cysts, which may, perhaps, not develop to appreciable size until somewhat late in life; or there may be fistulous passages opening either into the pharynx or externally, forming canals varying in length from half an inch to two inches, secreting a little fluid because lined with epithelium. When these become inflamed an abscess results. When they open externally the opening is often marked by a little tag of skin containing a fragment of yellow cartilage. These are often referred to as cervical auricles. They open along the line of the sternomastoid muscle. The internal openings of these fistulas frequently form diverticula from the pharynx or esophagus. Thus it will be seen that dermoid cysts about the neck are principally relics of openings or ducts, which are normal in embryonic life, but which should have been obliterated at or long before birth. Congenital fistulas, however, may be met with in the middle line of the neck, which are not to be confounded with branchial fistulas, but rather with the ducts previously described.
3. Ovarian Dermoids and Teratomas.
—These may be unilocular or multilocular cysts, usually the latter. They are lined with epithelium, and contain mostly mucoid fluid, the inner coat being practically identical with mucous membrane. Occasionally, however, the skin is furnished with hair, sebaceous glands, teeth, and even nipples. The multilocular cysts are practically an aggregation of those just described. They are surrounded by dense capsules, often attain great dimensions, and are made up of primary cysts resembling large cavities in a honeycomb-like mass, which itself is occupied by secondary cysts, and belong rather to the class of mucous retention cysts, these being occupied by still smaller ones, which are histologically indistinguishable from distended ovarian follicles. In these large tumors we find in some cases hair, in others teeth, and in others sebaceous glands, etc., the dermoid constituents being scattered throughout. As Wilms has shown, in almost every tumor of this character a projection may be found whose summit is covered with epiblastic elements, which when cut in serial transverse sections will show in its deeper portion other epithelial collections representing a feeble attempt to develop a nervous system, or lung tissue, while mesoblastic elements, like connective tissue, cartilage, and bone, appear scattered throughout, as though a very crude effort had been made to reproduce an atypical embryo.
3. Teratomas.
So far the endeavor has been to limit the term dermoid to tumors which are essentially of epiblastic formation, their location being explained on the inclusion theory of Cohnheim. There is also a still more complicated type of tumor, composed of tissues of both epiblastic and mesoblastic origin, perhaps even hypoblastic. Their consideration belongs to that department of pathology known as teratology, which is supposed to deal especially with monsters. Strictly speaking a teratoma refers to an irregular tumor or mass containing tissues and fragments of viscera of a suppressed fetus which is attached to an otherwise normal individual. Nevertheless the term is often applied to growths which are the result of luxuriant mesoblastic development in which neither form nor member of a suppressed fetus is present.
The presence of supernumerary members is largely connected with what is called dichotomy, alluding thereby to cleavage either at the anterior or posterior end of the developing embryo. When the whole embryonic axis divides twins may be produced, but should cleavage be partial we may have a monster with two heads if it be anterior, or one with three or more limbs if it be posterior. Children born with these deformities are usually called monsters, and the study of such cases belongs entirely to teratology. But in certain tumors small portions of a suppressed fetus may develop, as, for instance, from the posterior portion of the sacrum, or within the abdomen or thorax, or upon the neck or face, which on dissection may contain a few vertebrae or processes resembling fingers associated perhaps with a structure resembling intestine or liver. This should be called a teratoma. Such tumors possess for the pathologist the greatest value. In surgery, however, they are rare, and there are scarcely two cases alike. The question of operation will often arise, as it does with supernumerary limbs, and each case should be studied upon its own merits. Sometimes they are amenable to extirpation.
Embryonal Adenosarcoma.
—Embryonal adenosarcoma is a term given to certain teratomatous tumors peculiar to renal and adrenal structure, which present peculiar characteristics in the mixture of elements which enter into their composition. At various times these tumors have been called adenoma, sarcoma, rhabdomyoma, congenital cystic kidney, etc. They have been also likened to the thyroid. They comprise a group of neoplasms, always congenital in origin, which usually appear early in life, but occasionally occur in advanced adult life. One of the most marked specimens of this kind the writer removed from a man over fifty years of age. Most of the specimens, however, described in literature pertain to the young. On minute examination they often present a strange, mixed picture of voluntary muscle elements intermingled with epithelium arranged to imitate acinous glands, with cystic dilatations of the true kidney tissue. They often attain enormous size, and undergo such proliferation of mesoblastic elements as to resemble sarcoma. Their occurrence is to be explained only on the principles of Cohnheim’s hypothesis. When the original Wolffian body is being differentiated from the elements about it a confusion of the same with the excretory tubular beginnings, which are to empty into the Wolffian duct, occurs. Thus we have the commencement of a mixed mass which presents itself as a more or less rapidly growing tumor, in which even cartilage or other mesoblastic structures may be met with. It is scarcely possible that any two specimens should yield exactly the same microscopic picture, much depending on whether one element or the other prevail. In a few of them there may occur also a mixture of adrenal elements. Sometimes the renal structure itself is more or less distinct, and rides, as it were, upon the surface of the tumor; at other times it is entirely mixed up with it. While the condition is usually limited to one side it may be a double affection, so that the second kidney becomes useless and the patient succumbs. The only treatment is extirpation.
Teratomatous tumors are sometimes found hanging in the pharynx, attached by a small pedicle, where they may be confounded with dermoids unless carefully examined after removal. Many instances of this type of tumor are found in animals. Here no false sentiment will prevent complete examination and preservation of the specimen. They are also encountered in the sacral and coccygeal regions.
4. Tumors of Connective-tissue Type.
Lipoma.
—Lipomas, or tumors composed of fat, are the most common of the neoplasms. Their normal type is the ordinary adipose tissue of the body, and may be divided into the encapsulated and the diffuse, the former of which are surrounded by fibrous tissue. The diffuse lipomas are those which have no capsule, and where the pathological collection of fat merges into that normally present—in other words, they are not circumscribed.
Subcutaneous Lipomas.
—Subcutaneous lipomas are perhaps the most common of all, and are usually irregularly lobulated and encapsulated, adherent rather to the skin than to the deeper tissues. Usually but one is found in an individual, though instances of multiple lipomas are not rare. They develop sometimes to enormous size, cases being on record where the tumor has even weighed one hundred pounds. They may be met with at any point on the surface of the body. The lobules often burrow between the muscles, and those found in the palm of the hand penetrate even beneath the palmar fasciæ. They are sometimes markedly pedunculated, and often hang by a small stem. The diffuse subcutaneous lipoma is most common about the neck, in the groin, and in the axilla.
Subserous Lipomas.
—Subserous lipomas are mostly retroperitoneal, and large tumors of this character, mistaken for ovarian, have been successfully removed by operation. They also occur in the hernial canals and spaces. They develop beneath the peritoneum covering the intestines, and in this location give rise occasionally to intussusception. Here in their pathological development they have the general form and significance of appendices epiploicæ.
Subsynovial Lipomas.
—Subsynovial lipomas occur about various joints and tendon sheaths; within the knee they assume a distinctive type which has been called lipoma arborescens, where they take on a dendritic appearance and arrangement. Submucous lipomas are rare. Intermuscular fatty tumors are occasionally met with, an interesting variety being that which develops between the masseter and buccinator muscles. Intramuscular forms rarely occur, as well as a variety known as parosteal, which arises in connection with the periosteum. Fatty tumors also occur within the spinal dura, as well as outside of it within the spinal canal, and more or less lipomatous alterations are common in connection with spina bifida.
Lipomas are ordinarily easy of recognition, save when deeply located. The subcutaneous forms are intimately related with the overlying skin, and have a dough-like consistence which is usually pathognomonic. Tumors, suspected to be fatty, in the middle line of the back or cranium are always to be viewed with suspicion, as they are often connected with congenital meningeal protrusions.
An encapsulated lipoma when thoroughly removed will not return.
Mixed forms of fibrous and fatty neoplasm are occasionally seen, and are referred to as lipoma fibromatosum or fibroma lipomatosum, according as one or the other tissue predominates. These growths are innocent in their character, but call for thorough extirpation. They frequently give rise to considerable discomfort or pain, and are called lipoma dolorosa.
Fibroma.
—Fibromas are tumors composed of fibrous tissue, which, when of pure type, are found to be not so common as was formerly supposed, the majority of tumors hitherto roughly grouped as fibromas containing either muscle tissue or sarcomatous elements, which takes them out of the category of pure fibroma. A typical fibroma is ordinarily dense, and is composed of wavy bundles of fibrous tissue whose cells are long and slender and closely packed together, the mass being permeated by distinct bloodvessels.
Fibroma occurs most commonly in the ovary, the uterus, the intestine, the gum (epulis), in nerve sheaths, and in the skin in the form of so-called painful subcutaneous tubercles and molluscum fibrosum. There is also a fibrous tumor of the skin, known as keloid, sustaining to fibroma the same relation that exists between exostosis and osteoma.
Painful subcutaneous tubercle is a sample of pure fibroma in the shape of a small, flattened, pea-like tumor which never attains great size. It is situated loosely in the subcutaneous structure and may form a visible prominence. Insignificant as it would thus appear, it becomes the seat of exasperating pain, particularly when touched or handled, which may radiate to considerable distances. The etiology of these growths is unknown.
In the ovary, the uterus, the intestine, and the larynx true fibrous tumors are pathological curiosities rather than common lesions.
Fig. 74
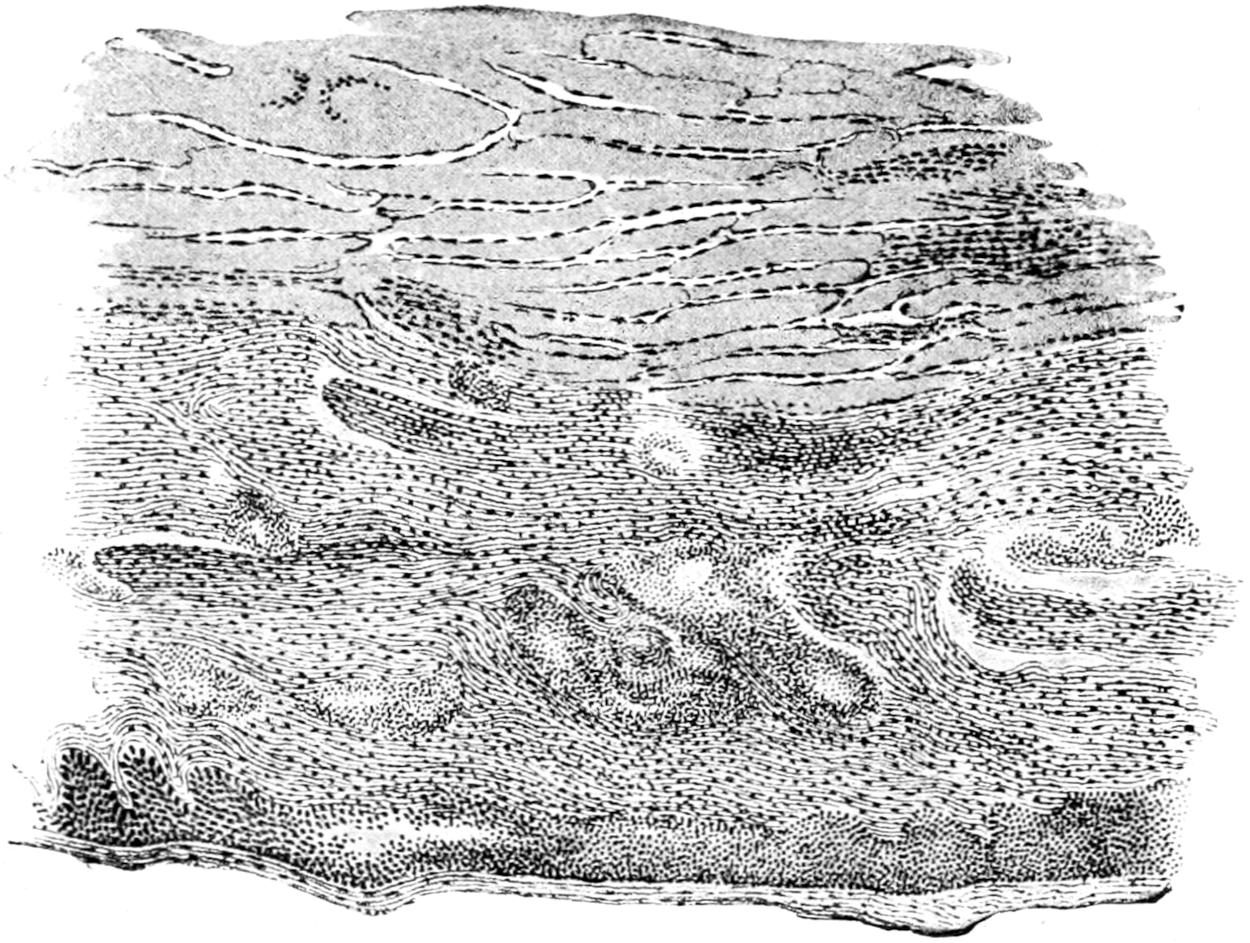
Keloid of external ear: a, dense tissue of skin; b, fibrous connective tissue; c, epidermis. (Klebs.)
Epulis.
—Epulis means any tumor growing upon the gum. The term was formerly applied in an indistinct and too comprehensive way, although it is still retained in literature. But pure fibromas do spring from the fibroösseous structure of the gum and alveolar process. They are covered with the gingival mucous membrane and seem to spring from the periodontal membrane. They seldom attain large size, and then only by neglect. By the pressure of such tumors teeth may be separated and distortion of the mouth produced. They should be promptly extirpated.
Keloid.
—Keloid is a fibrous neoplasm arising mainly in cicatricial tissue, which is essentially fibroid in structure. It is a neoplasm which often follows the general outline of the scar in which it grows, consists in elevation of the surface, ordinarily quite smooth, sometimes of a delicate pink from the dilated vessels which it contains. Keloid is the bête noir of surgeons, as it frequently complicates and disfigures scars which have at first been satisfactory, and since it indicates a condition which it is discouraging to deal with, because when it is removed there is usually recurrence of growth within a few months after cicatrization. It often occurs in stitch-hole scars and upon the site of extensive burns, and may be observed after puncture of the ears for ear-rings, and has also been observed in scars left by smallpox, acne, etc. It is more prevalent in the colored race than in the white. In negroes multiple keloid tumors are often seen, occasionally in large numbers. Their explanation is unknown, and it may be that some trifling injury has preceded each individual tumor (Fig. 74).
The treatment of keloid will be considered in the chapter on the Surgical Diseases of the Skin.
Desmoids.
—This term has been applied to tumors of a certain clinical type which arise from the fibrous structures, usually of the abdominal wall, and produce neoplasms like the fibromas of other parts of the body. The use of the term should be restricted to those tumors which proceed primarily only from muscles, tendons, and aponeuroses, or perhaps from ligamentous and periosteal tissues. These tumors are usually single, attain sometimes considerable size, grow slowly, rarely involve other structures, and not infrequently develop to such an extent as to encroach upon either pelvis or the abdomen, or both. They have been known to attain to the weight even of ten pounds or more. They are usually more or less encapsulated, and are firm and dense in structure. Under the microscope they have the general appearance of cellular fibroma. Sarcomatous elements may be met, while they occasionally undergo cystic degeneration. Their occurrence may be explained, at least in some instances, on the embryological theory of Cohnheim.
Fig. 75

Multiple enchondromas.
The treatment of desmoids consists in their complete extirpation. They should not be allowed to attain large size because their removal may entail a serious weakening of the abdominal wall. There should be such plastic rearrangement of abdominal protecting membranes as to reduce the resulting weakening to a minimum.
Psammoma.
—Psammoma is a term applied to a form of hard fibroma met with in the dura mater, in which there has occurred a petrefaction of some of the cells—i. e., a deposition of calcareous salts, which gives it a gritty or sandy appearance.
Chondroma.
—The true chondroma is a tumor composed of hyaline cartilage. It occurs in the long bones, usually in relation with epiphyseal cartilages, and is often noted during the earlier years of life. While it is usually a solitary tumor, multiple chondromas are often seen, especially upon the hands. These tumors are often encapsulated and form deep hollows, in which they rest. Unless pressing upon nerve trunks they are painless and slow of growth. They are exceedingly dense and hard, and ordinarily immovable. Mucoid softening (i. e., cystic degeneration) is common, and the softened areas may give rise to fluctuation. There may be coincident calcification or ossification in any of these growths. It is noted as a curious circumstance by Sutton that their tissue resembles histologically the bluish, translucent, epiphyseal cartilage seen in progressive rickets.
To the small local hypertrophies of cartilage which are seen especially about joints, about the laryngeal cartilages, and the triangular cartilage of the nose, are given the term ecchondroses. They are most common in the knee in connection with rheumatoid arthritis, and occur as prominences along the margins of the joint cartilage. They may project to such an extent as to be detached by accident, after which they become movable and floating bodies in the joints. Many of the floating cartilages or bodies found in joints are detached ecchondroses, which may be smoothed off by attrition, and may be found singly or multiple, even several hundred existing in one joint.
Chondromatous changes as occurring in sarcomatous tumors have been alluded to. It seems to be easy for connective tissue to form hyaline cartilage, and mixed tumors may thus be seen in connection either with sarcoma, fibroma, or other forms.
Treatment.
—The treatment of chondroma is solely operative. Unless the integrity of a member or a limb be compromised, such a tumor can usually be shelled out from its location, but requires that the matrix be completely extirpated; all of which may call for the use of powerful bone instruments. At other times amputation is the only measure which may relieve from deformity, pain, and disability. The ecchondroses occurring within joints necessitate incision and evacuation, with the most rigid aseptic precautions, with or without drainage. When practised according to modern technique this is almost invariably successful. In former times many lives were lost because of septic infection.
Osteoma.
—Under the head of nomenclature I have already endeavored to distinguish as between exostosis, or irregular bone outgrowth, and osteoma, as a distinct tumor which is composed of bone tissue, with the subvariety odontoma, or tumors of dental origin and structure. Osteoma is regarded by some as ossifying chondroma, for it is nearly always found near epiphyseal lines, and is always covered by hyaline cartilage when thus found. Nevertheless it is not invariably such. We speak of compact or ivory osteoma and of a cancellous form. The former is identical with the compact tissue of the shafts of long bones, and may occur anywhere, but is most common about the cranium, at the frontal sinus, the external meatus, and the mastoid process. Osteomas growing into the frontal sinus of oxen form large, lobulated, bony masses, sometimes weighing several pounds, and as dense as ivory. Some of these tumors growing into the cranial cavity have been regarded as ossified brains. Osteomas in connection with the external auditory meatus may partially obscure this channel and cause deafness. They constitute ivory-like growths, which sometimes defy the finest steel instruments with which the surgeon can supply himself.
Fig. 76
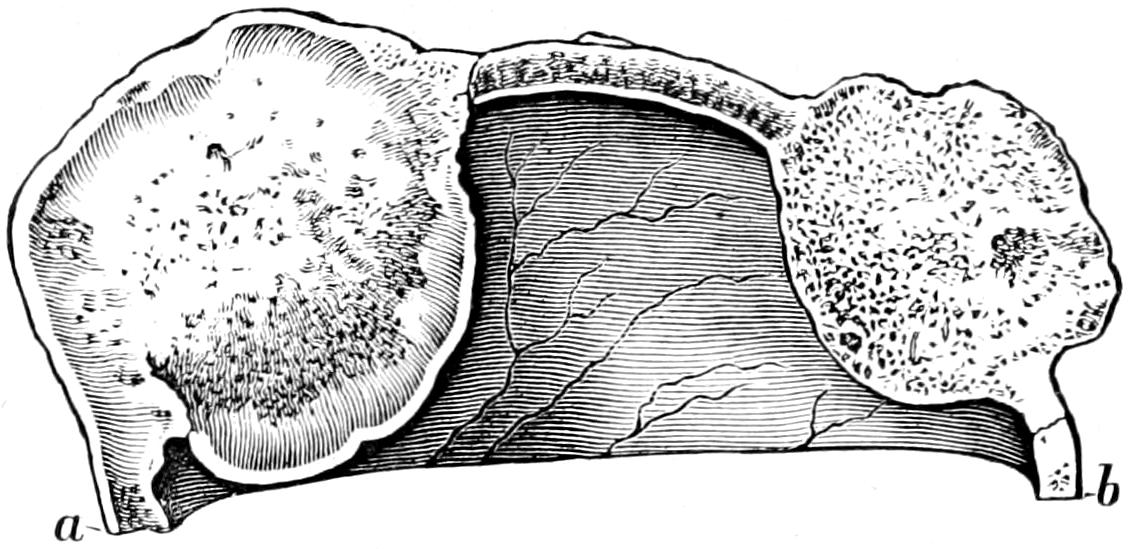
Double osteoma of the skull. (Musée Dupuytren.)
Cancellous osteomas grow in the cranium as well as in the long bones, and, like the compact forms, only occasion pain by pressure upon nerve trunks.
Exostoses.
—Exostoses are classed by Sutton as—
1. Those formed by ossification of tendons and their attachments. There should be excluded from this group such natural or evolutionary processes as the supracondyloid process, the third trochanter of the femur, etc. Over or around such exostoses bursæ will form to mitigate as much as possible the effect of friction. Such an outgrowth is known as an exostosis bursa; it is most frequently seen on the inside of the femur immediately above the knee.
2. Subungual exostoses, occurring usually beneath the nail of the big toe.
3. Exostoses due to calcification of inflammatory exudations, including the rare condition known as myositis ossificans.
PLATE XVII
FIG. 1

Round-cell Sarcoma. (Low power.)
FIG. 2

Spindle-cell Sarcoma. (Low power.)
When a true osteoma is once thoroughly removed there is no tendency to recurrence. Thorough removal, however, calls sometimes for serious and often mutilating operations, which may become dangerous when the growth involves the curve of a rib or a large portion of the skull. At other times amputation is rendered necessary. Special forms require special treatment.
Sarcoma.
—Formerly this name implied a fleshy tumor, and was made to cover many different conditions. Now sarcoma means a tumor composed of immature mesoblastic or embryonic tissue in which cells predominate over intercellular material. Sarcomas are sometimes encapsulated; they merge into and infiltrate the surrounding tissue and disseminate widely, and have usually these propensities and characteristics to such a degree as to constitute malignancy. For the laity sarcomas and carcinomas are together included in the comprehensive term of cancer; for the surgeon they constitute but one form of cancer. Sarcomas are classified, according to the shape of their cells and their disposition, into—
A. Round-cell;
B. Spindle-cell;
C. Myeloid.
To these are added other varieties mentioned below.
Fig. 77
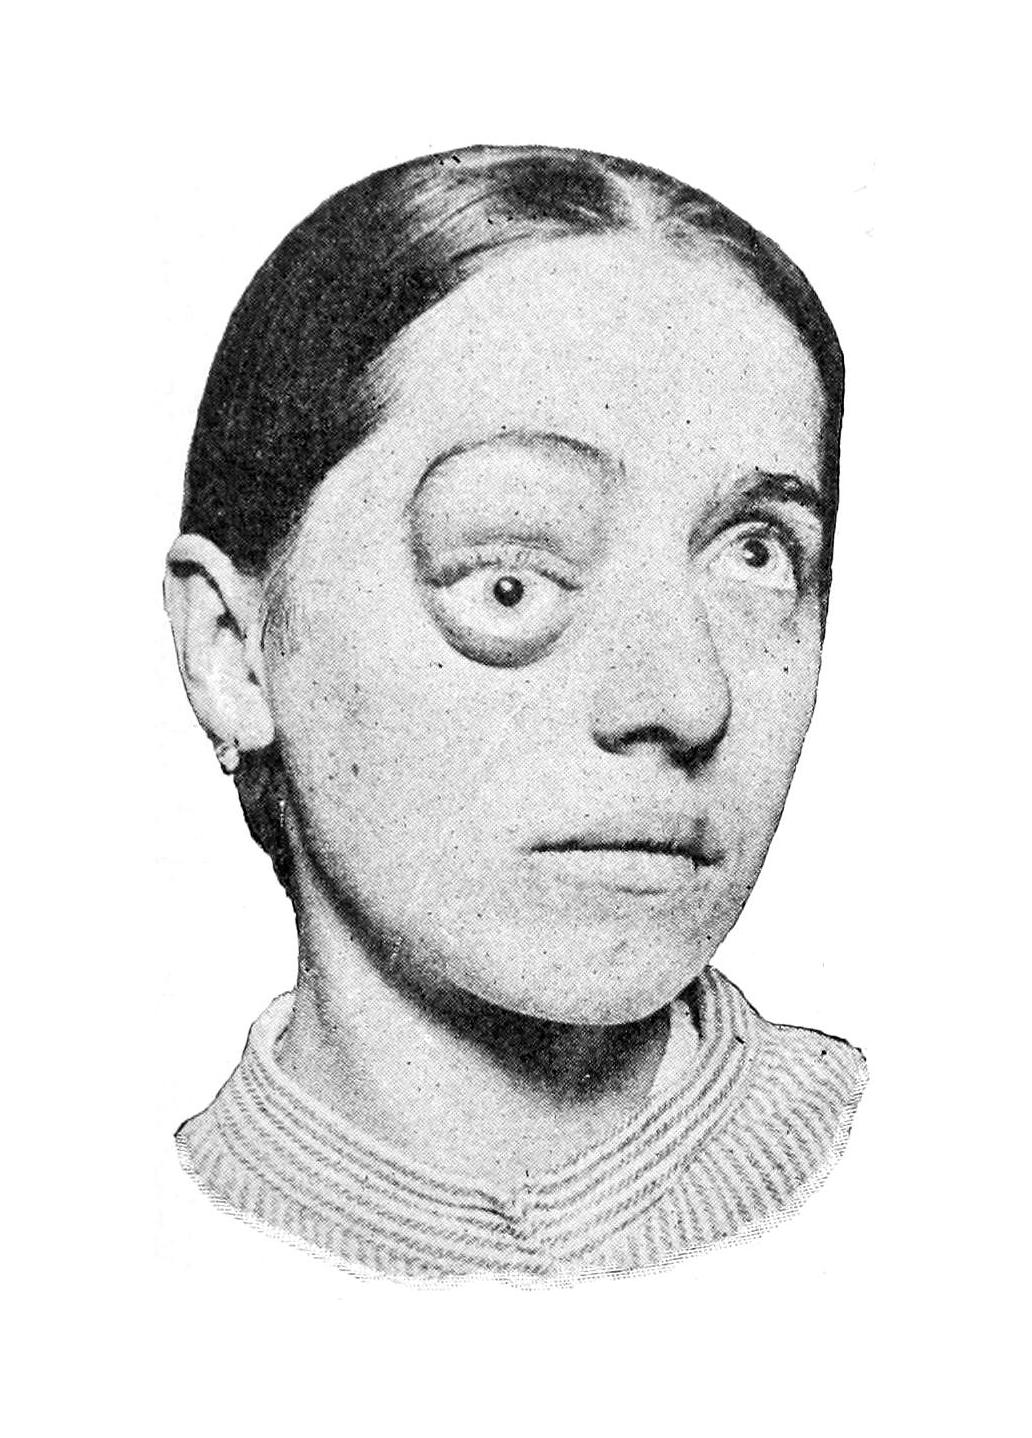
Osteoma of frontal sinus. (Neisser.)
Fig. 78
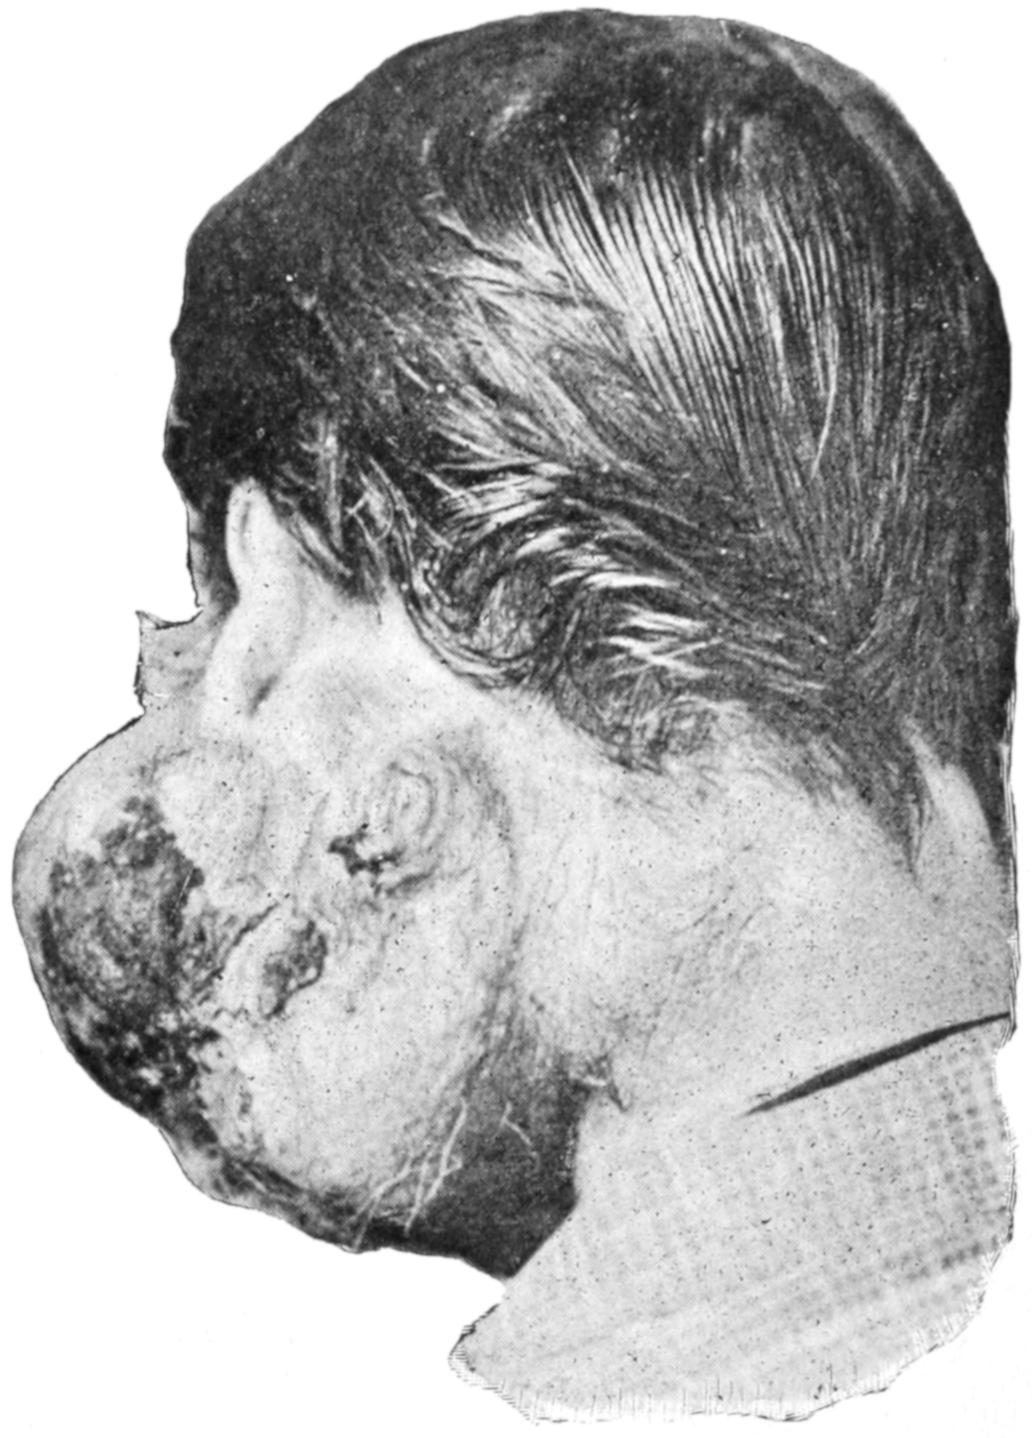
Recurring sarcoma of parotid. (Original.)
A. Round-cell Sarcoma.
—This is simple in construction, and consists of round cells containing very little intercellular substance. The nuclei of the tumor cells stain easily, the cells themselves varying in size in different cases. Bloodvessels lead up to the tumor, but in the interior appear rather as channels. These tumors have no lymphatics: they grow rapidly, infiltrate easily, recur quickly, and give rise to numerous metastatic or secondary deposits. They may affect any part of the human body. The size of the cells is supposed to be in some measure an index of their malignancy—the smaller the cell the more malignant the tumor. They appear at all periods of life. They are perhaps the most commonly seen of malignant tumors in animals. (See Plate XVII.)
Lymphosarcoma.
—This tumor is composed of cells similar to the previous form, but enclosed in a delicate meshwork resembling that of lymph nodes, hence the term lymphosarcoma. Lymphosarcomas are not to be confounded with enlargements nor with the specific granulomas involving these lymphatic structures.
B. Spindle-cell Sarcoma.
—In this form the cells have a spindle shape and run in all directions, so that sections will show them in various shapes and sizes. In some cases the cells are small and slender, in others large. The size of the cell is a measure of the malignancy of the tumor. (See Plate XVII.)
The largest of these spindle cells are frequently striated transversely like voluntary muscle fiber, and tumors composed of this form have been considered as tumors of striped muscle tissue, and are generally called rhabdomyoma. There is no tumor of striped muscle fiber, and the rhabdomyomas of writers generally should be considered as spindle-cell sarcoma, or may be dignified by the name myosarcoma. (See Rhabdomyoma, under Myoma.)
Alveolar Sarcoma.
—This is a rare form, in which the cells, contrary to the general rule of sarcomas, assume an alveolar arrangement strongly imitating that of epithelial cells in carcinoma. Almost invariably, however, on close examination it will be possible to distinguish a delicate reticulum between individual cells, which is never met with in cancer.
C. Myeloid, or Giant-cell Sarcoma.
—In this form the tissue resembles histologically the red marrow of young and growing bone, containing large numbers of multinuclear cells embedded in a matrix of spindle or round cells. These tumors usually occur in the long bones, and when freshly cut look like a piece of liver. They constitute most of the epulides or cases of epulis—i. e., spongy tumors springing from the gums. (See Plate XVIII., Fig. 2.)
Fig. 79
Sarcoma of femur following fracture—i. e., developing in callus. (Original.)
Giant or multinuclear cells should be present in considerable numbers to entitle a tumor to classification in this group. When round cells, spindle cells, or giant cells mingle in nearly equal proportion the tumor should be called a mixed-cell sarcoma.
D. Osteosarcoma.
—Osteosarcoma is something more than sarcoma of bone, which latter may spring from the fibrous or medullary elements. It is sarcoma of the specific bone-forming connective tissue, including the osteoblasts and osteoclasts; in other words, of the stroma of the bone. Under these circumstances real bone develops throughout the tumor, and it is essentially a bony neoplasm. In like manner there may be true osteofibroma. These tumors are to be distinguished, even clinically, from the medullary sarcomas, which develop within the bone and expand it, even to enormous proportions, the bony covering then being a mere shell.
E. Chondrosarcoma.
—Chondrosarcoma resembles osteosarcoma in that it is sarcoma of the stroma of cartilage, or of the specific tissue which produces cartilage. In it true cartilage (white fibrous) also is found throughout the tumor. Chondrofibroma is also possible. (See Plate XIX.)
F. Endothelioma.
—Endothelioma has been called various names, and its true character has been only lately determined. It is composed particularly of the endothelial cells which line the lymph spaces, and which have no peculiar secretion. It is met with most often in the skin (especially of the face), in the parotid region, in the genital glands, the bones, the lymph nodes, and dura.
PLATE XVIII
FIG. 1
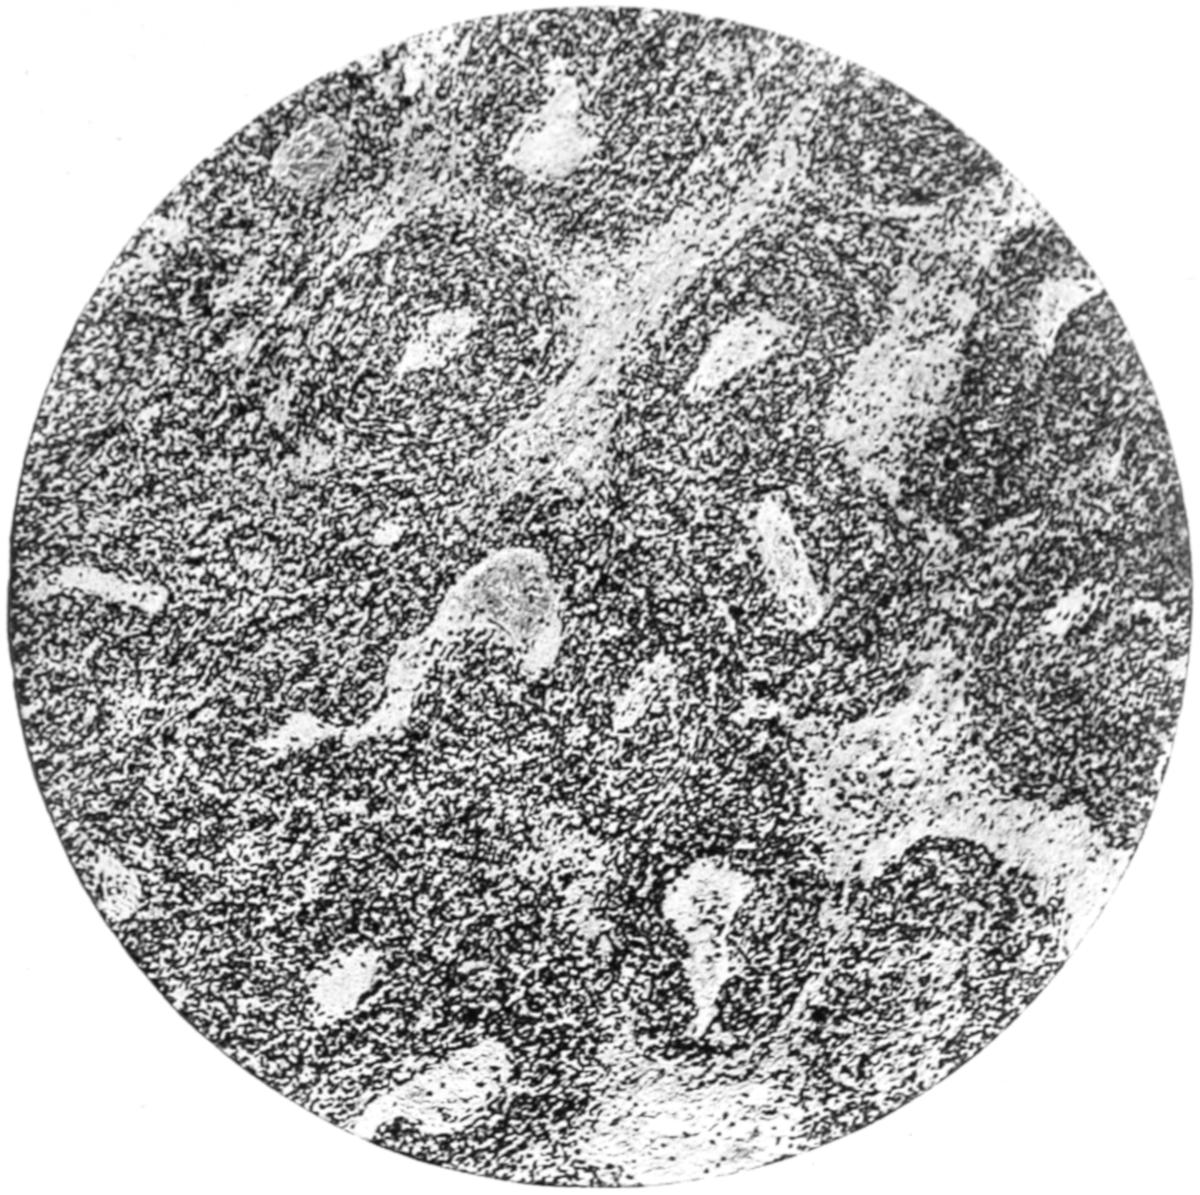
Angiosarcoma. (Low power.)
FIG. 2
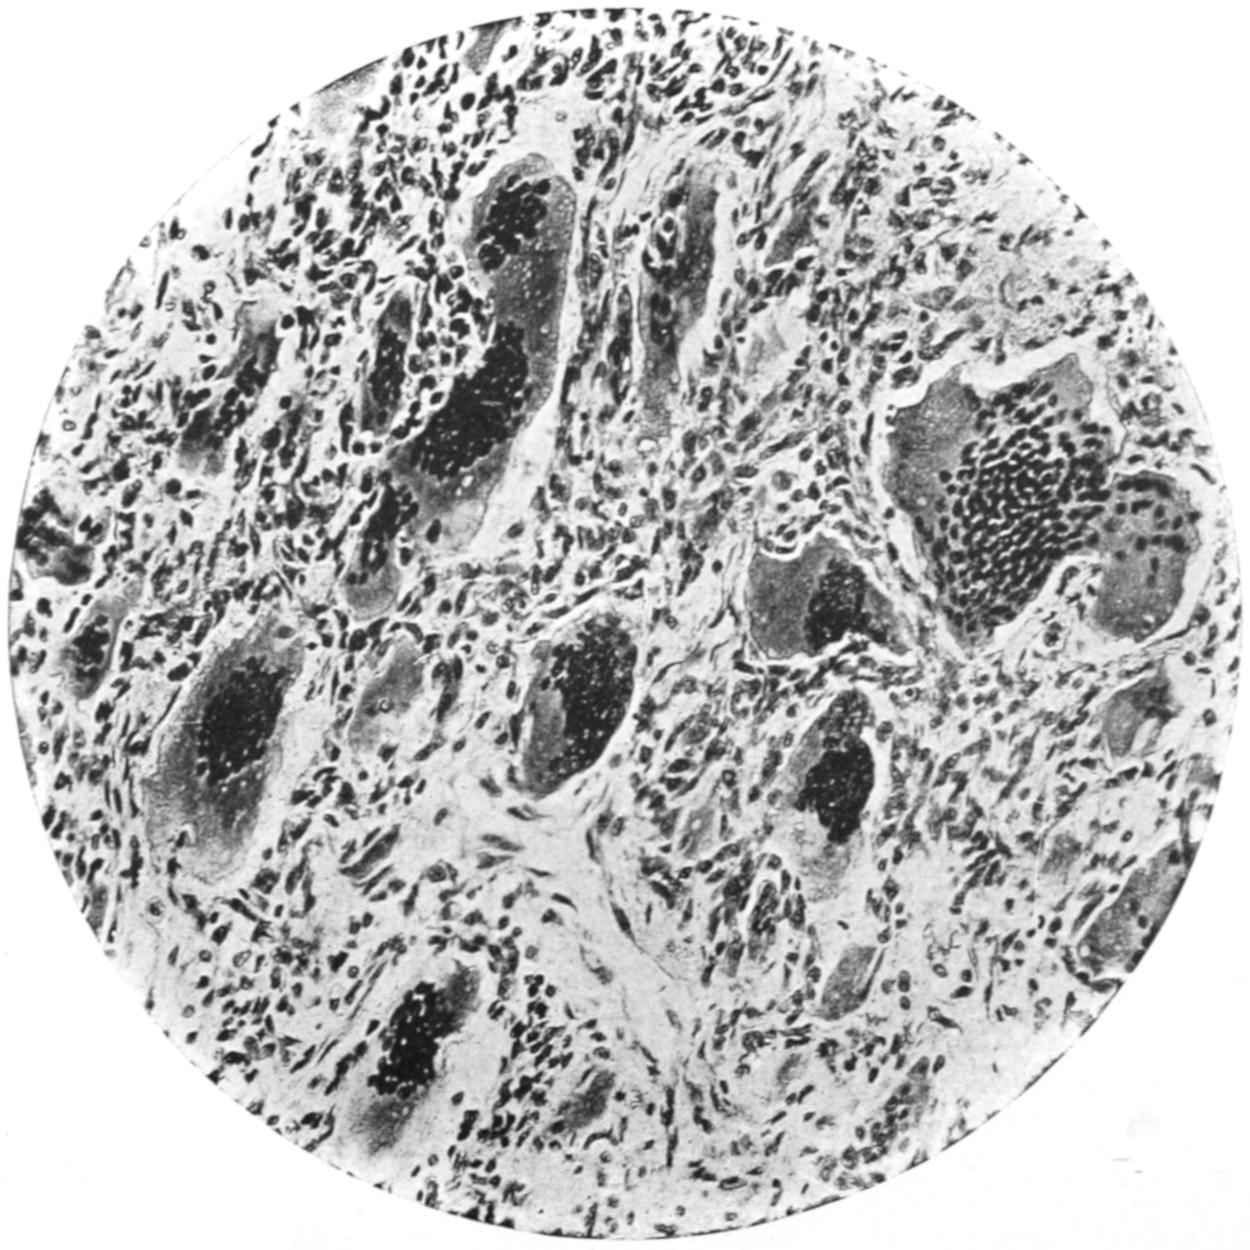
Giant-cell Sarcoma. (High power.)
PLATE XIX
FIG. 1
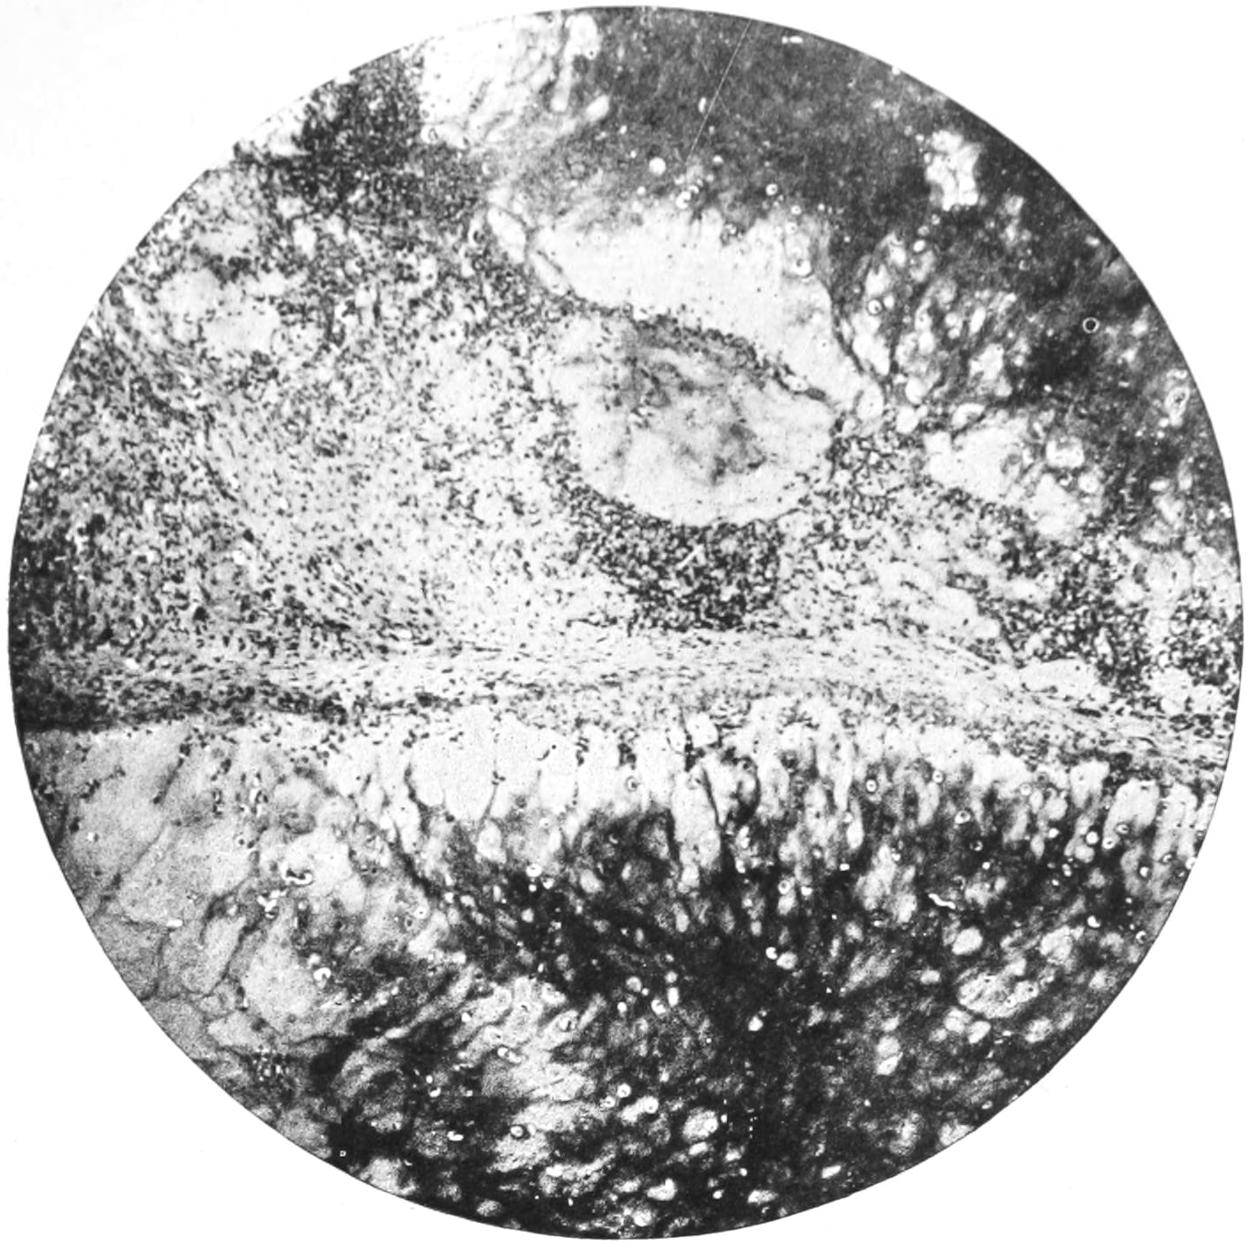
Chondrosarcoma. (Low power.)
FIG. 2
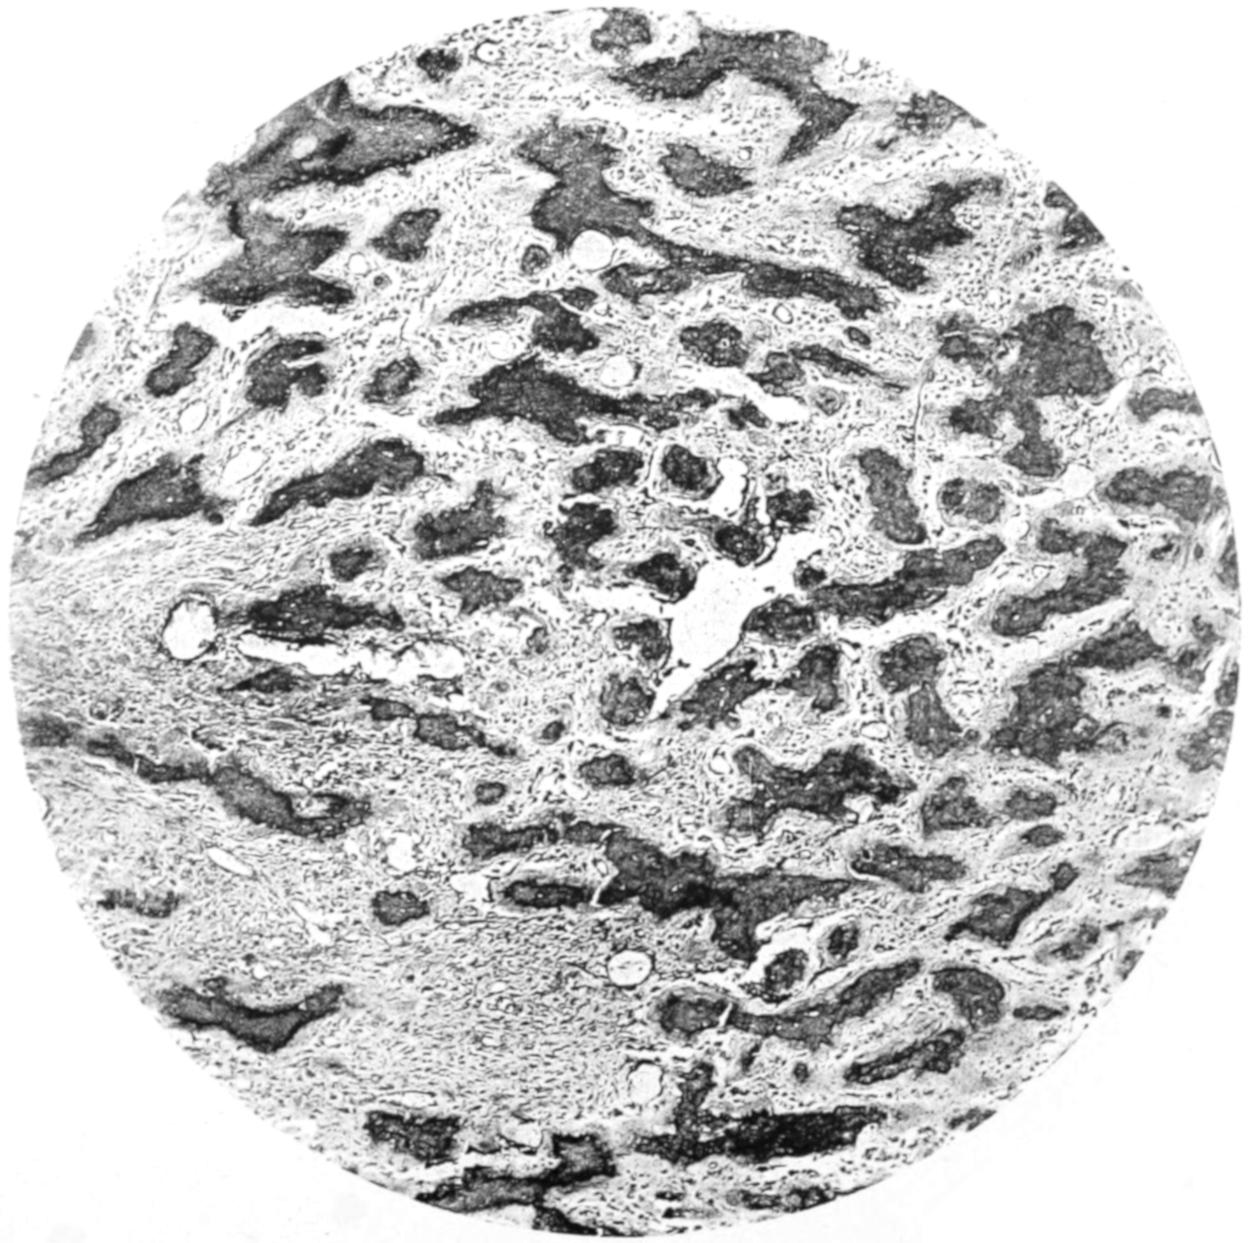
Osteosarcoma. (Low power.)
PLATE XX
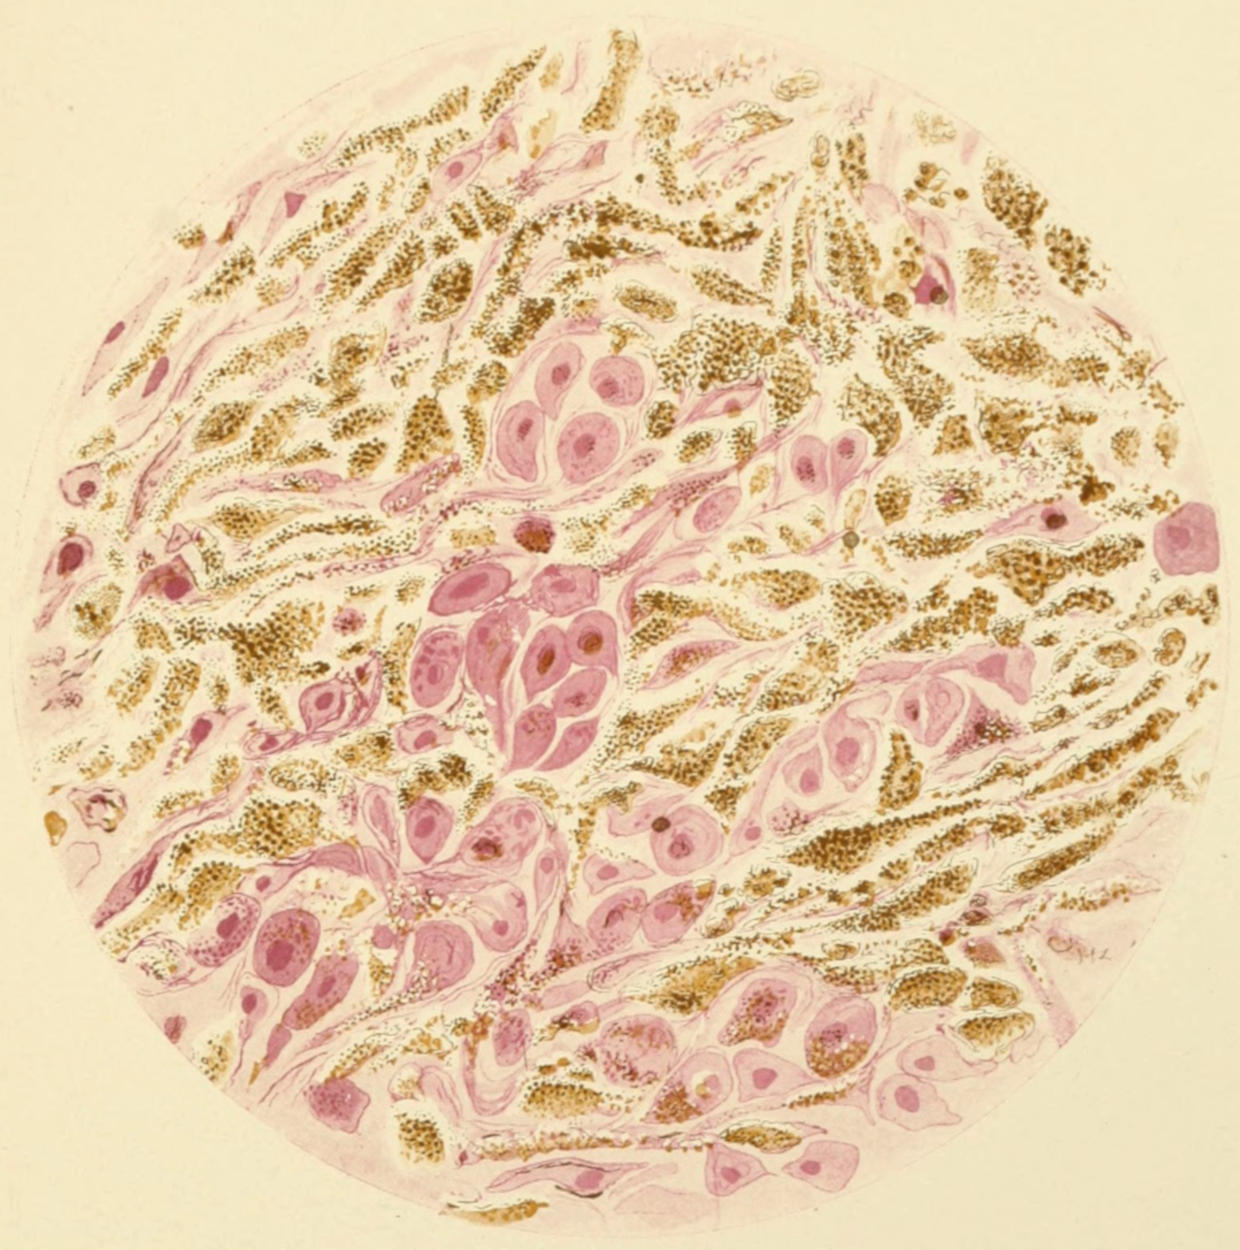
Melanosarcoma of Skin. (Dry high power.)
The microscopic picture of these tumors varies greatly, the endothelial cells often shaping and grouping themselves so as to imitate epithelioma. In doubtful cases the primary location or origin of the growth should be ascertained.
Endotheliomas are mainly of rapid growth, and often show a high degree of malignancy. If thoroughly extirpated before metastasis has occurred, prognosis is fair; but metastases happen early because of the direct connection of the tumor with the lymph current.
Fig. 80
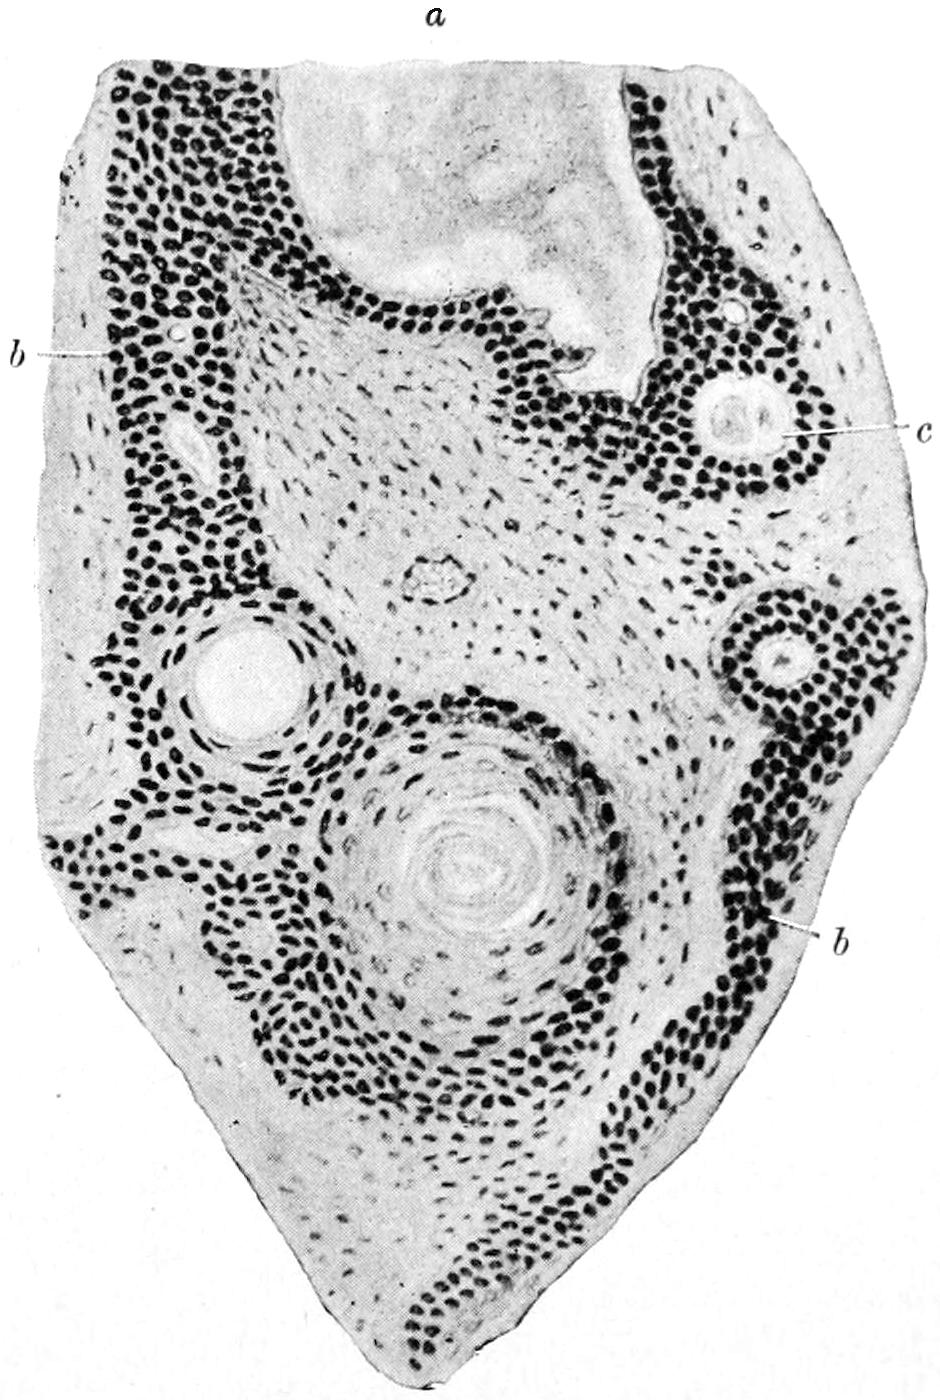
Endothelioma of the soft palate: a, dilated lymph space; b, endothelial cells with beginning cystic formation; c, completely formed cyst. (Volkmann.)
G. Angiosarcoma.
—Angiosarcoma is a sarcoma arising from the adventitia of the bloodvessels. It is characterized by its extraordinary vascularity, the ease with which hemorrhages into the structure of the tumor take place, and the frequency of pigmentation. Peritheliomas constitute a subvariety, met with especially in the kidneys, the bones, and the skin, and originate in the perithelial cells between the capillaries and the perivascular lymph spaces. They are more vascular than the angiosarcomas. The latter are common in the liver. In many cases the cells of these tumors simulate the columnar epithelium of adenocarcinoma. (See Plate XVIII, Fig. 1.)
H. Cylindroma.
—This is a term applied to tumors of the angiosarcomatous type in which hyaline changes have occurred, so that along the vessels appear cylindrical masses of altered cells. Similar appearances are noted in certain endotheliomas and are due to the same hyaline degeneration.
I. Melanosarcoma (better known as Melanoma).
—This refers to the deposition of pigment, rather than to type or shape of cell, the distinguishing feature of these growths being the presence both in the cells and in the intercellular substance of a variable quantity of blackish pigment. Of all the forms the melanotic growths are considered the most malignant. They invariably recur after removal, lead to secondary deposits at long distances, and present the most intractable and incurable forms of cancer. Deposition of pigment in carcinomas is most rare, if ever met with, and the growths of melanotic type should be relegated entirely to the class under consideration. The tumors most often develop from pigmented nevi of the skin, though primary melanoma of the deeper parts of the body is known. These will be treated more fully in the chapter on the Skin. (See Plate XX.)
This name has been variously applied by different writers to different growths. In order to avoid confusion it would be well, in using it, to be definite.
General Characteristics of Sarcomas and Endotheliomas.
—The vascular supply of sarcomas varies within wide limits. In nearly all instances it is of capillary character, the blood circulating rather through vessels without well-marked walls. While large vessels may be found about and in the periphery of these tumors, distinct vascular structure is usually absent from the more internal portions, which will explain the frequency of hemorrhage, its persistency after operation, and the ease with which large extravasations occur. True hematocele may thus take place within sarcomatous tumors, with the usual later cystic alterations, and thus in one way we have the condition known as cystosarcoma.
In attacking these growths the vascular and bloody area may be met just about their margins, the bloodvessels expanding as they arrive at the tumor, and sometimes bleeding extensively. Under most circumstances, however, this hemorrhage can be controlled by packing or by operating at a greater distance from the circumference of the growth.
Metastasis in sarcoma is common, dissemination occurring mainly along the veins, as these growths connect with the venous channels and permit of easy detachment of fragments, which are then carried along as emboli. These emboli pass naturally to the right side of the heart, and thence to the lungs, where it is most common to find secondary growths, except in areas emptying into the portal veins, in which case the liver will be the most common site. Sarcomas are destitute of lymphatics, and dissemination does not occur through these channels.
Infiltration is also a common phenomenon with these growths. This is generally seen in muscular tissue, particularly with growths proceeding from the periosteum and projecting into it.
Sarcomas, like other tumors, tend to grow along the lines of least resistance. Hence processes of these tumors will insinuate themselves into fissures and interspaces, and penetrate perhaps even into the cavities, from which it is hazardous or impossible to remove them. Thus, sarcomas springing from the head of a rib have been known to extend through an intervertebral foramen and give rise to an intraspinal tumor, causing fatal pressure.
Secondary changes are usually seen in sarcomas, the most frequent being hemorrhage. Myxomatous degeneration is also frequent, and gives rise to cystic conditions. Calcification is common, particularly in the slowly growing tumors which arise from bone. Upon the other hand, necrosis (i. e., ulceration) is common in growths which project upon the surface or into any of the open cavities of the body. Ulceration here is growth at a rate faster than nutrition will justify, and gangrene is to be regarded as a failure to supply sufficient blood. It may also mean infection, of which it is a usual expression.
Tumors of this character, which luxuriate upon reaching the surface, and bleed easily upon the slightest touch, were formerly known as fungus hematodes. The name may be preserved for the sake of convenience, but should be held to mean, in almost every instance, a rapidly growing round-cell sarcoma.
Sarcoma is common in the lower animals, particularly so in horses—most common in those of gray color. It is met with also in cows and various other domestic and undomesticated animals.
Myxoma.
—The myxomas are composed of mucous tissue, whose best-known normal representative is the Whartonian jelly of the umbilical cord. True myxoma should be distinguished from myxomatous degeneration, which occurs frequently in cartilage, fibrous tissue, and sarcoma, and which brings about a similar condition of affairs, though of essentially different origin. Myxomas appear under the following forms:
1. Polypi.
—These include many of those which grow in the nose. The pure form of nasal myoma proceeds from the mucous membrane of the nasal passages or sometimes from the accessory sinuses. But most of the so-called nasal polypi are due to edematous hypertrophies of the submucosa. The polypi usually hang as gelatinous tumors of grayish-yellow tint, being present sometimes singly, sometimes in clusters or in large numbers. Their principal effect is to produce nasal obstruction, with, perhaps, subsequent serious disorder, due to decomposition or to extension into the pharynx or other cavities. Similar growths also occur from the mucous membrane of the tympanum, and constitute the common variety of aural polypi.
2. Cutaneous Myxoma.
—Cutaneous myoma is not common. It presents usually as a sessile tumor, although about the perineum and labia the tumors may become pedunculated. It is often difficult to distinguish between a myoma of the skin and a sarcoma of the same which has undergone myxomatous degeneration, and which then should be called sarcoma myxomatodes. The latter tend to recur after removal; hence the importance of exact diagnosis.
3. Neuromyxoma.
Neuromyxoma is a similar condition involving the nerve trunks, and is dealt with under Neuroma.
Myxomas require complete removal, and, in the nose especially, cauterization or destruction of the surface from which they spring. When this is thoroughly done they do not recur; otherwise, they are likely to require subsequent operation.
Myoma.
—The true myoma is a tumor composed of unstriped or involuntary muscle fiber. Until recently it has been customary to divide the myomas into the leiomyomas in contradistinction to the rhabdomyomas, the latter being supposed to be tumors of voluntary muscle fiber. Myomas are met with only where involuntary muscle fiber is found—namely, in the uterus and adnexa, the vagina, the esophagus, alimentary canal, the prostate, the bladder, and the skin. They form encapsulated tumors composed of fusiform muscle cells with a rod-like nucleus, the size of the cells varying greatly in different specimens. The bundles of muscle fibers are much contorted, and it is often difficult in a single section to decide to just what class of cells they belong.
These tumors are most common in and about the uterus, and are referred to as intramural when developing in the true uterine tissue, and submucous and subserous when situated just beneath one or the other of the adjoining membranes. They differ in their rate of growth, are firm in composition, and are moderately vascular, sometimes containing areas of softening and becoming even cystic. In rare instances they become enormously vascular, and are then known as cavernous myomas. Aside from mucoid or colloid changes they occasionally undergo fatty metamorphosis or calcareous infiltration. The latter is possible to such an extent as to lead to a condition of uterine calculi.
Uterine myoma is liable to septic infection, which frequently follows exploration of the uterus or the changes incident to pregnancy or parturition. It then becomes a case for immediate operation. Uterine myomas do not occur before puberty, rarely before the age of thirty-five, and are most common between the thirty-fifth and forty-fifth years of life. They produce disaster not alone by their size, but by hemorrhage, by pressure on adjoining viscera (rectum, kidneys, etc.), and occasionally by torsion of a long pedicle.
Myomas are found in the esophagus, in the walls of the stomach, where they are frequently confounded with malignant tumors, in the prostate and wall of the bladder, and in connection with the skin. As soon as they give rise to inconvenience or to dangerous symptoms they are to be dealt with surgically, as no other treatment has proved of lasting benefit.
The rhabdomyomas deserve but brief description. The striated muscle fibers of which these tumors are composed have been often confused with spindle-shaped sarcoma cells. They are met with almost exclusively in the mixed tumors of the kidney under Teratomas.
Myoma or myofibroma is exceedingly likely to undergo sudden conversion into a form of growth entitling it to be called malignant myoma.
Angioma.
—Angiomas are tumors composed of bloodvessels, and group themselves under three headings, in accordance with the structure of the vascular system:
1. Capillary Angioma, or Nevus.
—Capillary angioma, or nevus, is the most common form of all, and is frequently seen in the skin and subcutaneous tissue. When the condition is spread over a relatively large area it gives rise to a discoloration known as port-wine mark, and called telangiectasis by the pathologists. The condition is often congenital or begins soon after birth. The color of the affected area determines whether the vessels belong to the venous or to the arterial system. These tumors may be found in all parts of the body, on the surface, on the submucous surfaces of the tongue, the inside of the mouth, the conjunctiva, and the vulva. The tendency is toward gradual increase in size; rarely, spontaneous contraction and obliteration occur.
2. Cavernous Tumors.
—These are similar in structure to the corpus cavernosum, and are called erectile tumors. They are common in connection with the skin, and are exaggerated forms of the variety first described, the vessels becoming not merely dilated but cavernous in arrangement. They occur occasionally in the tongue, in the voluntary muscles, and in the liver, and are noted very rarely in the mammæ, in the larynx, and subperitoneally.
A similar condition is met with in the so-called cavernous tumors which involve various organs, especially the thyroid and the liver. In these instances a part or the whole of the organ may be involved, and presents great increase in size and evidences of vascularity.
In cavernous growths of the thyroid are vessels, veins especially, the size of the thumb, while with the ear not touching the body of the patient a distinct venous murmur may be heard.
3. Arterial or Plexiform Angiomas.
—Arterial or plexiform angiomas, when of any particular size, are called cirsoid aneurysm or aneurysm by anastomosis. This form consists of arteries abnormal both in number, length, and diameter, tortuous in arrangement, occurring often in the scalp, but rarely in the perineum or genitalia, and seldom in other parts of the body. (See Aneurysm, Chapter XXIX.) These tumors are liable to rupture from external injury, and necessitate ligation of the main arterial trunks, with perhaps extirpation of the tumor mass.
Recognition of angiomas is not difficult unless they are deeply concealed. The effect of intermitting pressure, the emptying and refilling, and the distinction between arterial and venous growths by the result of alternating pressure and relaxation, either above or below the growth, with discoloration of the skin, and, in the larger growths, audible murmur, leave little doubt of the character of the growth.
When such growths are small they may be dealt with by electrolysis, the needles from both poles being introduced, or that from the negative, the positive being applied upon some neighboring portion of the body. The effect of the electric current is to determine coagulation of the blood in the tissues acted upon, and this is followed by organization of thrombus, conversion of vascular into cicatricial tissue, shrinkage, and possible eventual disappearance of the mass. Radical excision under an anesthetic should be made, dissecting out the mass, securing bleeding vessels, and reuniting the parts by sutures, with the expectation of securing primary union. This is the quickest and in many cases the least disfiguring method. Old methods of ligation of surrounding vessels or the subcutaneous ligature are now practically discarded. The injection methods as formerly practised, especially the use of iron salts in solution, are severely condemned, as death is liable to occur. With electrolysis and excision the surgeon has nearly all the measures which he will need to practise for the medical treatment of angiomas.
Fig. 81
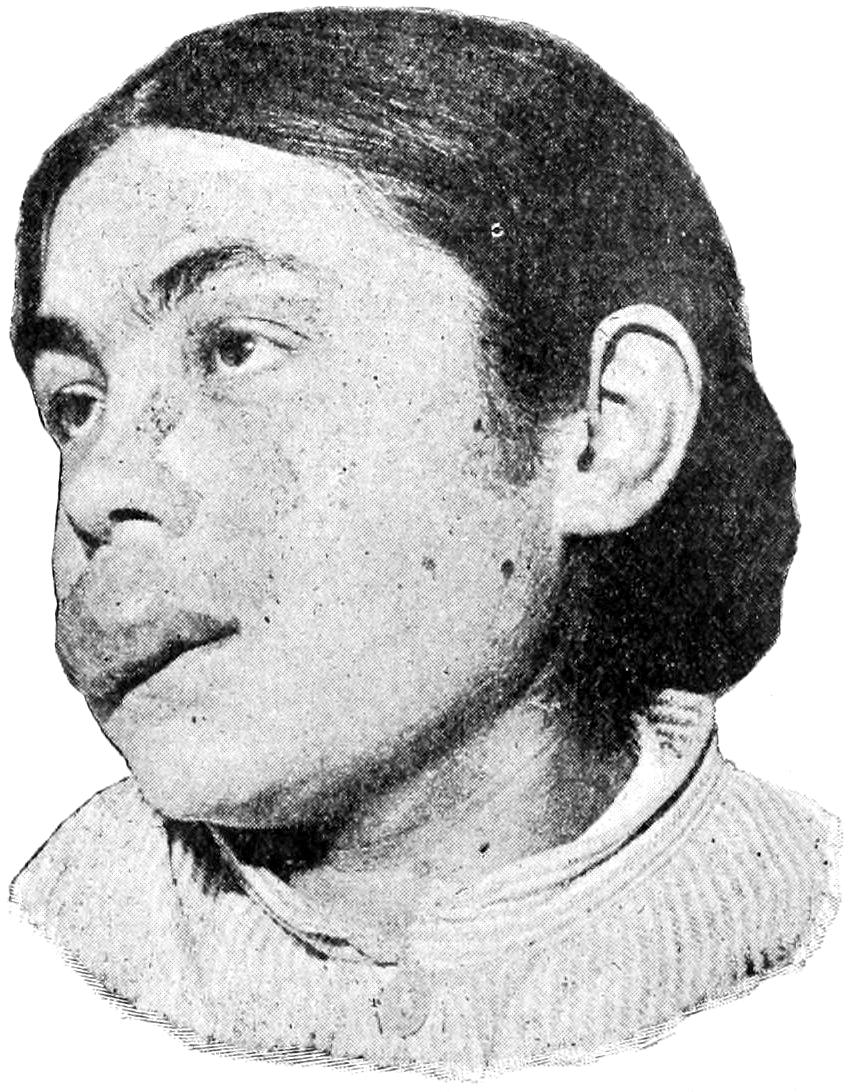
Lymphangioma of lip; macrocheilia. (Neisser.)
Lymphangioma.
—Lymphangiomas are tumors composed of lymph vessels and bear resemblance to the tumors above considered. They may be divided into three varieties:
1. The Lymphatic Nevus.
—The lymphatic nevus is composed mostly of lymphatics nearly normal in size, and occasionally colored red by the presence of bloodvessels. When pricked, pure lymph or blood-stained lymph, will flow. They are usually small, and are noticed during childhood. They may occur anywhere upon the surface of the body or in the mouth, generally in connection with the tongue, where they may appear as large papillæ involving a portion or all of the dorsum. When the lymphatic structures of the tongue are thus enlarged and involved the condition is known as macroglossia, and consists of enlargement of the organ, sometimes to a degree not permitting its retention in the mouth, but leading to its constant protrusion (Fig. 81).
2. Cavernous Lymphangioma.
—Cavernous lymphangioma corresponds to cavernous angioma, and is a condition in which the lymph vessels become positively cavernous and sacculated.
3. Lymph Cysts.
—Lymph cysts are the still more aggravated form which lymphatic dilatation may attain, and are usually encapsulated, complicated with more or less tense tissue, and produce a condition of the parts, especially about the scrotum and labia, to which the term elephantiasis is often applied (Fig. 83).
The question of congenital occlusion or dilatation of lymph channels is one which has been made the subject of large separate monographs (especially by Busey). Numerous tumors, essentially of lymph-vascular origin, are found upon the lips, in the neck, and elsewhere, which grow slowly, are more or less elastic and spongy upon pressure, are frequently covered with skin, from which hair grows most luxuriantly, and in which pigment or papillomatous structures are dispersed. These tumors are called cavernous tumors, are of slow growth, and undergo spontaneous involution, but usually require surgical relief. They are often confounded with branchiogenic and other congenital cysts of the neck.
Treatment.
—The treatment for the smaller lymphatic tumors is simple, but here electricity is less to be relied upon and excision is more urgently demanded. Electrolysis will cause coagulation of blood, but not of lymph—at least not to nearly the same extent; consequently its usefulness is restricted to blood-vascular tumors. Excision, then, is the best remedy. When this is impracticable much can be done by galvanopuncture or ignipuncture, the cicatricial contraction following multiple punctures leading to reduction in size of the affected part. The enlargement of the tongue spoken of above as macroglossia may be treated by ignipuncture or by electrolysis, if necessary under an anesthetic, the effect of the electric current here being not to produce coagulation, but apparently absorption of fibrous tissue and changes which come slowly rather than by obliterative processes.
Fig. 82
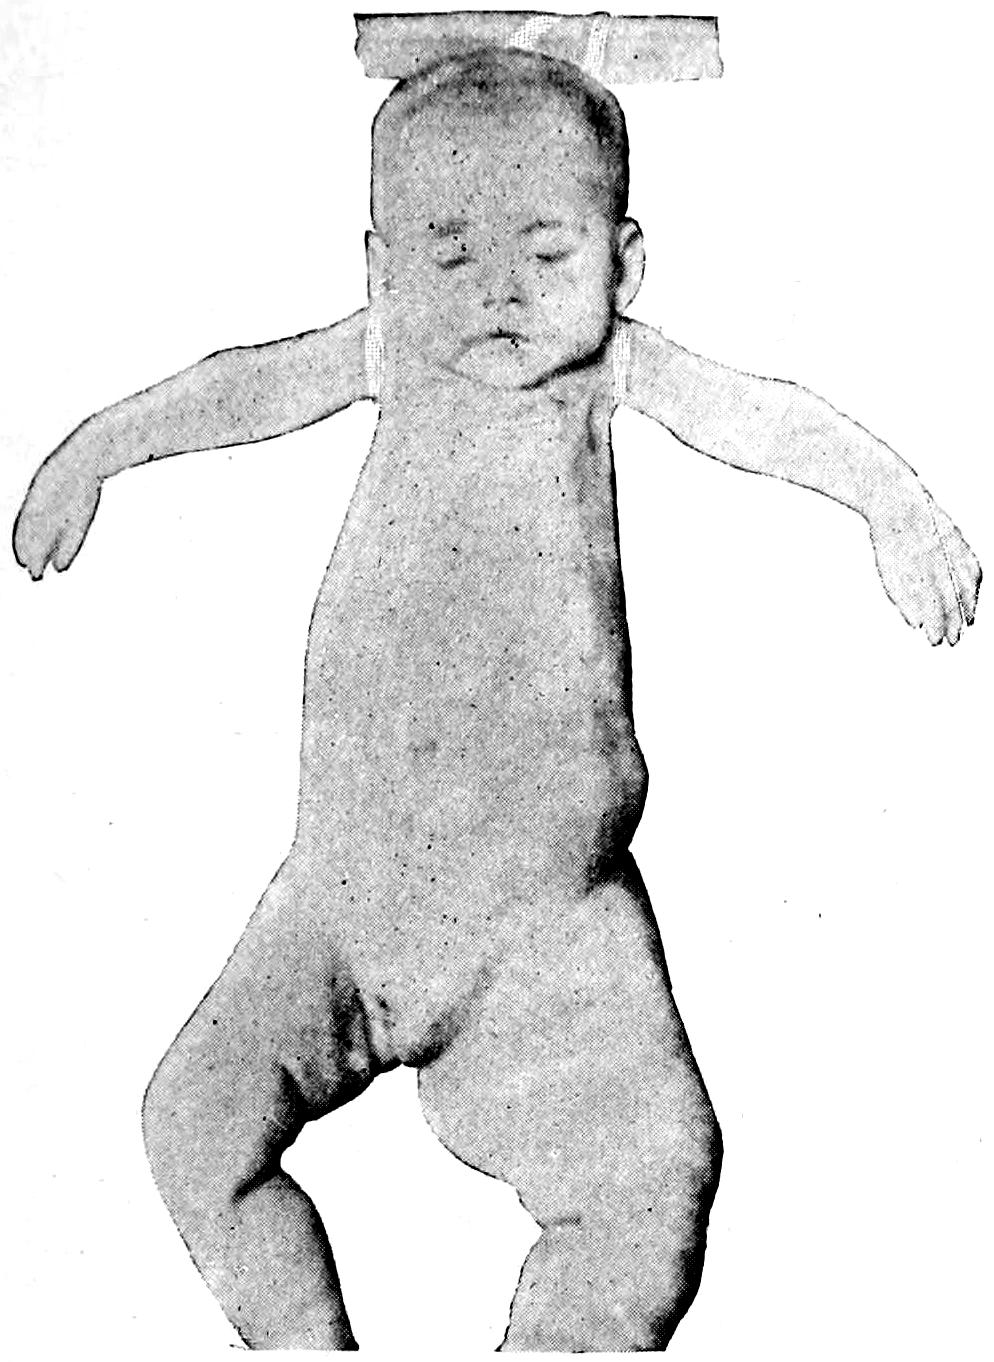
Congenital lymphangioma. (Original.)
Fig. 83
Lymphangioma of lower extremity. (Original.)
5. Tumors of Nerve Elements.
Glioma.
—Glioma is a malignant tumor developing directly from actual nerve structure or that of the original nerve elements, and is clinically allied to the sarcomas. It arises from the neuroglia, and hence is confined to the central and peripheral nervous system, mainly the former. It is most common in the brain, the cord, and in connection with the optic nerve and fundus of the eye. It is often extremely vascular, the vessels being sacculated, and is usually met with in solitary form. When near the surface of the cortex such a tumor may appear like a great convolution (Virchow). In the basal portions of the brain it may attain considerable size. In the cord it is rare, usually limited to the cervical region. In the orbit and eye it may produce marked exophthalmos. It is more frequent in the young than in the aged.
Glioma is an exceedingly malignant form of tumor, and operation is rarely performed sufficiently early to more than prolong life. Dissemination by continuity is the rule rather than metastasis. It kills usually by its pressure effect on the nerve centres.
Neuroma.
—True neuromas spring from the structures of nerve trunks, which trunks may also be the site of other tumors, mainly fibromas and sarcomas, with which neuromas may be easily confounded. The most common nerve tumor is the neurofibroma, which grows from the structure of a nerve sheath, its long axis usually coinciding with that of the nerve trunk. Tumors of this class vary greatly in size, are often multiple, and in other instances affect nearly all the nerves in the body. They are extremely liable to myxomatous degeneration, which will account for many of the instances reported as myxoneuroma, etc. They attack cranial and spinal nerves alike, and no nerve or nerve root in the body is exempt. The sensory nerves appear more liable to attack than the motor. The nerve least often attacked is the optic. They are not rare upon the roots of the spinal nerves, in which location they may attain to such size as to press upon the cord and induce paraplegia. Multiple neuromas are often associated with molluscum fibrosum (q. v.). There is an instance on record in which 1600 of these tumors were found after careful dissection of the neuroskeleton, and another in which at least 2000 were found, 60 of them involving the pneumogastric trunks and their branches.