Part 2 — ANATOMY OF THE PERITONEUM IN THE SUPRA-COLIC COMPARTMENT OF THE ABDOMEN. (continued 2)
Reading edition
In the Selachians the liver arises as a ventral outgrowth at the hinder end of the foregut immediately in front of the vitelline duct, thus bringing the liver from the beginning into close proximity with the vitelline veins entering the heart. Almost as soon as formed the outgrowth develops two lateral diverticula, opening into a median canal. The two diverticula are the rudimentary lobes of the liver and the median canal uniting them is the rudiment of the common bile-duct and gall-bladder.
In the Teleosts the liver arises quite late (in the trout about the 25th day) as a solid outgrowth from the intestinal canal close to the heart. In the Amniota the liver arises in the same position as in the Anamnia, but, at least in birds and mammals, shows its bifurcation almost, if not quite, from the start. The two forks embrace between them the omphalo-mesenteric or vitelline veins just before they empty into the sinus venosus of the heart.
In the chick the liver appears between the 56th and 60th hour, the right fork being always of greater length but less diameter than the left. The hepatic outbud in the rabbit appears during the 10th day, and during the 11th day begins to send out branches.
In man, as above stated, the bud appears well marked in embryos of 3 mm.
[Certain adult variations make it appear possible that there are two human embryonic hepatic buds, a cranial and a caudal, as is the case in birds.]
I. B. Comparative Anatomy of the Liver.—The liver, phylogenetically a very old organ, occurs in all vertebrates, for the cæcal diverticulum of the intestine of amphioxus (Fig. 49) has probably the significance of a hepatic outbud.
The primitive form of the liver is symmetrically bilobed, a type which is seen well in the chelonian organ (Fig. 238).
Fig. 238.—Pseudemys elegans, pond turtle. Alimentary canal. (Columbia University Museum, No. 1437.) Fig. 239.—Stomach, mid-gut, pancreas, and liver of Boa constrictor, boa. (Columbia University Museum, No. 1832.)
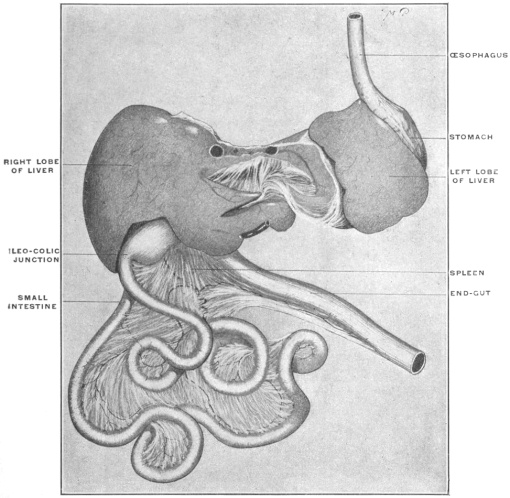
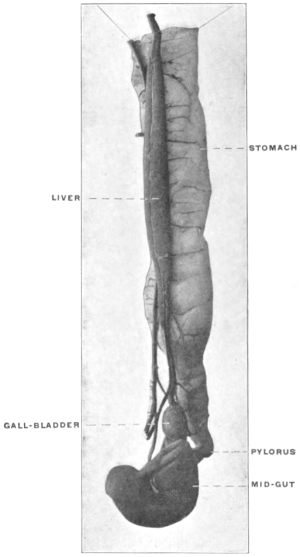
In size the liver is subject to great variations. It is usually larger in animals whose food contains much fat. Hence carnivora in general have a larger liver than herbivorous animals.
Its shape also varies considerably, depending on the form of the body cavity and on the amount and disposition of the available space. Hence in the snakes the organ appears long drawn out, flattened, almost ribbon-like (Fig. 239), while the relatively very large coronal diameter of the body cavity in the turtles permits the liver to expand transversely (Fig. 238).
Fig. 240.—Liver of Macacus cynomolgus, Kra monkey. (Columbia University Museum, No. 28/1833.) Fig. 241.—Liver of Pleuronectes maculatus, flounder. (Columbia University Museum, No. 1679.)
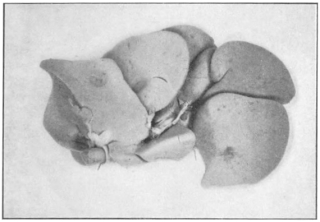
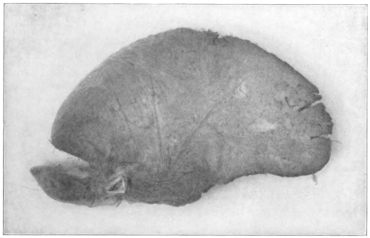
In general, when the liver is large and the available space for its reception limited, it is usually split into several (two to seven) lobes, which permit, by mutual displacement, the accommodation of the organ to varying space-conditions of the body cavity (Fig. 240). Under the opposite circumstances, on the other hand, even the primitive bilobed character may disappear and the liver is then unlobed (Fig. 241).
The presence or absence of a gall-bladder depends apparently largely on the character of the food and on the habitual type of digestion. In many vertebrates digestion is carried on nearly continuously, without marked interruption, especially in many ungulates, ruminants and rodents. In such animals the gall-bladder is absent. It is also absent in several birds (most Parrots, Doves, Ostrich, Rhea americana, the Cuculidæ, Rhamphastos, etc.). This variability emphasizes the morphological fact that the biliary bladder is only a modified portion of the hepatic duct system, as shown by the development above outlined.
A great variety is observed in the arrangement of the biliary ducts, through which, at the period of intestinal digestion, bile passes from the liver and gall-bladder into the intestine, while in the intervals of digestion the secretion is only carried from the liver to the bladder. The following main types of the biliary duct system may be recognized:
Fig. 242.—Schema of hepatic and cystic ducts. (Nuhn.) Fig. 243.—Schema of hepatic and cystic ducts. (Nuhn.)
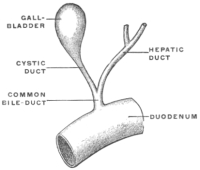
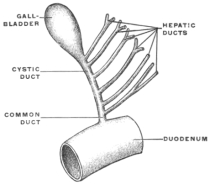
Fig. 244.—Schema of hepatic and cystic ducts. (Nuhn.) Fig. 245.—Schema of hepatic and cystic ducts. (Nuhn.)
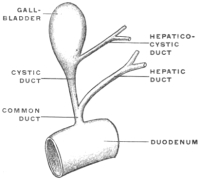
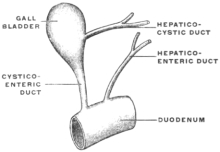
1. The hepatic duct joins the cystic to form the common bile-duct, entering the duodenum by passing obliquely through the intestinal wall (Fig. 242). This form is encountered in man and in most mammals. It is also found in some birds (Buceros), many amphibians, and in some fish (Lophius). Instead of one hepatic duct two may join the cystic duct separately to form the common bile duct (Phoca litorea), or the number of hepatic ducts may be further increased. The separate hepatic ducts then unite successively with the cystic duct. This occurs in many mammals (as Tarsius, Galeopithecus, monotremes) and in some fishes (Xiphias, Trigla, Accipenser) (Fig. 243).
2. Of two hepatic ducts only one helps to form with the cystic duct the common duct, while the other leads from the liver transversely into the bladder, especially into the neck, forming the hepatico-cystic duct (Fig. 244). This arrangement is found in several mammals (calf, sheep, dog).
3. No common bile-duct is formed. The hepatic and cystic ducts each empty separately into the intestine (hepato-enteric and cysto-enteric ducts), while a hepato-cystic duct carries the bile directly from the liver to the gall-bladder (Fig. 245).
Lutra vulgaris among mammalia, the majority of the birds and several reptilia present this type.
When the gall-bladder is absent a single large hepato-enteric duct is found, or instead a number of smaller ducts which enter the intestine successively.
I. C. Development of Vascular System of Liver.—In order to comprehend the peritoneal relations of the adult liver it is absolutely necessary to have a clear understanding of the development of the vascular system in connection with the gland.
For our purpose, in the first place, a serial consideration of the successive stages, illustrated by schematic diagrams, will prove most practicable. These diagrams represent the structures in the dorsal view, i. e., in the position which they would occupy in the adult liver with the gland resting on its upper or convex surface and with the ventral sharp margin turned toward the beholder (see Fig. 259).
The development of the venous system, especially in connection with the liver, presents a somewhat complicated series of successive conditions. After having become familiar with the principal typical embryonal stages, as shown in the following diagrams, the student is strongly recommended to cement this knowledge by the comparative examination of the venous system. The permanent veins of the lower vertebrates, while in many cases not strictly homologous to those of the higher forms, yet are excellent objects for study, since they serve to illustrate temporary stages in the development of the mammalian venous system, and to that extent are of aid in comprehending one of the most difficult and important chapters in human anatomy. At the conclusion of the diagrammatic consideration of the mammalian development a number of comparative facts will be put together for this purpose.
Fig. 246.—Diagram of embryonic vascular system, without the portal circulation. (Parker, after Wiedersheim.) The dorsal aorta is formed by the junction of the right and left aortic roots arising from the confluence of the branchial arterial arches. Fig. 247.—Diagram of the circulation of the yolk-sac at the end of the third day of incubation in the chick. (After Balfour.) The median portion of the first aortic arch has disappeared; but its proximal end forms the external, its distal the internal carotid arteries. The whole blastoderm has been removed from the egg and is viewed from below. Hence the left appears on the right, and vice versa. Arteries in black. Veins in outline.
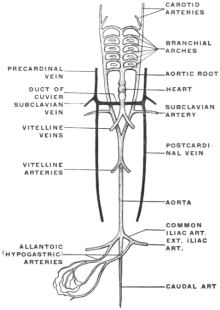
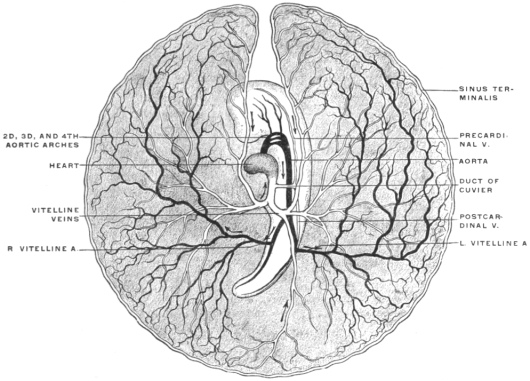
1. Early Stage.—In the earlier developmental stages in mammalian embryos the primitive dorsal aorta extends caudad along the ventral aspect of the vertebral axis, giving off paired vitelline or omphalo-mesenteric arteries to the yolk-sac and allantoic arteries to the embryonic urinary bladder or allantois (Figs. 246 and 247).
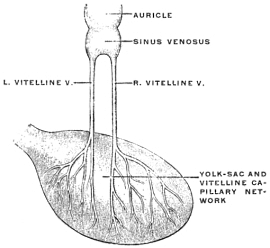
The blood is returned from the vascular area of the yolk-sac by two vitelline or omphalo-mesenteric veins, which unite near the heart to form a common trunk, continued as the sinus venosus into the caudal or auricular extremity (venous end) of the primitive tubular heart (Figs. 246, 247 and 248).
2. Development of Allantois. Stage of Placental Circulation.—The placental circulation, replacing the temporary vitelline circulation of the earliest stages, is inaugurated by the appearance of two umbilical veins, which pass cephalad, imbedded in the tissue of the ventral mesogastrium, to empty into the sinus venosus near the vitelline veins (Fig. 249). The umbilical veins return the oxygenated blood from the placenta to the embryo. At first the right umbilical vein is the larger of the two.
Fig. 248.—Schema of vitelline veins. Fig. 249.—Schema of umbilical veins, early stage.
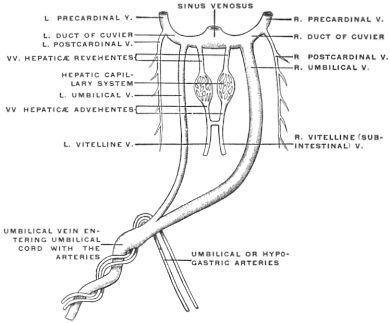
The sinus venosus at this time also receives two large veins, transversely directed, called the ducts of Cuvier, which are formed near the heart by the union of the anterior cardinal (primitive jugular) and posterior cardinal veins, draining respectively the head end of the embryo, and the body walls and Wolffian bodies.
The vitelline veins are placed on each side of the primitive small intestine, and become connected with each other by a broad anastomotic branch (Fig. 249). When the hepatic outgrowth buds from the duodenum the vitelline veins send out branches which break up into a wide-meshed capillary network in the mesodermic tissue enveloping the hepatic cylinders. Hence at this period the circulation in the vitelline veins is made up of three districts:
(a) Distal segment of veins, coursing along duodenum, and joined by a transverse anastomosis, before reaching the liver bud (subintestinal veins).
(b) Middle segment, from which capillary vessels are derived, ramifying upon and between the developing hepatic cylinders.
(c) Proximal segment, formed by the continuation of the proximal part of the vitelline veins into the sinus venosus of the heart.
Fig. 250.—Schema of primitive portal circulation.
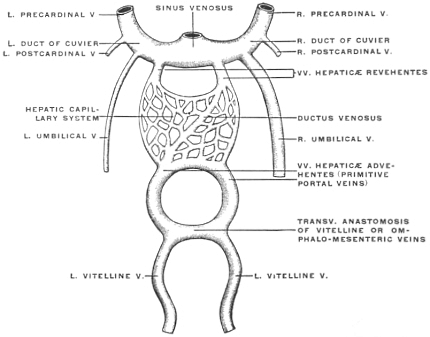
3. Formation of Portal Circulation. A.—With the further development of the liver the direct connection of the distal segment of the vitelline veins with the sinus venosus becomes lost, the intermediate segment being entirely broken up into an intrahepatic network (Fig. 250). Hence all the blood brought to the liver by the vitelline veins (venæ hepaticæ advehentes) passes through the hepatic capillary circulation, before it is carried by the proximal segment of the vitelline veins (venæ hepaticæ revehentes) into the sinus venosus. The amount of this blood increases with new connections which the vitelline veins make with the venous radicles developing in the intestinal tract and its appendages. In proportion as, with the development of the placenta and reduction of the yolk-sac, the original significance of the vitelline veins as nutritive and respiratory vessels disappears, this secondary connection of the vitelline veins with the veins of the alimentary tract becomes more and more important, until finally the original vitelline veins, now properly called omphalo-mesenteric veins, return the blood from the intestinal tube, pancreas and spleen to the liver.
The venæ hepaticæ advehentes, becoming connected in this way with the developing intestine, pancreas and spleen, form the rudiments of the future portal system, while the venæ hepaticæ revehentes are prototypes of the hepatic veins of the adult circulation.
B. Development of the Portal Vein.—The distal subintestinal segments of the vitelline veins are early united by a transverse anastomotic branch. The section of the veins above this anastomosis is seen already in Fig. 250 to have assumed an annular shape, while the veins below the primary anastomosis are approaching each other to form a second ring-like junction.
Fig. 251.—Schema of further development of portal circulation and connection of same with umbilical veins in early stages.
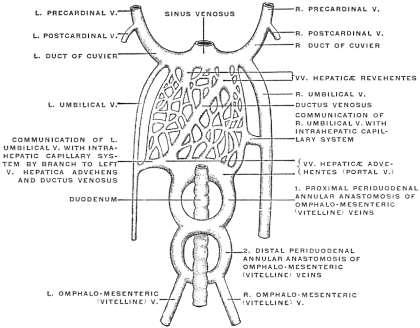
Fig. 252.—Second stage in development of circulation through portal and umbilical veins. The proximal segment of the main portal vein is formed by the persistence of the left half of the distal and right half of the proximal periduodenal vascular ring of the omphalo-mesenteric veins. The distal segment of the main portal vein is the product of the fusion of the omphalo-mesenteric veins, and becomes connected with the veins of the intestinal canal, pancreas, and spleen. The proximal terminal segment of both umbilical veins becomes included in the system of the venæ hepaticæ revehentes.
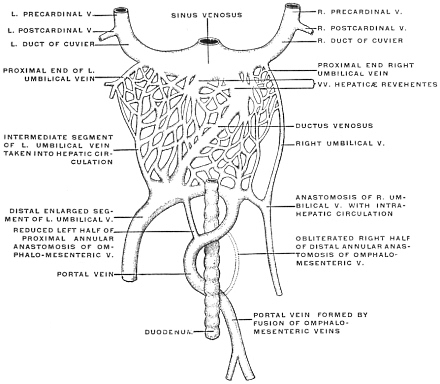
Fig. 253.—Third stage in development of portal and umbilical veins during the placental period.
In Fig. 251 the subintestinal segments of the two vitelline veins are seen to have communicated with each other by transverse anastomotic branches around the duodenum, two of these branches being situated ventrad and one dorsad of the intestinal tube. These branches, and the portions of the primitive vitelline veins between their points of derivation, form two vascular loops or rings, encircling the primitive duodenum (Fig. 251).
The distal portions of the vitelline veins, before reaching the caudal annular duodenal anastomosis, next fuse into a single longitudinal vessel which also receives the veins from the stomach, intestine, spleen, and pancreas, and forms the beginning of the portal vein.
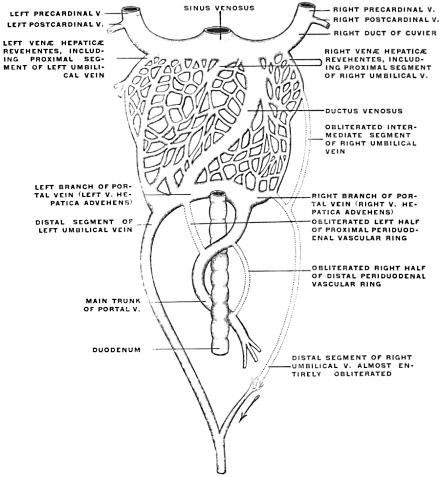
By atrophy of the right half of the lower, and of the left half of the upper duodenal venous ring (Figs. 252 and 253), the proximal portion of the portal vein is formed as a single vessel, taking a spiral course around the duodenum (Fig. 256). Hence in the adult the portal vein and its principal branch (the superior mesenteric vein) crosses over the ventral surface of the duodenum (third portion), turns along the mesal side of the second portion, and then continues to the liver along the dorsal aspect of the first portion (Fig. 254). Note—In comparing Fig. 254 with the schematic figures it should be noted that the same presents the parts in the ventral view, while the schemata offer the dorsal aspect.
4. Changes Leading to the Final Arrangement of the Umbilical Veins.—A very important rearrangement of the umbilical veins takes place. These veins originally course in the lateral abdominal wall, close to the fold of the amnion (Fig. 255), and then turn cephalad of the developing liver along the septum transversum to empty into the sinus venosus at each end (Figs. 249 and 250). The right umbilical vein is at first the larger.
This symmetrical arrangement, and the direct connection of the umbilical veins with the sinus venosus, now becomes lost by the occurrence of the following changes:
1. At first (Fig. 249) all the blood carried to the liver by the omphalo-mesenteric veins passes through the hepatic capillary network before being conducted by the venæ revehentes to the sinus venosus. Very early, however, a new intrahepatic channel develops, the ductus venosus (Figs. 250-253), which passes obliquely between the entrance of the left omphalo-mesenteric vein into the capillary system (l. v. advehens) and the termination of the right omphalo-mesenteric vein (r. vena revehens) in the sinus venosus.
In human embryos of 4 mm. the ductus venosus can already be distinguished, and in embryos of 5 mm. the vessel has assumed considerable proportions.
2. A communication is next established on both sides between the capillary hepatic network in the portion of the liver nearest to the abdominal wall and the umbilical veins as they ascend imbedded in the abdominal wall (Fig. 251).
This connection is usually from the start larger on the left side and connects with the left omphalo-mesenteric vein just at the point where the same is about to be continued into the ductus venosus. This connection becomes rapidly larger, so that the ductus venosus, which at first appeared merely as an anastomotic channel between the left omphalo-mesenteric vein and the terminal portion of the right omphalo-mesenteric vein, now forms the main continuation of the left umbilical vein. This vessel grows very rapidly up to its connection with the ductus venosus and soon exceeds the right umbilical vein in size (Fig. 252). Beyond the ductus venosus on the other hand the proximal segment of the left umbilical vein diminishes in size, and loses its independent character by incorporation in the hepatic circulation. Only its terminal portion, emptying into the sinus venosus, is preserved. This is surrounded by the growing masses of hepatic cylinders and is converted into a vena revehens.
The connection of the right umbilical vein with the liver vessels is at first symmetrical to that on the left side, but less strongly developed. The effect of this connection is to reduce in the same way the proximal segment of the right umbilical vein and to convert its termination into a vena revehens. With the great development of the left vein, however, the vein on the right side gradually diminishes and finally loses its connection with the intrahepatic circulation altogether. The right umbilical vein is now reduced to a vessel of the ventral abdominal wall, which carries blood in the reverse of the original direction, i. e., from the abdominal wall caudad into the left umbilical vein (Figs. 253 and 255).
The connection thus established between the umbilical vein and the portal circulation results in the formation of a single large (the original left) umbilical vein which, throughout the remainder of fœtal life, returns all of the placental blood (Fig. 253).
The newly developed hepatic portion of the left umbilical vein becomes, however, not only connected with the ductus venosus, but also with the right part of the upper venous ring, derived from the right omphalo-mesenteric vein (Fig. 253). This connection forms the left portal vein of the adult, and enlarges rapidly.
Fig. 254.—Corrosion preparation showing course of portal vein and tributaries in relation to duodenum. (Columbia University Museum, No. 1857.)
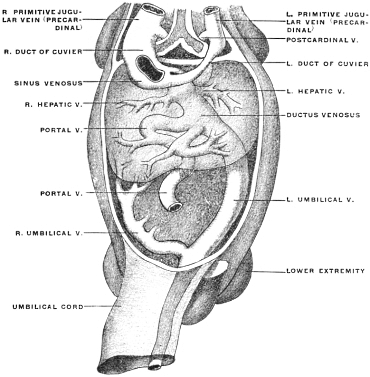
Fig. 255.—Human embryo of 10 mm. cervico-coccygeal measure. Heart and ventral body-wall removed to show sinus venosus and entering veins. (Kollmann, after His.)
The terminations of the ductus venosus and of the venæ hepaticæ revehentes undergo a number of secondary changes in relative position. The left hepatic vein loses its direct connection with the sinus venosus, and now opens into the termination of the ductus venosus, into which the right hepatic vein also empties. This common vessel (v. hepatica communis) subsequently forms the proximal segment of the postcava when this vessel develops (Fig. 256).
Fig. 256.—Final stage of development of portal and umbilical veins in the placental period.
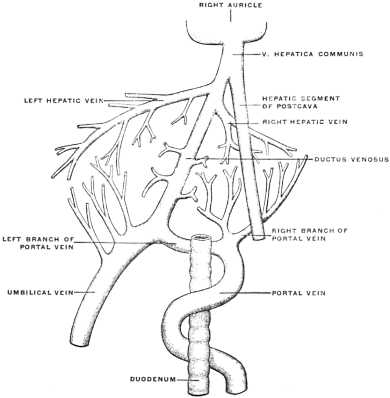
Fig. 257.—Schema of relation of postcava to hepatic veins and ductus venosus.
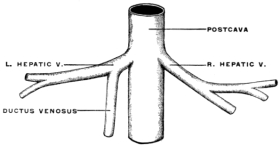
The blood, therefore, returned to the liver by the left umbilical vein divides at the transverse fissure into three streams. Two of these pass through the connection with the portal vein and through branches developed from the hepatic part of the umbilical vein into the capillary system of the right and left lobe. The third continues through the ductus venosus to the common hepatic vein and sinus venosus (Fig. 256). The ductus venosus thus becomes the chief vessel returning arterialized placental blood to the heart. When the postcava develops fully the hepatic segment of this vessel also joins the terminal part of the ductus venosus (Fig. 256) and gradually replaces the same as the main returning venous channel, the proximal part of the ductus venosus being incorporated in the vena cava (Fig. 257). The postcava then receives the right hepatic veins separately, while the left hepatic veins and ductus venosus open together into the main vein. This condition obtains up to the time of birth and the consequent interruption of the placental circulation.
While at first the ductus venosus communicates throughout its entire length with the meshwork of the hepatic capillary system, a separation into two segments, i. e., ductus venosus proper and intrahepatic segment of umbilical vein, is established after the free communication with the left umbilical vein takes place. This condition is exhibited in Fig. 258, which represents the corroded venous system of the fœtal liver, and in Fig. 259, showing an injected liver in the fœtus at term.
Fig. 258.—Corrosion preparation of venous system of human liver in fœtus at term. (Columbia University Museum, No. 1834.)
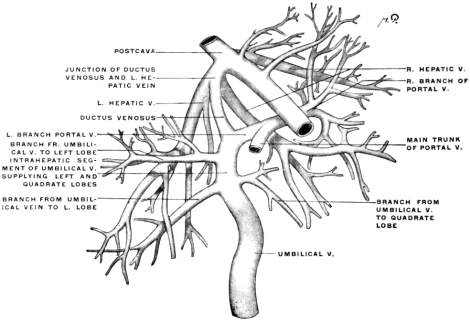
Fig. 259.—Injected and hardened human liver from fœtus at term. (Columbia University Museum, No. 1853.)
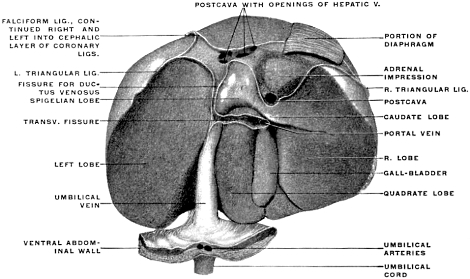
Fig. 260.—Diagram of intrahepatic fœtal venous circulation.
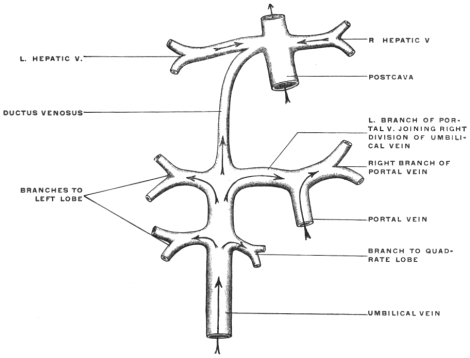
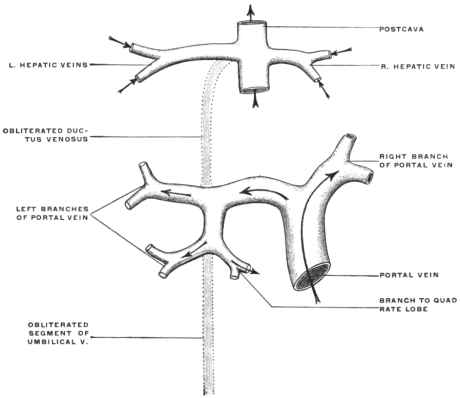
Fig. 261.—Diagram illustrating the changes in the intrahepatic venous circulation resulting from the cessation of the placental circulation at birth.
It will be observed that the umbilical vein on entering the liver gives off a large branch to the left lobe, and a smaller branch on the right side to the quadrate lobe, which act as the main venæ advehentes of these portions of the liver. Arrived at the transverse fissure the umbilical vein divides into three branches, at right angles to each other. The left branch enters the left lobe, the right branch becomes directly continuous with the left main division of the portal vein, while the central branch, continuing the direction of the umbilical vein, passes dorsad, as the ductus venosus proper, to join the left hepatic vein close to its entrance into the postcava.
5. Changes Consequent upon the Establishment of Pulmonary Respiration.—After birth the umbilical vein and its continuation, the ductus venosus, become obliterated, the former constituting the round ligament of the liver, the latter the ligament of the ductus venosus, both structures imbedded in corresponding portions of the sagittal fissure on the caudal and dorsal surfaces of the adult liver (Figs. 284 and 286). The lateral branches of the umbilical vein, however, in its course from the ventral margin of the liver to the transverse fissure (Fig. 258), remain pervious and are transferred to the portal circulation.
It will be noticed, in reference to the direction of the blood current, that at birth a sudden reversal takes place in the right terminal branch of the umbilical vein at the transverse fissure (Figs. 260 and 261). Before birth the blood current of the umbilical vein divides into three streams, right, left and central. The latter enters the ductus venosus. The left enters the liver directly, the right traverses, from left to right, the segment between the termination of the umbilical and the bifurcation of the portal vein. This segment in the adult carries blood from right to left, as left branch of the portal vein. In the fœtus, however, the blood traverses this segment from left to right, in passing from the umbilical to the right branch of the portal vein. The blood entering the liver through the portal vein passes chiefly into the right division of that vessel (Fig. 260).
After birth all the venous blood entering the liver passes through the portal vein. In the right division the direction of the current is the same as in the fœtus.
On the left side, however, the current is now from right to left, from the bifurcation of the portal into the channels of the left lobe formerly connected with the umbilical vein (Fig. 261).
Hence the direction of the current in this segment is reversed at birth.
SUMMARY OF HEPATIC CIRCULATION.
The foregoing consideration of the development shows us that the hepatic circulation presents successively three main stages:
1. Omphalo-mesenteric or Vitelline Stage, which results in the laying down of the primary capillary circulation of the liver and in the establishment of its connection with the developing veins of the alimentary tract (primitive portal channels).
2. Umbilical or Placental Stage, in which the greater part of the blood circulating through the liver is oxygenated blood returned from the placenta by the umbilical vein, accounting for the rapid growth and relatively large size of the organ during fœtal life.
The placental blood uses the preformed capillary channels of the vitelline or primitive portal system in the liver, and the same rapidly extend and enlarge with the accelerated growth of the gland. During this stage venous blood is also returned from the alimentary tract to the liver by the portal vein, produced by fusion of the distal segments of the primitive vitelline veins and their secondary connection with the mesenteric, splenic and pancreatic veins (omphalo-mesenteric development of primitive vitelline veins).
3. Adult or Portal Stage.—With the interruption of the placental circulation the portal vein assumes again its original position as the only vein carrying blood to the liver. With the establishment of intestinal digestion and absorption this vessel grows rapidly in size.
COMPARATIVE ANATOMY OF THE HEPATIC VENOUS CIRCULATION.
For the purpose of fixing the main facts in connection with the development of the higher mammalian hepatic circulation, and in order to obtain a demonstration of the cycle through which the different veins pass, the student is recommended to examine, preferably by personal dissection, a limited series of lower vertebrates which can be readily procured and easily injected. The following series has been selected, but it will be understood that other forms can be substituted, according to the local conditions which govern the supply of the material.
1. Fish. A Selachian, the common skate (Raja ocellata) or dog-fish (Acanthias vulgaris).
2. Amphibian. (a) Urodele. Necturus maculatus. (b) Anura. The common frog.
3. Reptile. Preferably, on account of the ease of injection, one of the larger lizards, as Iguana tuberculata. The turtles, although somewhat more difficult objects to prepare, can be substituted.
4. Bird. The common fowl.
5. Human fœtus at term.
1. Fish.—The venous system can be injected by tying a canula in the lateral vein, and injecting both cephalad and caudad, or by injecting cephalad through the caudal vein. The injection of the systemic veins can also be made caudad through one of the ducts of Cuvier, combined with an injection cephalad of the caudal vein.
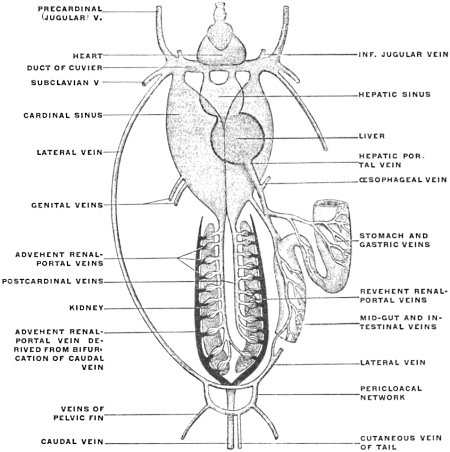
Fig. 262.
—Diagram of the veins of a selachian. (Wiedersheim, after Parker.)
The lateral vein arises from a venous network surrounding the cloaca, receiving one or more cutaneous veins of the tail, veins of the body-wall, and veins of the pelvic fins.
The caudal vein divides at the posterior end of the kidney into the two renal-portal veins, from which the advehent veins of the renal-portal system are derived. The revehent renal-portal veins join to form the posterior cardinal veins, which, after dilating enormously to form the cardinal sinuses, join with the anterior jugular, subclavian, and lateral veins to form the ducts of Cuvier. The latter receive the inferior jugular veins, from the deep parts of the head and neck and the terminations of the hepatic portal system (hepatic sinus).
The hepatic portal vein is formed by the veins of the œsophagus, stomach, and intestines. After traversing the capillary vessels of the liver, the revehent hepatic veins unite to form an extensive hepatic sinus before entering the heart.
The following main facts are to be noted in the venous system of the Selachian (Fig. 262):
1. There are Two Portal Systems. (a) Renal Portal System.—The caudal vein divides near the vent into two branches which course along the lateral border of the kidneys, sending afferent or advehent veins into the organ. The blood traverses the renal capillaries and is gathered together by the efferent or revehent veins, which empty into median paired vessels, the posterior cardinals.
(b) Hepatic Portal System.—The veins of the digestive tract and appendages unite to form a hepatic portal vein. The blood after traversing the capillary system of the liver is collected by hepatic veins, which form a dilated hepatic sinus emptying into the sinus venosus of the heart.
2. The middle segment of the intestine, presenting a spiral valve in the interior, gives rise to a vein emptying into the portal vein which corresponds to the subintestinal vitelline vein of the mammalian embryo (Fig. 202).
3. The posterior cardinal veins, also greatly dilated and forming the posterior cardinal sinus, join, near the heart, the veins returning blood from the head, the anterior cardinal or jugular, to form a transversely directed trunk, the duct of Cuvier, which empties into the sinus venosus at the auricular extremity of the heart. Into the duct of Cuvier empties on each side a lateral vein returning the blood from the body walls. This vein can be considered, for our present purpose, as representing in general the abdominal vein of amphibians and reptiles, and the umbilical vein of the mammalian embryo.
The adult selachian venous system is therefore to be considered as illustrating the following conditions above encountered in our study of the embryology of the mammalian venous system.
1. The heart illustrates excellently the stage in the mammalian development, in which auricular and ventricular segments have differentiated, but before the division of the cavities into a pulmonary and systemic portion by the development of the auricular and ventricular septa and the division of the arterial trunk into pulmonary artery and aorta.
The sinus venosus still exists, as an ante-chamber to the auricular cavity proper, receiving on each side the ducts of Cuvier, which represent the fusion product of the systemic veins, anterior and posterior cardinal.
2. The hepatic portal circulation corresponds to the mammalian stage in which the vitelline veins have become omphalo-mesenteric by joining the intestinal veins.
The spiral vein remains as a portion of the original vitelline vein corresponding to the subintestinal segment of the mammalian embryo (cf. Figs. 248 and 249).
The selachian portal vein represents the united vitelline veins, into which the veins of the digestive tract open.
In the liver we find a simple system of venæ advehentes, derived from the branching of the portal vein, a hepatic capillary network, and venæ revehentes, the proximal remnants of the original vitelline veins which carry the liver blood to the sinus venosus. The condition of the hepatic circulation corresponds therefore to the stage shown in Fig. 250 of the mammalian development. There is as yet no association of the hepatic venous system with the representative of the umbilical vein (the lateral vein of the selachian).
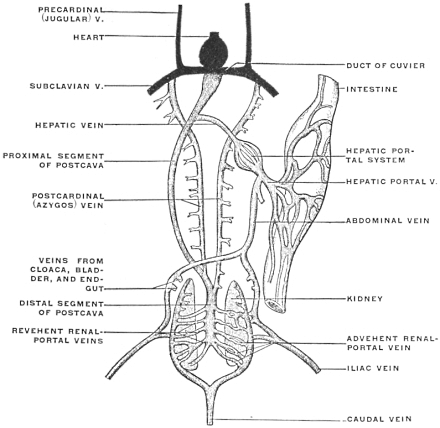
Fig. 263.
—Diagram of the veins of urodele amphibian (
Salamandra maculosa
). (Wiedersheim.)
The caudal vein bifurcates at the posterior extremity of the kidneys to form the afferent trunks of the renal-portal system along the lateral border of the kidneys, from which the advehent veins of the renal-portal system are derived. The iliac or femoral vein divides into an anterior and a posterior branch, the latter opening into the afferent renal-portal vein, while the former, uniting with the one of the opposite side, forms the abdominal vein, and receives vessels from the bladder, cloaca, and end-gut. The revehent veins of the renal-portal system, emerging upon the ventral surface of the kidneys, empty into a single median vessel, the distal or renal section of the postcava or vena cava inferior. Proceeding cephalad, the proximal or hepatic section of this vessel, after traversing the liver and receiving the revehent hepatic veins of the hepatic portal system, empties into the sinus venosus of the heart. Previous to entering the liver the postcava gives off the two posterior cardinal or azygos veins, which continue cephalad, receiving tributary segmental veins from the body-walls and reach the sinus venosus by joining the subclavian veins. These latter uniting with the anterior cardinal (jugular) veins form the ducts of Cuvier (precaval veins).
The abdominal vein continues cephalad in the ventral mesogastrium to the liver, giving off a number of smaller branches, which enter the hepatic portal circulation by penetrating the ventral surface of the liver between the layers of the ventral mesogastrium, while the main continuation of the vessel joins the hepatic portal vein at its point of entrance into the liver.
The hepatic portal vein is formed by tributaries returning the blood from the digestive tract (intestinal canal, spleen, pancreas). The blood, after traversing the hepatic portal circulation, is conducted by the hepatic revehent veins to the proximal section of the postcava. A number of secondary or accessory portal veins pass from the anterior portion of the intestinal canal (œsophagus, stomach) directly to the liver.
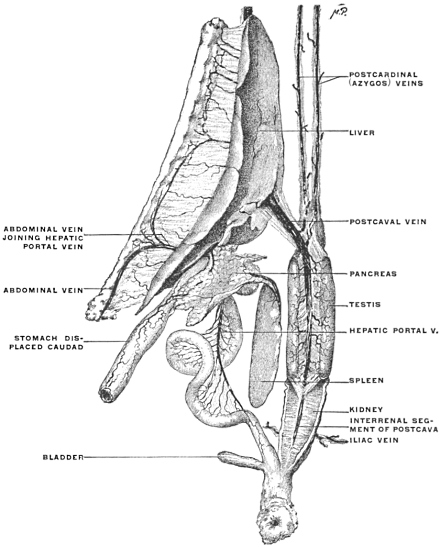
Fig. 264.
—Dissection of veins of
Necturus maculatus
, mud-puppy. (Columbia University Museum, No. 1835.)
The postcava has been divided at the cephalic end of the liver just before entering the sinus venosus, and the postcardinals have been cut prior to their junction with the subclavian veins.
The stomach has been turned caudad. The abdominal vein has been divided after the common trunk has been formed by branches from the iliac veins. The latter are seen entering the afferent renal-portal vein, derived from the bifurcation of the caudal vein, along the lateral border of the kidneys.
The junction of the main trunk of the abdominal vein with the hepatic portal vein takes place close to the liver under cover of the pancreas. A series of accessory portal veins continuous with the abdominal vein enter the ventral surface of the liver between the layers of the ventral mesogastrium. The inter-renal segment of the postcava receives the revehent renal-portal veins. The iliac vein enters the advehent renal-portal veins derived from the caudal vein.
Fig. 265.—Venous system of Rana esculenta, frog. (Ecker.)
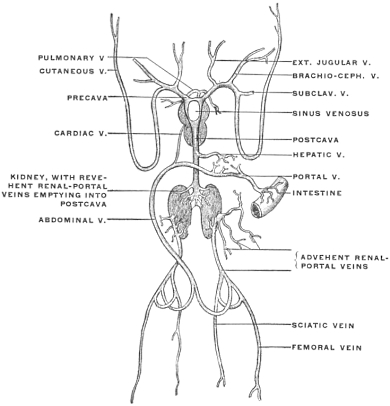
3. The lateral veins, which we can, as stated, regard for purposes of illustration, without prejudging their genetic significance, as representing the mammalian embryonic umbilical veins, still present the condition corresponding to the early mammalian embryonal stage shown in Fig. 250. They are veins of the body walls, emptying cephalad of the liver, directly into the ducts of Cuvier, and through them into the sinus venosus of the heart.
Fig. 262 shows the arrangement of the venous system in a typical selachian diagrammatically.
2. Amphibian. (a) Urodele.—The following points are to be noted in comparison with the preceding form:
1. The two ducts of Cuvier entering into the sinus venosus are formed by the anterior cardinal and subclavian veins, which latter, having appeared with the full development of an anterior extremity, receives the posterior cardinal veins, representing the mammalian azygos system.
2. The renal portal circulation persists. The caudal vein is, however, no longer the only afferent vein of this system. With the full development of a posterior extremity an iliac vein returns the blood from the same and gives a large branch (afferent to the portal renal system), while the trunk continues cephalad as an anterior abdominal vein, corresponding to the lateral selachian vein, emptying in the hepatic portal vein.
3. The efferent veins of the renal portal system no longer unite to form the posterior cardinal, as in the Selachian, but empty into a new median vessel, the inferior vena cava, or postcava, which has replaced the distal segments of the posterior cardinal veins.
The postcava now carries the blood from the kidneys directly to the heart. The original posterior cardinal veins still persist in their proximal segments, as smaller trunks connecting the distal part of the postcava with the ducts of Cuvier through the subclavian veins. The ducts of Cuvier represent the precavæ (venæ cavæ superiores) of mammalia and the postcardinals the mammalian azygos veins.
4. The hepatic portal system differs in two respects from the Selachian type.
(a) The blood returned to the liver from the digestive tract by the portal vein becomes mixed before entering the gland with the blood returned from the posterior extremities and abdominal walls by the abdominal vein.
This vein, paired below and continuous with the lateral of the two branches into which the iliac vein divides, becomes united into a single trunk above and empties into the portal vein.
The abdominal vein represents the lateral vein of the Selachian and corresponds to the umbilical vein of the higher vertebrates.
(b) The venæ hepaticæ revehentes do not empty directly into the sinus venosus, but into the proximal portion of the postcava.
Hence the adult urodele venous system illustrates, in reference to the mammalian development, these stages:
1. The umbilical (abdominal) vein has lost its direct connection with the sinus venosus. The proximal segment, cephalad of the liver, has disappeared, and its blood now passes directly into the hepatic circulation by its union with the portal vein.
(Cf. stage schema Figs. 251 and 252.)
2. The postcaval vein has made its appearance, largely replacing the posterior cardinal veins, whose proximal segments became converted into secondary vessels (azygos) uniting the system of the postcava with that of the duct of Cuvier (mammalian præcava), while their distal segments are transformed into the distal portion of the postcava.
The postcava, therefore, is made up of two districts:
(a) The proximal portion is a new vessel, developed in connection with the hepatic venous system.
(b) The distal portion is derived from the distal segments of the original posterior cardinal veins.
The termination of the hepatic veins in the postcava corresponds to the stage shown in schema Fig. 256.
Fig. 263 gives a schematic representation of the arrangement of the venous system in a typical urodele amphibian (Salamandra maculosa).
In Fig. 264 the dissected venous system of Necturus maculatus, the mud puppy, is shown in an injected preparation.
(b) Anure.—The venous system of Rana esculenta is shown in Fig. 265. Comparison with venous system of urodele:
1. The abdominal vein, corresponding to the mammalian umbilical vein, has assumed a greater importance in reference to the hepatic circulation. It is a large trunk, continuous below with the pelvic vein, terminating above in two branches, which enter the liver as afferent veins, being joined just prior to the division by the hepatic portal vein.
2. A small cardiac vein, coming from the heart, empties into the angle of bifurcation of the abdominal vein.
3. The postcava is well developed, formed by large efferent renal veins. It entirely replaces the posterior cardinal veins which are absent in the adult animal.
4. A right and left præcaval vein is formed by the union of two jugular trunks with the vein of the anterior extremity and a large musculo-cutaneous vein.
Comparison with the mammalian development: the venous system of this amphibian can be used to illustrate the mammalian embryonal stage shown in schema Fig. 252, in which the abdominal or umbilical vein has become the most important vessel in the afferent hepatic venous system.
The communication existing by means of the cardiac vein between the heart and the hepatic afferent system may suggest, but purely for illustrative purposes, the direct connection of the umbilical vein with the heart by the ductus venosus in the mammalian embryo (cf. schema Figs. 250-256).
3. Reptile.—In Iguana the renal portal system is well developed. The caudal vein, returning the blood from the tail and the cavernous tissue of the genital organs, continues for a short distance upon the fused caudal end of the two kidneys (Fig. 269) and then divides into two afferent renal veins which ascend on the ventral surface of the glands, giving branches to the renal capillary system. About the middle of the kidney each afferent vein is joined by a large transverse branch from the abdominal vein (Fig. 266).
Fig. 266.—Systemic veins of Iguana tuberculata. The alimentary canal and appendages, together with the hepatic portal vein and the intrahepatic segment of the postcava, have been removed. The liver occupies the space between the divided ends of the postcava. The vertebral vein represents the rudimentary proximal segment of the postcardinal vein corresponding to the mammalian azygos vein. (Columbia University Museum, No. 1320.) Fig. 267.—Veins of Iguana tuberculata. Connection of systemic veins with sinus venosus of heart. The rudimentary system of the vertebral (azygos) veins and their proximal connection with the subclavian vein are shown. (Columbia University Museum, No. 1859.)
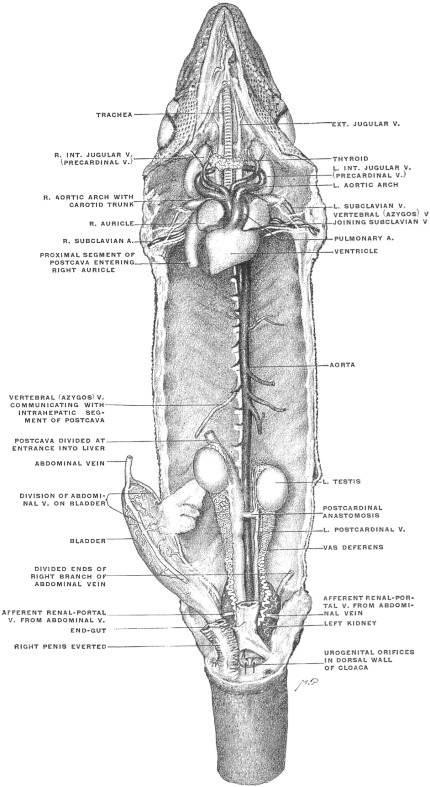
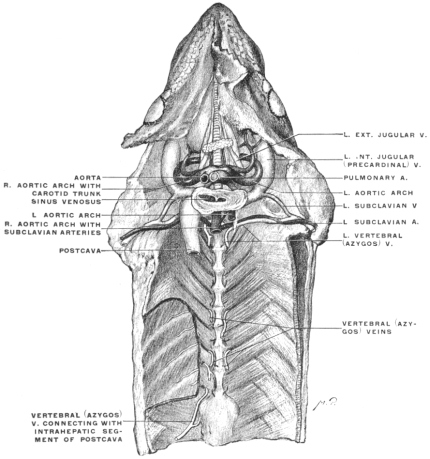
Fig. 268.—Corrosion preparation of venous system of liver in Iguana tuberculata. The hepatic portal system and its connection with the abdominal vein, as well as the relation to the postcava, are shown. The preparation supplements Fig. 266, showing the parts which have been removed in the latter. (Columbia University Museum, No. 1860.)
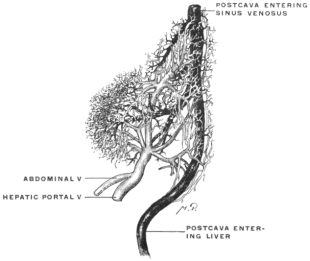
Fig. 269.—Iguana tuberculata, ♂. Genito-urinary tract, dorsal view, with renal-portal, postcardinal, and postcaval veins. (Columbia University Museum, No. 1862.)
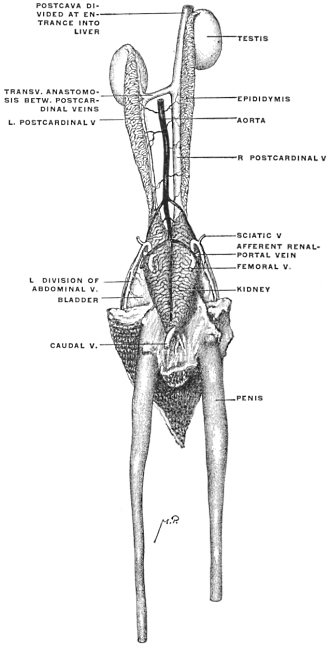
The renal efferent system begins by a number of inter-renal anastomoses which unite along the mesal border of the right kidney into a large ascending trunk, while the corresponding vessel of the left side, starting from the same anastomosis, is considerably smaller (Figs. 266 and 269). Each of these vessels also receives blood from the testis, epididymis, vas deferens and adrenal body in the male, and from the ovary and oviduct in the female. They represent, in fact, the distal functional part of the right and left embryonic postcardinal vein. Just caudad of the left testis the vein of the left side crosses obliquely ventrad of the aorta and joins the right vessel to form the trunk of the postcava, which enters, immediately beyond the cephalic pole of the right testis, the prolonged caval lobe of the liver (Figs. 266 and 269). Ascending in the substance of this gland and receiving the afferent hepatic veins (Fig. 268), the vena cava emerges from the cephalic surface of the liver greatly enlarged and proceeds to the right auricle.
The abdominal vein divides below into two branches which pass caudad on each side of the bladder, receiving tributaries from the same, to the lateral border of the kidneys (Figs. 266 and 269). Here the vessel is connected by the transverse branch above described with the afferent renal portal system derived from the caudal vein. At the same point it receives the sciatic vein, the principal venous vessel of the posterior extremity. Above, the main abdominal vein, resulting from the union of the two branches referred to, ascends on the dorsal surface of the ventral abdominal wall, receiving a few twigs from the ventral mesogastrium within whose free caudal edge the vessel runs. Just before reaching the liver the abdominal vein turns dorsad on the caudal surface of the gland and joins the hepatic portal vein (Figs. 268 and 275). Several accessory veins, two or three in number, belonging to the system of the abdominal vein, pass above this point from the ventral body wall between the layers of the ventral mesogastrium, to enter the liver separately on its convex ventral surface, above the fusion of the main abdominal vein with the portal vein. These additional branches on entering the liver join the portal system, forming a set of ventral accessory portal veins.
The hepatic portal vein derives its principal tributaries from the splenic, gastric, pancreatic and intestinal veins. One or two additional branches (accessory vertebral portal veins), as above stated, connect the system of the segmental and vertebral veins with the portal circulation, entering the liver separately. In like manner one or two gastric veins (accessory gastric portal veins) enter the dorsal aspect of the liver separately, passing from the stomach to the gland between the layers of the gastro-hepatic omentum (Fig. 275).
Compared with the development of the mammalian type, the venous system of Iguana serves to illustrate the stage in the history of the umbilical vein (represented by the abdominal vein of the reptile) in which the connection of the vessel with the portal vein has been formed and transmits the greater part of the blood returned by the umbilical vein to the liver, while the proximal segment above this point, originally continued into the sinus venosus, has begun to disappear, being, however, still represented by the vessels which, as accessory ventral portal veins, pass in the ventral mesogastrium, from the body wall to the liver.
It will be noted that all the hepatic portal blood, whether conducted by the main portal and abdominal vein, or by the accessory portal branches, traverses the capillary circulation of the liver before entering the postcava.
The vertebral and segmental venous system, representing the azygos veins of the mammalia, is very rudimentary (Figs. 266 and 267). The distal portions of the postcardinal veins form the efferent renal branches and the ascending trunks of the postcava.
The next segment of the vertebral veins appears as a trunk on the right side which enters the portal circulation. A second vein higher up is connected with both the gastric portal system and with the longitudinal chain of the vertebral veins. Finally a proximal venous branch on each side of the vertebral column, representing the upper portion of the postcardinal veins, receives the proximal segmental veins and empties into the subclavian vein (Fig. 267).
Fig. 270.—Veins of pigeon, Columba livia. (Modified from Parker and Haswell.) The renal-portal vein of the right side is supposed to be dissected to show its passage through the right kidney.
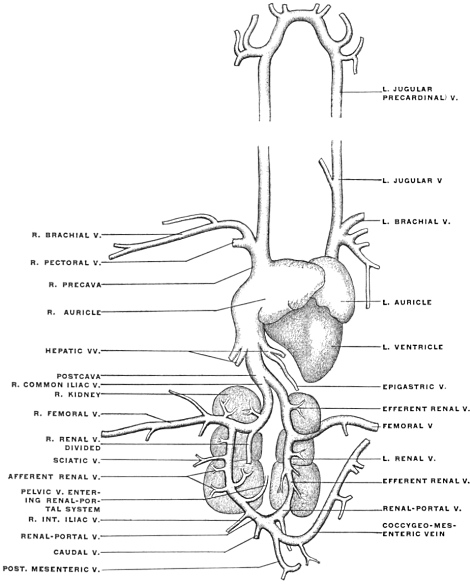
4. Bird.—The characteristic change in the venous system of the bird, as compared with that of the amphibian and reptile, is found in the nearly complete abolition of the renal portal system. The caudal vein bifurcates, sending on each side a large trunk, which receives the pelvic (int. iliac) veins, to the kidney (renal afferent portal vein), but only a few small branches enter the substance of the gland (Fig. 270, afferent renal V). The main vessel continues cephalad through the kidney and, after receiving the vein from the posterior extremity (femoral), unites as common iliac vein with the vessel of the opposite side to form the postcava. This vessel traverses the liver, receiving the hepatic afferent veins of the portal system. The portal vein is formed by tributaries from the intestinal canal, pancreas and spleen, and is also joined by a large coccygeo-mesenteric vein, which is given off at the point of bifurcation of the caudal vein and receives tributaries from the lower part of the alimentary canal. The abdominal vein of amphibians and reptiles is represented probably by the epigastric vein, which returns the blood from the omental mass of fat to the hepatic veins.
Compared with the mammal on the one hand, and with the lower types on the other, the venous circulation of the bird illustrates the following points:
1. Extensive reduction of the renal portal system and direct formation of postcava by the iliac veins, foreshadowing the condition found in the mammal.
2. Complete separation of the portal and systemic venous circulation in the adult. Disappearance of the ventral abdominal vein as a vessel of the body wall.
5. Human Fœtus at Term.—The student is recommended to examine, by dissection and injection, the venous system of a fœtus at term, noting the following facts:
Fig. 271.—Human fœtus at term. Corrosion preparation of heart and vascular system. (Columbia University Museum, No. 1858.)
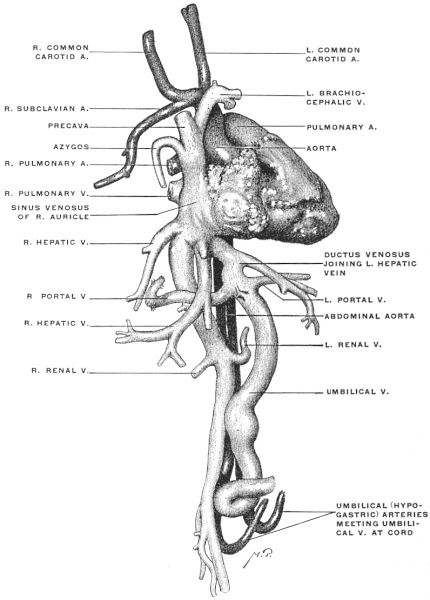
1. Course of umbilical vein in ventral abdominal wall and along free edge of falciform ligament to liver (Fig. 241), corresponding to the position of the amphibian and reptilian abdominal vein (Figs. 264 and 275).
2. Connection of umbilical vein in liver: (a) With portal system (Figs. 258 and 271). (α) With portal vein. (β) With portal system of left and quadrate lobes by branches derived directly from umbilical vein while situated in the umbilical fissure (Fig. 258). (b) With hepatic veins and postcava by the ductus venosus (Figs. 258 and 271).
3. Connection of the postcaval and precaval systems by the azygos veins representing the proximal segments of the embryonic postcardinal veins (Fig. 272).
Fig. 272.—Human fœtus at term. Postcava and azygos veins. (Columbia University Museum, No. 1861.)
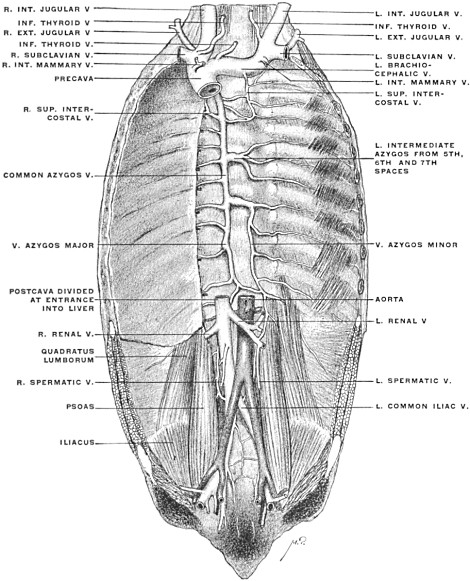
If possible the dissection of an injected fœtus should be combined with the examination of corrosion preparation of the fœtal circulation and especially of the venous system of the fœtal liver (Figs. 258 and 271).
3. The remnants of fœtal structures in the adult liver (round ligament and ligament of the ductus venosus) should be compared with the structures from which they are derived in the fœtus at term (umbilical vein and ductus venosus).
II. THE VENTRAL MESOGASTRIUM.
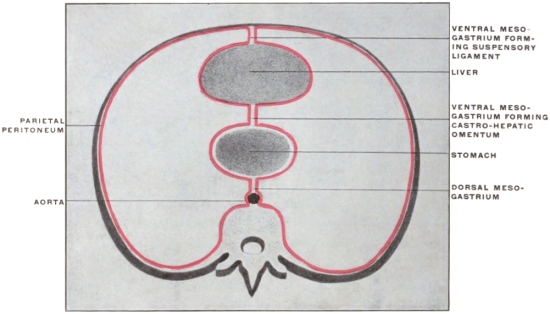
This membrane has been heretofore mentioned on several occasions. It now remains for us to carefully consider its arrangement in detail, both as regards the peritoneal relations of the liver and in reference to its influence on the abdominal space as a whole. We can best accomplish this purpose by considering the membrane in the first place in a purely schematic manner. In contradistinction to the primitive common dorsal mesentery, which extends the entire length of the alimentary tube, the ventral mesentery, or properly the ventral mesogastrium, is confined to the stomach and proximal portion of the duodenum. We can represent the membrane as extending between the ventral abdominal wall and the ventral border (later the lesser curvature) of the stomach and of the hepatic angle of the duodenum. Cephalad it is connected with the embryonic septum transversum (future diaphragm). Caudad its two layers pass into each other in a free concave edge, including between them the umbilical vein (free edge of falciform ligament of adult). Consequently a schematic profile or lateral view of the membrane and its attachments in the earlier stages would appear as represented in Fig. 273, while the arrangement in transection would be as shown in Fig. 274. It will be observed that the separation of the cephalic portion of the abdominal cavity into symmetrical right and left halves, previously indicated in discussing the primitive stomach and the dorsal mesogastrium, is actually completed by the ventral mesogastrium. This complete separation of the lateral halves of the cœlom cavity ceases at the point where the ventral mesogastrium terminates in the free concave edge carrying the umbilical vein. Hence caudad of this falciform edge the two halves of the cavity communicate freely with each other ventrad of the intestine and dorsal mesentery.
Fig. 273.—Schematic profile view of ventral mesogastrium with developing liver.
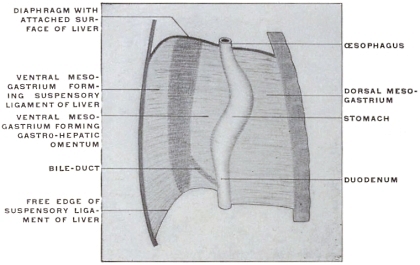
Fig. 274.—Schematic transection of abdomen in region of ventral mesogastrium.
This difference in the extent of the mesogastria is perhaps best understood by reference to their relation to the first portion of the duodenum. We have seen that the duodenum in the early stages is attached dorsally by a portion of the common dorsal mesentery, which, after differentiation of the intestinal tract, immediately follows the dorsal mesogastrium proper, forming the mesoduodenum (Fig. 172). The proximal portion of the duodenum (hepatic angle) is still included within the fold of the ventral mesogastrium which membrane terminates immediately beyond this point in the free edge surrounding the umbilical vein (subsequent round ligament) (Fig. 172). The remainder of the duodenum is devoid of any ventral attachment, being only connected to the dorsal body wall by the mesoduodenum (Fig. 197).
Subsequently, after the fourth month, while the right surface of the mesoduodenum and descending duodenum adhere to the parietal peritoneum, the peritoneal investment of the first portion or hepatic angle remains free. This peritoneal covering of the proximal duodenal segment is situated at the point where the caudal end of the ventral mesogastrium, after surrounding the first portion of the duodenum, becomes continuous with the dorsal mesentery forming the mesoduodenum. Obliteration of the latter membrane by adhesion to the parietal peritoneum leaves the first portion of the duodenum invested on both surfaces by the lesser omentum, derived from the ventral mesogastrium. The ventral surface of the gut is covered by the ventral layer, the dorsal surface by the dorsal layer of the lesser omentum. These two layers become continuous around the right free edge of the lesser omentum (hepato-duodenal ligament) forming the ventral boundary of the foramen of Winslow (cf. infra, p. 177).
Returning to the schematic consideration of the ventral mesogastrium above outlined (Figs. 273 and 274) we have to note the first important change in the arrangement depending upon the development of the liver. This organ, growing, as we have seen, from the duodenum, extends between the two layers of the ventral mesogastrium, receiving a serous investment from the same. At an early period the liver, developing thus between the mesogastric layers, reaches the septum transversum and becomes closely connected with it, laying the foundation for the subsequent extensive attachment of the gland to the diaphragm.
Extending caudad the liver grows beyond the caudal free edge of the ventral mesogastrium on each side, carrying the serosa with it. Consequently the ventral margin of the liver becomes indented at this point; the umbilical vein and subsequently its fibrous remnant, the round ligament, are imbedded in a notch and fissure (umbilical notch and fissure) continued from the ventral margin dorsad along the caudal surface of the liver (Fig. 259).
This growth of the liver has now effected a division of the primitive ventral mesogastrium into two segments:
1. Ventral portion, between diaphragm and liver, forms the broad falciform or suspensory ligament of the liver.
2. The dorsal portion, between liver and stomach, forms the lesser or gastro-hepatic omentum.
The caudal free edge of the ventral mesogastrium extends between the umbilicus and the caudal surface of the liver, carrying the umbilical vein between its layers. The growth of the liver serves to bury this free edge and the contained vein in a fissure on the caudal surface of the liver. The same obtains in the case of the ductus venosus continued from the umbilical vein (umbilical fissure and fissure of ductus venosus of adult liver). Consequently the original continuity of the broad ligament and lesser omentum, as parts of the primitive ventral mesogastrium, is not readily seen in the adult.
The broad ligament extends across the convex cephalic surface of the liver uniting it to the ventral abdominal wall and diaphragm, while its free falciform edge apparently stops at the umbilical notch in the ventral border of the organ. Actually, however, the obliterated vein is surrounded in the bottom of the fissure, by a peritoneal fold which effects the junction between broad ligament and lesser omentum.
We will see later in what way the permanent adult arrangement of the lesser omentum is brought about. For the present we can state, on the hand of the schematic Fig. 273, that the free caudal edge of the falciform ligament containing the umbilical vein, and the free edge of the gastro-hepatic omentum form together originally the caudal free edge of the ventral mesogastrium, which membrane becomes separated, by the growth of the liver, into suspensory or broad ligament and lesser or gastro-hepatic omentum.
Fig. 275.—Abdominal viscera of Iguana tuberculata. (Columbia University Museum, No. 1313.)
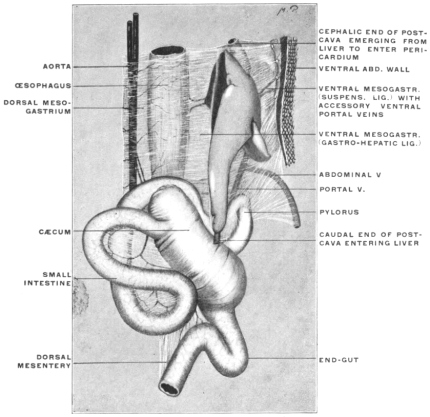
This primitive disposition of the ventral mesogastrium and the viscera connected with the same, is well shown in some of the lower vertebrates in whom the development never proceeds beyond the early mammalian stages. Fig. 275 shows in profile view from the right side the situs viscerum and peritoneum in Iguana tuberculata.5 The two dorsal aortic roots are seen to unite to form the main aorta, which descends between the layers of the dorsal mesentery, sending branches to the dorsal margin of œsophagus and stomach. From the opposite border of the stomach the ventral mesogastrium is derived. Its dorsal segment (gastro-hepatic omentum) connects liver and stomach, carrying between its layers the portal vessels, hepatic artery and biliary duct. The ventral segment of the membrane, forming the suspensory or broad ligament, extends between abdominal wall and ventral surface of the liver. Caudad, the lesser omentum and the suspensory ligament are seen to have a common concave falciform edge.
The ventral abdominal vein ascends between the layers of the suspensory ligament and near the liver becomes connected by a large branch with the portal vein. A few smaller branches are seen passing from the abdominal wall beyond this point. In this reptile, therefore, the permanent vascular arrangement corresponds to an early human embryonic stage.
The reptilian ventral abdominal vein is the homologue of the umbilical vein of the placentalia. The large branch passing to the portal vein represents the connection established in the human embryo between the umbilical and portal veins. The small branches, continuing cephalad between the mesogastric layers, represent the temporary proximal remnants which in the human embryo the umbilical veins form in connection with abdominal walls. The permanent adult arrangement of this part of the vascular system in this animal corresponds therefore to one of the stages of development in the human embryo, as previously indicated (cf. p. 149; Figs. 251 and 252).
PERITONEAL RELATIONS OF LIVER.
It is well to begin the study of the peritoneal connections of the liver with the consideration of the embryonic stage shown in Fig. 273 schematically.
Fig. 276.—Schematic view of embryonic liver detached from its connections, seen from behind, with lines of peritoneal reflection.
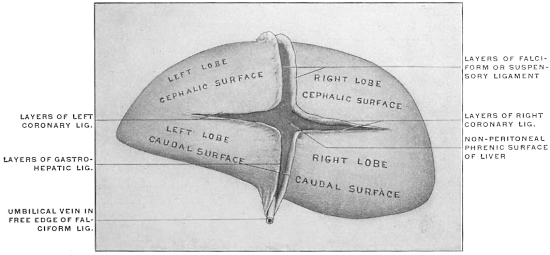
If we imagine this embryonic liver detached from its connections in such a manner as to leave the divided peritoneal layers of the ventral mesogastrium as long as possible, and if we regard the preparation from behind, the appearance of the parts could be represented in Fig. 276.6
It will of course be seen that the area of direct adhesion to the diaphragm, extending transversely, would separate the lesser omentum from the suspensory ligament.
As is seen in the transection (Fig. 274), the right and left layers of the suspensory ligament, at its attachment to the liver, turn into the visceral peritoneum investing the organ on its ventral and cephalic surfaces. Continuing around the borders of the liver this visceral peritoneum then invests in like manner the dorsal or caudal surface directed toward the stomach, until, at the region of the future portal or transverse fissure, this visceral peritoneum becomes in turn continuous with the two layers of the lesser or gastro-hepatic omentum. Consequently in the embryonic detached liver the lines of peritoneal reflection would be nearly cruciform, the vertical limb of the cross being formed on the cephalic surface by the two layers of the suspensory ligament, while on the caudal surface it is formed by the layers of the lesser omentum. The horizontal arm of the cross is formed by the upper and lower limits of the area of diaphragmatic attachment, along which the parietal diaphragmatic peritoneum turns into the visceral hepatic investment (forming the two layers of the primitive coronary ligament). In the liver shown thus schematically from behind we would overlook the dorsal and adjoining portions of the cephalic and caudal surfaces of the adult human liver.
The primitive biliary duct, portal vein and hepatic artery reach the liver between the layers of the lesser omentum. The venæ revehentes (hepatic veins) reach the sinus venosus at the attachment of the liver to the septum transversum (primitive diaphragm).
The first important change, resulting in a rearrangement of these peritoneal layers, is produced by the connection of the umbilical with the rudimentary portal vein.
Fig. 277.—Schematic view of embryonic liver, showing influence of vascular connections on the arrangement of the lines of peritoneal reflection.
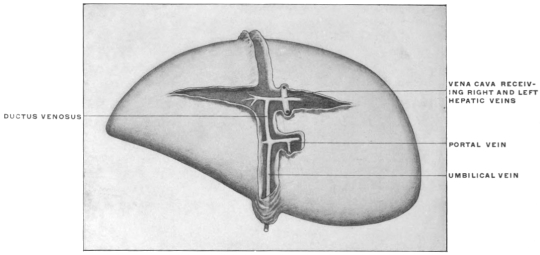
Fig. 278.—Later stages, showing development of transverse fissure, Spigelian and caudate lobes.
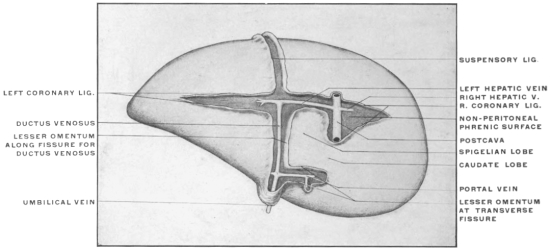
This junction occupies a relatively wide area on the caudal surface of the liver, and the layers of the lesser omentum are separated somewhat at this point to accommodate the enlarging vascular structures between them. More especially is this the case with the right leaf of the primitive gastro-hepatic omentum. A species of lateral diverticulum is formed by this leaf so as to include the umbilical vein at its junction with the portal. The membrane in the region of this diverticulum turns its surfaces dorsad and ventrad, and its free edge toward the right (Fig. 277). With the gradual increase in the size of the vessels, and with the transverse position which the rotation of the stomach imparts to the opposite border of the lesser omentum attached to the lesser curvature, this transversely disposed portion gradually exceeds in length and size the part of the original omentum enclosing the umbilical vein. This vessel and the investing peritoneum become lodged in a sagittal depression on the caudal surface of the liver (rudimentary umbilical fissure), while the transverse portion, developed as indicated, surrounds the structures connected with the liver at the future transverse or portal fissure.
Schematically this rearrangement of the hepatic peritoneal lines of reflection can be shown in Fig. 278.
It will be observed that in this way a small part of the caudal surface of the right lobe has become partially marked off from the remainder as a rudimentary Spigelian lobe, bounded ventrally by the transverse fissure and lesser omentum attached to the same; to the left by the two layers of the lesser omentum containing the ductus venosus; while the limit cephalad is afforded by the reflection of peritoneum from liver to diaphragm, forming part of caudal layer of right coronary ligament. To the right this rudimentary Spigelian surface is directly continuous with the rest of the dorsal and caudal surface of the right lobe (Fig. 277). Finally a definite right limit is given to the Spigelian lobe by the increasing size of the postcava and its closer connection with the liver. This vessel now assumes the position of the main venous trunk entering the heart from below.
This inclusion of the vena cava in the fissure or fossa of that name on the dorsal surface of the liver affords, so to speak, the vertical measure of the non-peritoneal area of the liver attached directly to the diaphragm. As the vein develops the interval between the two layers of the right coronary ligament increases, producing the well-known large non-peritoneal area on the dorsal surface of the adult liver, which is directly attached to the diaphragm.
Immediately to the left of the vena cava, however, the original condition persists. The area of direct diaphragmatic attachment is narrow and consequently the two layers of the coronary ligament are close together at this point.7
In this way a species of recess (Spigelian recess or hepatic antrum of lesser sac) is formed. A portion of the dorsal liver surface lying just to the left of the vena cava, between it and the ductus venosus, remains invested by peritoneum which is reflected from the boundaries of this space to the diaphragm. This forms the Spigelian lobe (Fig. 278).
The lobe is bounded to the right by the postcava, to the left by the reflection of the lesser omentum to the stomach along the fissure for the ductus venosus; cephalad the boundary is formed by the reflection of the caudal layer of the coronary ligament to the diaphragm.
The caudal boundary is afforded by the transverse position which the lesser omentum has assumed in the region of the transverse or portal fissure.
It will be seen that the original continuity of the Spigelian lobe with the caudal surface of the right lobe is maintained by the narrow bridge of liver tissue connecting the caudal right angle of the rectangular Spigelian lobe with the right lobe. This narrow isthmus, situated between vena cava dorsad and the free right edge of lesser omentum ventrad, forms the so-called caudate lobe.
Fig. 279.—Liver of human fœtus at eighth month. View of caudal and dorsal surfaces. (Columbia University Museum, No. 1854.)
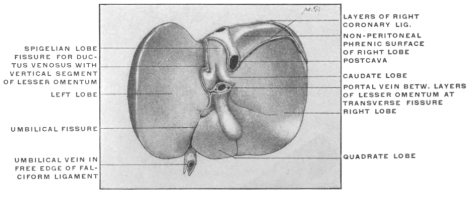
Fig. 280.—Human fœtal liver at term, showing lines of peritoneal reflection on cephalic, dorsal, and caudal surfaces. (Columbia University Museum, No. 1855.)
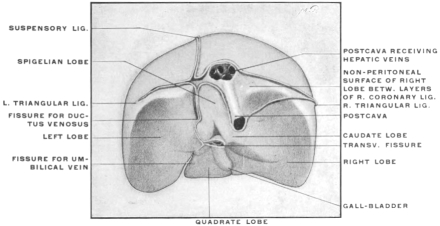
Fig. 279 shows a human fœtal liver at the end of the eighth month in the view from below and behind. The original continuity of the layers of the lesser omentum, attached along the fissure for the ductus venosus, with the fold of the falciform ligament occupying the umbilical fissure can still be made out for a short distance beyond the left extremity of the transverse fissure. The section of the lesser omentum which occupies the transverse fissure and, including the portal vein, hepatic artery and duct between its layers, terminates in the free right margin, is evidently derived by a lateral extension from the right layer of the primitive sagittal lesser omentum, whose original direction is preserved along the fissure of the ductus venosus.
In Fig. 280 the lines of peritoneal reflection on the cephalic, dorsal and caudal surfaces of a human fœtal liver at term are shown.
We can now proceed to trace the reflection of the peritoneum from the liver to adjacent structures.
Begin with the caudal layer of the coronary ligament on the extreme right, where fusion with the corresponding cephalic layer produces the right triangular ligament. The caudal layer of the coronary ligament proceeds from right to left along the caudal margin of the non-peritoneal dorsal diaphragmatic surface of right lobe, being reflected along this line from the liver to the adjacent portions of the diaphragm and ventral surface of right kidney and suprarenal capsule (hepato-renal ligament). A small cephalic part of ventral surface of right suprarenal capsule lies above this line of reflection, is hence non-peritoneal and firmly connected with the liver just to the left of entrance of vena cava into the caval fissure. Continuing, the caudal layer of the coronary ligament crosses the ventral surface of the vena cava and turns, immediately to the left of the vein, at a right angle, ascending to form the left boundary of the Spigelian recess, being reflected along this line from the left margin of the caval fissure to the pillars of the diaphragm. Arrived at the opening of the central tendon permitting passage of vena cava into pericardium, and at the level of the entrance of the left hepatic vein into the cava, the peritoneum turns again at a right angle and runs from right to left, forming the cephalic limit of the Spigelian recess. Turning caudad along the fissure for the ductus venosus, as right leaf of that portion of the lesser omentum which is attached to this fissure and has preserved its sagittal position, the peritoneal line of reflection reaches the left extremity of the portal or transverse fissure. It now turns to the right following the fissure as the dorsal layer of the transverse segment of the lesser omentum, and becomes continuous, with the formation of a free right edge, with the ventral layer of the same membrane, passing from right to left, the two layers including between them the structures entering and leaving the liver at the transverse fissure (portal vein, hepatic artery, duct). Arriving at the left extremity of the transverse fissure the ventral layer of the transverse segment of the lesser omentum—as we practically trace it in the adult as a free membrane—turns directly into the left leaf of the sagittal segment attached along the fissure for the ductus venosus, and becomes continuous along the dorsal border of the left lobe with the caudal layer of the left coronary ligament. This direct continuity, as just stated, exists practically in the adult. From the development of the membrane, however, it will be seen that the ventral layer of the transverse lesser omentum, at the left extremity of the portal fissure, becomes continuous with the right layer of the primitive mesogastrium enclosing the umbilical vein. After surrounding this vein it is continued into the left leaf of the same membrane, which in turn passes into the left layer of the portion attached along the fissure for the ductus venosus.
This original connection can at times be traced very clearly in young specimens (Fig. 279), and occasionally is also still evident in the adult liver.
Usually, however, the round ligament of the adult and its investing peritoneum is buried so deeply in the umbilical fissure, or even bridged over in part by liver tissue, that the connection is not evident. The ventral layer of the transverse omentum then appears directly continuous with the left layer of the sagittal omentum attached along the fissure for the ductus venosus.
We can sum up the facts just considered as follows:
1. The rotation of the stomach from the sagittal into the transverse position, and the development of the umbilical and portal veins, rearrange the original sagittal plane of the lesser omentum, dividing it into two districts:
(a) Cephalic portion, remaining in the original sagittal plane, follows the fissure for the ductus venosus. With the incorporation of the Spigelian lobe in the adult dorsal or “posterior” surface of the liver, this segment of the omentum assumes a vertical direction, forming the left boundary of the Spigelian recess, being reflected from the fissure for the ductus venosus to the abdominal portion of the œsophagus and the part of the lesser curvature of stomach adjacent to the cardia.
(b) Distal caudal portion of the lesser omentum is twisted laterally and turned to the right by the change in the position of the stomach and the development of the structures connected with the liver at the transverse fissure. It is reflected from this fissure to the distal part of the lesser curvature and to the first portion of the duodenum. This transverse segment of the lesser omentum is a secondary derivative from the right leaf of the primitive membrane, produced by the enlarged area for entrance of umbilical and portal veins at the transverse fissure. It lies ventrad of caudal border of Spigelian lobe.
2. The distal segment of the original omentum containing the umbilical vein (round ligament), continues imbedded in the umbilical fissure, to the ventral margin of the liver, where it joins the layers of the suspensory ligament passing over the cephalic surface.
3. The adult lesser omentum at the transverse fissure may be regarded as a diverticulum of the right leaf of the primitive embryonal sagittal omentum.
With the reduction of the umbilical vein after birth to form the round ligament this structure becomes deeply buried in the umbilical fissure. The ventral and dorsal layers of the lesser omentum at the transverse fissure thus become continuous with respectively the left and right layers of the second segment of the omentum which ascends vertically along the fissure for the ductus venosus.
4. The cephalic layer of the coronary ligament (Fig. 280) remains practically in the embryonic condition. The adult convex cephalic surface of the liver is traversed in the sagittal direction by the suspensory ligament which connects it with the abdominal surface of the diaphragm, and thus effects the division into right and left lobes on the convex surface. Arrived at the dorsal border of this surface (junction of “superior” and “posterior” surfaces) the right and left leaves of the falciform ligament turn at right angles into the cephalic layer of the right and left coronary ligament, which at each extremity meet the right and left caudal layers to form the triangular ligaments. It will thus be seen that the apparent irregularity in the relative arrangement of the s. c. “upper” and “lower” layers of the coronary ligaments, produced by the Spigelian recess, is only a difference in the interval between the two layers, caused by the vertical extent of the non-peritoneal direct diaphragmatic attachment of the right lobe to the right of the vena cava.
Comparative Anatomy of Spigelian Lobe and Vena Cava in the Cat.—The lines of peritoneal reflection in the cat’s liver and the arrangement of the Spigelian lobe and recess are seen in Fig. 281, taken from a preparation hardened in situ.
Fig. 281.—Liver of cat, hardened in situ. (Columbia University Museum, No. 1836.)
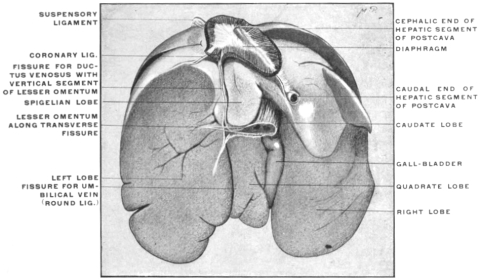
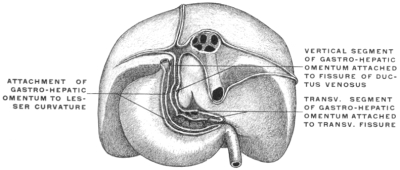
Fig. 282.—Dorsal view of human liver and stomach in fœtus at term, showing lines of hepatic and gastric attachment of lesser omentum.
Compared with the human liver it will be noted that the area of diaphragmatic adhesion is much less developed. The dorsal surface of the right lobe to the right of the postcava is peritoneal, there being no extension laterad of the right coronary and triangular ligaments. The postcava enters the liver in a special prolongation of the liver substance (caval lobe).
The boundaries of the Spigelian recess and the lines of attachment of the gastro-hepatic omentum correspond to the human arrangement.
RELATION OF THE HEPATIC PERITONEUM TO THE “LESSER SAC.”
Foramen of Winslow.—We have previously seen that the rotation of the stomach and the further growth of the dorsal mesogastrium lead, in the first instance, to the formation of the “lesser peritoneal cavity.” This cavity is in fact primarily the retrogastric space created by the transverse position of the stomach, augmented by the cavity of the omental bursa developed from the dorsal mesogastrium.
We have now to consider the additional boundaries of this space contributed by the peritoneal connection of the lesser curvature with the liver.
Fig. 283.—Schema of lines of reflection of peritoneum on dorsal surface of liver and in the formation of the gastro-hepatic omentum. A B, transverse section of lesser omentum attached to transverse fissure of liver and to pyloric section of lesser curvature (A' B'); B C, vertical section of lesser omentum passing between fissure of ductus venosus and cardiac section of lesser curvature of stomach (B' C'); C D, line of reflection of peritoneum from cephalic border of Spigelian lobe to diaphragm; D E, line of reflection of peritoneum from right border of Spigelian lobe to left margin of postcava and diaphragm.
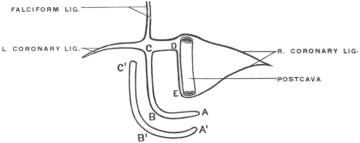
Fig. 284.—Portion of abdominal viscera of adult human subject, hardened in situ. (Columbia University, Study Collection.) The segment of stomach between cardiac and pyloric orifices has been removed, dividing the lesser omentum to this extent, but leaving the right extremity of the membrane (lig. hepato-duodenale) intact. Behind this portion the arrow passes through the foramen of Winslow.
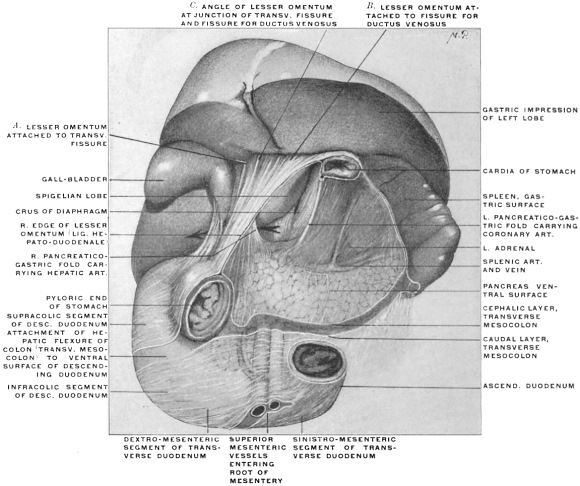
Fig. 285.—Liver and stomach of Macacus pileatus. (Columbia University, Study Collection.)
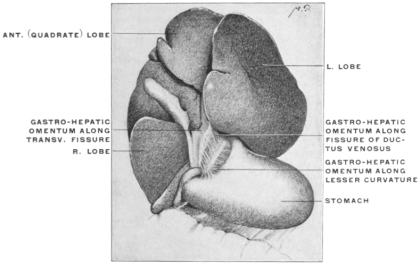
Fig. 286.—Abdominal viscera of adult human subject, hardened in situ; with liver lifted up after incision of the gastro-hepatic omentum. (Columbia University Museum, No. 1845.)
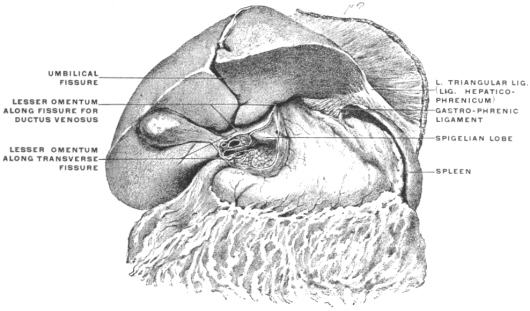
The lesser omentum follows, of course, along its gastric attachment to the lesser curvature the general direction of the stomach, passing from the cardia transversely downwards and to the right. We distinguish the two layers of the adult membrane as ventral and dorsal, which meet in the free right edge and include between them the main structures entering and leaving the liver at the transverse fissure, viz.: the portal vein, hepatic artery and bile-duct.
The lesser omentum therefore prolongs the plane of the stomach cephalad towards the liver and thus forms the continuation of the ventral boundary of the lesser peritoneal sac. We can now consider the line of its hepatic attachment in the light of the facts previously adduced, and combine the same with the line of gastric attachment to the lesser curvature. Fig. 282 shows the fœtal liver and stomach in their relative position in the dorsal view, and Fig. 283 gives the lines of the peritoneal reflections. The vertical segment of the omentum, occupying the fissure for the ductus venosus, passes to the cardiac part of the lesser curvature, its ventral layer covering the ventral and left side of the œsophagus, while its dorsal layer passes to the dorsal and right side of the œsophagus at its entrance into the stomach. The transverse segment of the omentum, attached on the liver to the portal or transverse fissure, accedes to the pyloric part of the lesser curvature. Of course the ventral and dorsal layers of the omentum are continuous with the serous visceral investment of the ventral and dorsal surfaces of the stomach.
Fig. 284 shows this right-angled course of the lesser omentum at the hepatic line of attachment in a preparation of the abdominal viscera hardened in situ, with the segment of the stomach between the cardiac and pyloric orifices removed. The arrow is passed behind the right free edge of the lesser omentum. This portion of the membrane is still intact, not having been disturbed by the removal of the body of the stomach, and includes between its layers the structures connected with the liver at the transverse fissure (duct, hepatic artery and portal vein). The lesser omentum is seen to be attached to the liver along the transverse fissure (Fig. 284, A) and along the fissure for the ductus venosus (Fig. 284, B), constituting the transverse and vertical segments above referred to, which pass into each other at the angle of junction between the transverse fissure (left end) and the fissure for the ductus venosus (Fig. 284, C). The caudal and left border of the Spigelian lobe is exposed by the division of the omentum, and the extent of the Spigelian or hepatic recess of the lesser peritoneal sac is shown. Fig. 285 shows the liver, stomach and lesser omentum of a Macaque monkey hardened in situ, and demonstrates still more conclusively that the uniform curve of the omentum along the lesser curvature of the stomach becomes a broken line at the hepatic attachment, the angle being placed at the left end of the transverse fissure at the point where the same encounters the fissure for the ductus venosus.
In Fig. 286 finally the hardened abdominal viscera of an adult human subject are shown in the ventral view with the lesser omentum incised. The cut through the lesser omentum exposes the hepatic recess of the lesser peritoneal cavity immediately to the left of the foramen of Winslow. Toward the right free margin of the omentum the divided portal vein, hepatic artery and duct are seen between the layers of the omentum imbedded in the pancreas and coursing behind the first portion of the duodenum on their way to the transverse fissure.
To the left of these structures the omental tuberosity of the pancreas projects above the level of the lesser curvature under cover of the secondary parietal peritoneum forming the dorsal wall of the lesser sac, while the lower edge of the Spigelian lobe appears in the upper angle of the incision.
If we remember that the liver is itself welded to the diaphragm between the layers of the coronary ligament (Fig. 280), it will become apparent that the serous surface of the Spigelian lobe forms part of the ventral wall of a peritoneal recess situated behind the lesser omentum, between this membrane and the diaphragm. Access to this recess, without the division of peritoneal layers, can only be obtained by passing from right to left, along the caudate lobe, between the vena cava behind, covered by parietal peritoneum, and the free right edge of the lesser omentum in front. (In the reverse direction of the arrow shown in Fig. 284.) This hepatic or Spigelian recess of the lesser peritoneal cavity has categorically the following boundaries (Figs. 282 and 283):
Dorsal: Parietal peritoneum, reflected along the line CD, from the caudal layer of the coronary ligament to the diaphragm.
Ventral: Visceral peritoneum investing the Spigelian lobe and the gastro-hepatic omentum.
Right: Reflection of peritoneum along the line DE (caval fissure) to become the parietal peritoneum covering the diaphragm.
Left: Right layer of lesser omentum, reflected along the fissure for the ductus venosus (CB) to the cardiac portion of the lesser curvature, continuous with the dorsal layer of the lesser omentum reflected from the transverse fissure to the pyloric segment of the lesser curvature (AB).
We will presently see that certain relations of the vessels connected with the liver at the transverse fissure and of the duodenum prevent the finger, when passed from right to left behind the free right edge of the lesser omentum and along the caudate lobe of the liver, from proceeding downward at this point. A narrow channel of communication is thus formed between the Spigelian recess and rest of the lesser sac on the one hand, and the general greater peritoneal cavity on the other. This channel is the so-called foramen of Winslow.
Having once passed this narrow space the finger will be in the Spigelian recess and can palpate its boundaries. Further progress cephalad and to the right is barred by the diaphragmatic adhesions of the liver just detailed. But in the direction downward behind the lesser omentum and along the dorsal surface of the stomach, as well as to the left toward the spleen the excursion is limited only by the length of the examining finger.
After opening the abdominal cavity of the human adult, elevating the liver and depressing the stomach, the hepatic attachment of the lesser omentum can be traced as already described. It will then be observed that the gastric attachment of the membrane lies in one plane following the lesser curvature while the hepatic attachment forms a broken line, with the angle situated at the left extremity of the transverse fissure. The vertical segment of the hepatic attachment, occupying the fissure for the ductus venosus, turns at this angle into the transverse segment which follows the transverse fissure to its right extremity where the two layers pass into each other around the right free omental margin (hepato-duodenal ligament). Consequently we overlook, in an abdominal cavity thus exposed, the entire caudal surface of the liver, including the caudal surfaces of right, left, and quadrate lobes. The junction of right and caudate lobes can be seen between vena cava and right edge of the omentum, or rather, it can be felt at this point. But the Spigelian lobe, turning its surface dorsad against the parietal peritoneum covering the diaphragm, forms part of the “posterior” liver surface and is not visible, although—as just stated, it can be palpated by passing the finger through the foramen of Winslow. The Spigelian lobe cannot be overlooked in its entire extent until the liver is removed from the body and regarded from behind. The caudal edge (continuation of its right angle into the caudate lobe and papillary tubercle) can be seen by tearing through the layers of the lesser omentum and lifting the liver up forcibly (Fig. 286).
Caudal Boundary of Foramen of Winslow.—We have above referred to the fact that the finger introduced through the foramen of Winslow meets in this canal with resistance if an attempt is made to pass downwards. After passing this constricting point the free excursion into the Spigelian recess and behind the omentum and stomach and toward the spleen can be performed.
In considering the elements which produce this narrowing of the communication between the two peritoneal sacs at the foramen of Winslow we have to deal with two factors, one primary and constant, the other secondary and inconstant.
1. The first of these is afforded by the arrangement of the arterial vessel supplying the liver. The hepatic artery is a branch of the cœliac axis, furnishing arterial blood to the liver tissues and supplying, in addition, branches to the stomach, duodenum and pancreas.
This vessel is, of course, placed primarily, like all other arterial branches supplying the alimentary tract, between the layers of the primitive dorsal mesentery. Originally the vessel supplies the distal (pyloric) portion of the stomach along its dorsal attached border (subsequently the greater curvature) corresponding to the adult gastro-epiploica dextra of the hepatic (gastro-duodenalis).
It likewise gives branches to the adjacent pyloric portion of the duodenum and the pancreas, as that gland develops from the intestine, corresponding to the adult superior pancreatico-duodenal branch, and to the ventral border (lesser curvature) of stomach, corresponding to the adult pyloric branch of the hepatic.
With the development of the liver from the duodenum arterial branches derived from this primitive gastro-duodenal vessel pass to the sprouting hepatic cylinders by continuing around the duodenum, beneath its serous investment, to reach the interval between the two layers of the ventral mesogastrium, in which the liver develops, near the free margin of this membrane.
After the rotation, which turns the right side of the stomach, duodenum and mesoduodenum dorsad, the branch which passes over the dorsal surface of the duodenum to reach the liver becomes more favorably situated and develops into the main hepatic artery which reaches the liver at the transverse fissure between the folds of the lesser omentum. The original right side of the duodenum, now turned dorsad, adheres to the parietal peritoneum. The hepatic artery which reached the liver by passing over this surface of the duodenum, beneath its visceral serous covering, becomes imbedded in connective tissue by the adhesion of the visceral duodenal and the primitive parietal peritoneum. Hence in the adult the hepatic artery courses imbedded in the connective tissue which binds the duodenum to the abdominal background to reach the interval between the two omental layers which carry it to the transverse fissure.
The hepatic artery, therefore, derived from one of the primitive intestinal branches (gastro-duodenal) is, notwithstanding its hidden position in the adult, originally situated between the layers of the free primitive dorsal mesogastrium.
Fig. 287.—Primitive dorsal and ventral mesogastrium with course of hepatic artery.
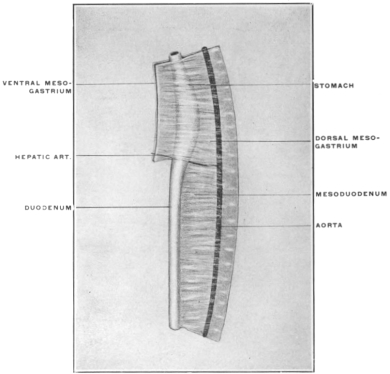
It now becomes necessary to regard the development of the great omentum from the primitive dorsal mesogastrium in relation to this course of the hepatic artery. We have seen that the great omentum and the cavity of the omental bursa is produced by the extension of the dorsal mesogastrium to the left and caudad, subsequent to the rotation of the stomach. The splenic artery and the left gastro-epiploic branch pass from the cœliac axis to the left between the layers of the mesogastrium, as previously seen (Figs. 291 and 292).
The hepatic artery, however, is so to speak placed on the border line between the portion of the primitive mesentery which, as dorsal mesogastrium, is to turn to the left and caudad to form the great omentum, and the portion which, as mesoduodenum, turns to the right and passes to the duodenal loop (Fig. 287).
In the further course of development the dorsal mesogastrium grows more and more, forming the omental bag, while the mesoduodenum on the other hand becomes anchored early and obliterated as a free membrane by adhesion of its original right layer to the primitive parietal peritoneum. The hepatic artery runs on the line dividing these two different mesenteric segments. We can imagine, so to speak, that the redundant growth of the omentum to the left and caudad, takes place over the hepatic artery as a resistant support (Figs. 288 and 289). Cephalad of the hepatic artery is the developing omentum, caudad of the vessel the mesoduodenum. The artery follows the cephalic limit of the mesoduodenum and becomes, as stated, adherent to the abdominal background in the segment between its origin from the cœliac axis and the point where, after having crossed the dorsal surface of the duodenum, it enters the right edge of the lesser omentum on its way to the liver.
Fig. 288.—The liver divides the ventral mesogastrium into a dorsal segment, the gastro-hepatic or lesser omentum, and a ventral segment, the suspensory or falciform ligament of the liver. Fig. 289.—Stages in the development of the dorsal mesogastrium (omental bursa) and mesoduodenum to show relation of hepatic artery to these two segments of the primitive common dorsal mesentery.
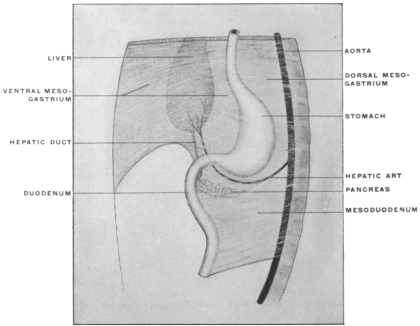
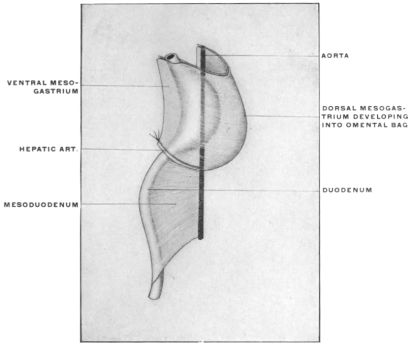
Pancreatico-gastric Folds.—If we open the lesser peritoneal cavity by dividing the gastro-hepatic omentum and look into the background of the retro-omental space, we will see a fold of the secondary lining parietal peritoneum (derived from the mesogastrium), which can be traced from the cephalic border of the pancreas to the pyloric extremity of the stomach. This fold carries the hepatic artery to the lesser omentum behind the first portion of the duodenum, and is called the right or main pancreatico-gastric fold. A similar fold, further to the left, carries in a like manner the coronary artery of the stomach to the cardiac end of the lesser curvature. This fold forms the left or secondary pancreatico-gastric fold. Between the two folds the caudal margin of the Spigelian lobe projects into the lesser cavity.
The appearance of the two pancreatico-gastric folds in the adult human subject is well seen in Fig. 284.
Fig. 290.—Abdominal viscera of Nasua rufa, brown coaiti, with stomach turned up and great omentum divided. (From a fresh dissection.)
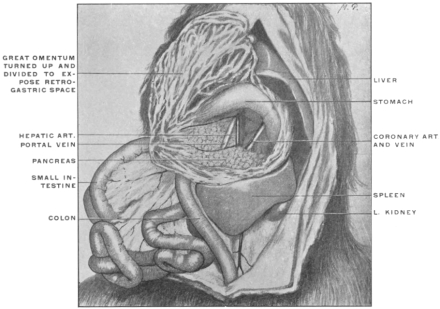
Fig. 291.—Schematic transection through foramen of Winslow before adhesion of dorsal mesogastrium and mesoduodenum to parietal peritoneum.
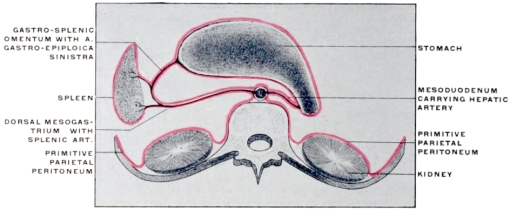
Fig. 292.—The same section after the adult conditions have been established by adhesion.
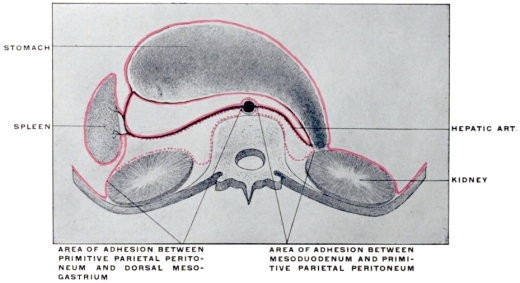
Fig. 290 shows the abdominal cavity of Nasua rufa, with great omentum divided to bring into view the vessels passing from cœliac axis to liver and stomach and elevating the retrogastric parietal peritoneum to produce the pancreatico-gastric folds.
(The course of the hepatic artery from cœliac axis to liver in the dorsal view in the cat is seen in Fig. 223.)
Figs. 291 and 292 represent schematically cross-sections directly through the foramen of Winslow, showing the method by means of which the hepatic artery reaches the upper border of the duodenum and the effect of the adhesion of duodenum and mesoduodenum upon the disposition of the vessel.
The coronary artery, like the splenic, is at first situated between the layers of the dorsal mesogastrium (vertebro-splenic segment). Like the splenic the coronary artery becomes anchored to the abdominal background and placed secondarily behind the parietal peritoneum of the lesser sac by the adhesion of this mesogastric segment to the primitive parietal peritoneum. To reach the lesser curvature at the cardia and to run thence from left to right along the lesser curvature between the layers of the gastro-hepatic omentum, the vessel raises the investing parietal peritoneum (originally the right leaf of the dorsal mesogastrium) into a crescentic fold, extending between its origin from the cœliac axis at cephalic margin of pancreas and the beginning of the lesser curvature of the stomach. Hence this fold is called the left pancreatico-gastric fold. (Seen well in Fig. 284.)
In the next place it must be borne in mind that the relation of the primitive hepatic artery to the vascular supply of the stomach, pancreas and duodenum produces a permanent shortening of the primitive mesentery at this point. This result is indicated in the schematic figures 287, 288 and 289.
In the original condition the dorsal mesentery, passing to a practically straight intestinal tube, is of uniform sagittal measure (Fig. 287).
As development proceeds, and as the liver grows from the duodenum, the hepatic artery develops from the primitive pyloric vessel as above indicated. This vessel, assuming greater importance with the rapid growth of the liver, is not lengthened out as happens with the remaining purely intestinal branches which follow the increase in the length of the intestinal canal. The hepatic artery, therefore, will mark the point where the original short sagittal extent of the primitive mesentery will tend to be preserved. Cephalad of this point the dorsal mesogastrium grows out into the great omentum (Figs. 288 and 289); caudad of the same point the membrane, in following the development of the intestine, becomes drawn out into the permanent mesentery and mesocolon.
The hepatic artery, in addition, marks the cephalic limit of the adhesion which anchors the duodenum and mesoduodenum to the parietal peritoneum. Consequently in the adult the vessel courses in as direct a manner as possible, taking the shortest course from the cœliac axis to the liver, passing dorsad of the duodenum and giving what now appear as secondary branches to supply the intestine, the stomach and pancreas (pyloric and gastro-duodenal arteries (pancreatico-duod. superior and gastro-epiploica dextra)).
Even if no fixation of the duodenum and mesoduodenum takes place this course of the hepatic artery will produce a constricted passage between the liver (caudate lobe) cephalad, abdominal parietes and aorta dorsad, lesser omentum and pyloric duodenum ventrad, and hepatic artery caudad. This passage leading from the general peritoneal cavity into the retrogastric space is the primitive foramen of Winslow. This condition is well represented in the abdominal cavity of some of the lower mammalia, in which duodenum and mesoduodenum remain permanently free.
Fig. 293 shows a view of the abdominal cavity from the right side in a specimen of the ant-eater, Tamandua bivittata.
Fig. 293.—Abdominal viscera of Tamandua bivittata, the little ant-eater, with the intestines turned downward and to the left. (From a fresh dissection.)
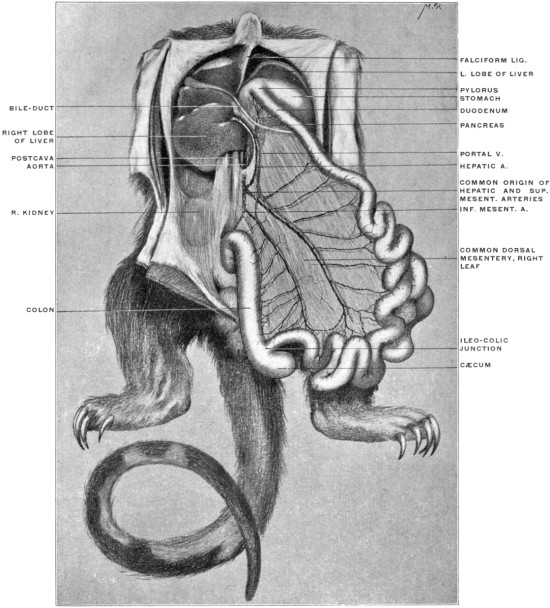
Fig. 294.—Schematic sagittal section through foramen of Winslow before fixation of pancreas by adhesion of mesoduodenum.
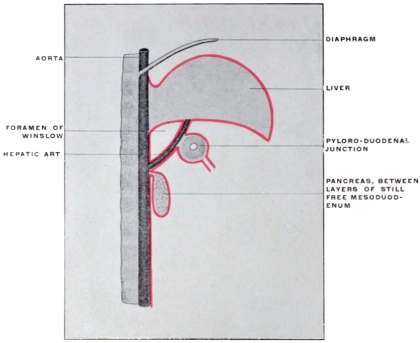
Fig. 295.—The same section after adhesion of mesoduodenum and pancreas. The pancreas appears secondarily retroperitoneal, after adhesion of apposed surfaces of mesoduodenum and primitive parietal peritoneum over dotted area, producing fixation of dorsal surface of pancreas.
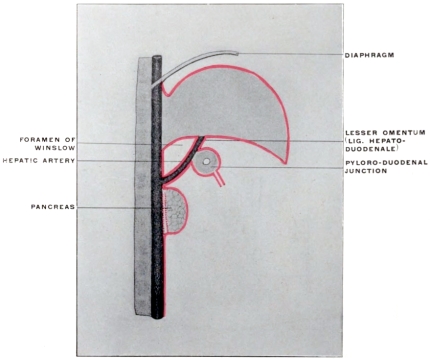
The right kidney is seen in the background, covered by the parietal peritoneum. The duodenum and mesoduodenum are free and can be turned toward the median line. The opening of the foramen of Winslow leading into the retrogastric space is seen between the liver cephalad, kidney and vena cava dorsad, lesser omentum and pyloric extremity of the stomach ventrad, and a fold of peritoneum carrying the hepatic artery caudad. Exactly similar conditions prevail in the cat and in many other mammals.
It will be seen in all these instances that neither portal vein nor bile-ducts limit the foramen caudad. These structures can be lifted up and turned toward the median line with the free duodenum and mesoduodenum. But the hepatic artery must pass to the liver from the retroperitoneal cœliac axis. In doing this the vessel traverses the cephalic border of the pancreas, and the pyloric extremity of the stomach and duodenum, to reach the lesser omentum which conveys it to the liver.
Consequently there must always be a narrow peritoneal neck between the liver cephalad, aorta dorsad, hepatic artery caudad, and pyloric extremity of stomach and duodenum together with the lesser omentum ventrad. It should be remembered that the vessel which extends after the development of the liver into the lesser omentum as the hepatic artery, was originally destined for the supply of these latter structures. In the adult these primary embryonic terminal branches to the intestine appear as secondary branches derived from the hepatic as the main vessel. Their origin, however, serves to keep the beginning of the small intestine in comparatively close connection with the hepatic artery which courses over the dorsal surface of the duodenum to reach the liver. The narrow space thus left between aorta, hepatic artery, duodenum, lesser omentum and liver forms the framework of the foramen of Winslow and appears always as a confined and narrow channel. This relation is shown in the accompanying schematic Figs. 294 and 295 which represent a sagittal section through the foramen. This primitive foramen is thus bounded cephalad by the liver (caudate lobe, connecting Spigelian and right lobes), ventrad by the first portion of the duodenum and the lesser omentum, with hepatic artery behind the intestine and between the omental layers; dorsad by the abdominal background and large retroperitoneal vessels, and caudad by the cœliac axis and beginning of the hepatic artery.
2. In the forms which possess in the adult an adherent duodenum and mesoduodenum, as in man, the foramen of Winslow obtains a secondary caudal limit by the agglutination of the descending duodenum and the parietal prerenal peritoneum. This is the secondary and inconstant factor referred to above in the caudal boundary of the foramen. The result of this anchoring of duodenum and mesoduodenum is to bring the margin of the foramen further to the right and to bury the hepatic artery still further from view. Thus in the adult human subject the structures bounding the foramen at the margin of the entrance into the narrow channel would be above caudate lobe of liver, behind postcava, below duodenum adherent to ventral surface of right kidney, in front first portion of duodenum and lesser omentum. The hepatic artery will be felt on introducing the finger through the foramen in its original position, but it will be seen that the actual boundaries of the foramen have been moved so to speak a little further to the right by the duodenal adhesion.
Fig. 296.—Dissection of adult liver, pancreas, spleen, and duodenum, with vessels, to show structures concerned in the formation of the foramen of Winslow. (Columbia University, Study Collection.)
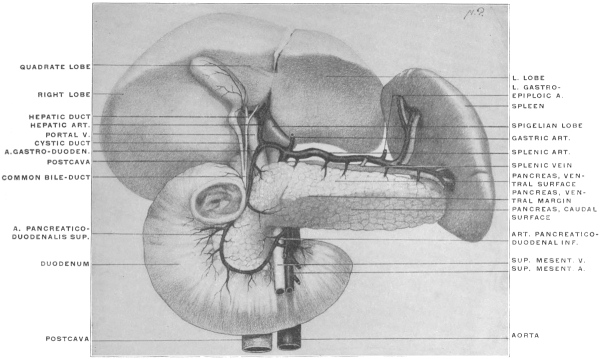
Fig. 296 shows a complete dissection of the adult human viscera and vessels concerned in the formation of the foramen, hardened in situ.
The stomach is removed, dividing of course the coronary artery and vein and the left gastro-epiploic artery. The portal vein, hepatic artery and bile-duct are seen entering and leaving the liver at the transverse fissure. Behind them and to the right the vena cava enters the liver. The hepatic artery distributes its pancreatico-duodenal branches to the duodenum and pancreas. The left angle of the Spigelian lobe and the fissure for the ductus venosus appear to the left of the portal vein and hepatic artery. The right angle of the Spigelian lobe and its continuation into the right lobe by means of the caudate lobe is hidden by the structures occupying the transverse fissure. We would enter the beginning of the foramen of Winslow by passing between the vena cava behind, the structures in the transverse fissure (portal vein, hepatic artery and duct) in front, caudate lobe of liver above and duodenum below, the latter in the undisturbed condition of the parts adherent to the right kidney. Continuing to the left the finger would pass between aorta behind, cœliac axis and hepatic artery below and in front, and liver above. These structures bound the permanent and primary narrow channel of communication between the retrogastric or lesser peritoneal space and the general peritoneal cavity, which exists even if a free duodenum and mesoduodenum allow us to lift the intestine away from vena cava and right kidney.